Related Experiment Video
Updated: May 29, 2026


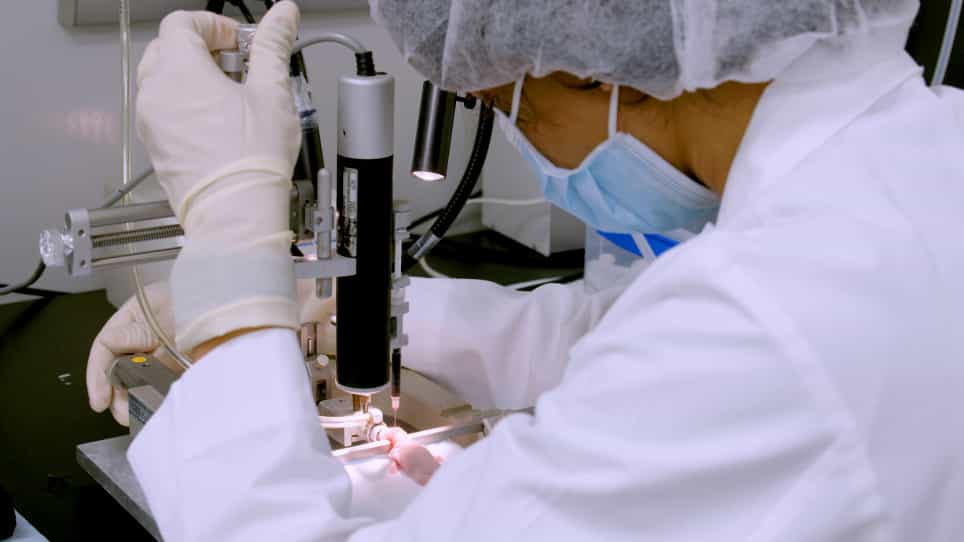
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Infantile posthemorrhagic hydrocephalus
Vasilios Tsitouras1, Spyros Sgouros
1Department of Neurosurgery, Mitera Childrens Hospital, Erythrou Stavrou 6, Marousi, 151 23 Athens, Greece.

Insights
Posthemorrhagic hydrocephalus in premature neonates can lead to long-term cognitive issues, but timely treatment is key. While shunting is often necessary, it carries risks and challenges like multiloculated hydrocephalus.
Area of Science:
- Neonatal Neurology
- Pediatric Neurosurgery
- Perinatal Medicine
Background:
- Intraventricular/germinal matrix hemorrhage impacts 7-30% of premature neonates.
- Hydrocephalus requiring shunting develops in 25-80% of affected infants, influenced by hemorrhage grade.
- Low birth weight and gestational age are significant predisposing factors.
Purpose of the Study:
- To review the pathogenesis and management of posthemorrhagic hydrocephalus in neonates.
- To discuss diagnostic imaging modalities and treatment strategies.
- To highlight long-term outcomes and potential complications.
Main Methods:
- Review of existing evidence on hydrocephalus pathogenesis, particularly the role of TGF-β1.
- Discussion of diagnostic tools: ultrasound for screening, MRI for detailed evaluation.
- Analysis of various treatment strategies for cerebrospinal fluid (CSF) management and intracranial hypertension.
Main Results:
- TGF-β1 is implicated in hydrocephalus pathogenesis, but effective treatments to clear blood products from CSF remain elusive.
- Ultrasound and MRI are crucial for diagnosis, surgical decision-making, and long-term follow-up.
- Management involves strategies to drain CSF, aiming to allow clearance and enable shunting once the neonate is stable.
Conclusions:
- Cognitive outcomes are primarily linked to the initial hemorrhage and perinatal events, not solely hydrocephalus if treated promptly.
- Shunting, while necessary, can lead to long-term complications like mechanical issues and overdrainage.
- Posthemorrhagic hydrocephalus patients face higher risks of complex forms like multiloculated hydrocephalus and encysted fourth ventricle.
Introduction:
Intraventricular/germinal matrix hemorrhage affects 7-30% of premature neonates, 25-80% of whom (depending on the grade of the hemorrhage) will develop hydrocephalus requiring shunting. Predisposing factors are low birth weight and gestational age.
Material:
There is increasing evidence for the role of TGF-β1 in the pathogenesis of hydrocephalus, but attempts to develop treatment modalities to clear the cerebrospinal fluid (CSF) from blood degradation products have not succeeded so far. Ultrasound is a valuable screening tool for high-risk infants and magnetic resonance imaging is increasingly utilized to differentiate progressive hydrocephalus from ex vacuo ventriculomegaly, evaluate periventricular parenchymal damage, decide on the surgical treatment of hydrocephalus, and follow up these patients in the long term. Treatment of increasing ventriculomegaly and intracranial hypertension in the presence of hemorrhagic CSF can involve a variety of strategies, all with relative drawbacks, aiming to drain the CSF while gaining time for it to clear and the neonate to reach term and become a suitable candidate for shunting. Eventually, patients with progressive ventriculomegaly causing intracranial hypertension, who have reached term and their CSF has cleared from blood products, will need shunting.
Conclusion:
Cognitive long-term outcome is influenced more by the effect of the initial hemorrhage and other perinatal events and less by hydrocephalus, provided that this has been addressed timely in the early postnatal period. Shunting can have many long-term side effects due to mechanical complications and overdrainage. In particular, patients with posthemorrhagic hydrocephalus are more susceptible to multiloculated hydrocephalus and encysted fourth ventricle, both of which are challenging to treat.
Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction