Related Experiment Video
Updated: May 29, 2026


Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Hydrocephalus and Chiari type I malformation
Concezio Di Rocco1, Paolo Frassanito, Luca Massimi
1Pediatric Neurosurgery, Catholic University Medical School, Policlinic A. Gemelli, Largo Agostino Gemelli, 8, 00168 Rome, Italy.

Insights
Hydrocephalus and Chiari type I malformation (CIM) association has complex causes. Understanding these diverse pathogenetic mechanisms is key to effective treatment strategies for CIM and hydrocephalus.
Area of Science:
- Neuroscience
- Neurosurgery
- Pediatric Neurology
Background:
- The association between hydrocephalus and Chiari type I malformation (CIM) is long-recognized.
- The underlying pathogenetic mechanisms linking these two conditions remain complex and debated.
Purpose of the Study:
- To explore the heterogeneous pathogenetic mechanisms underlying the association of hydrocephalus and Chiari type I malformation.
- To discuss the implications of these mechanisms for therapeutic approaches.
Main Methods:
- Review of clinical and radiological data from patients with complex craniosynostosis.
- Analysis of pathogenetic hypotheses including supratentorial pressure and cephalo-cranial disproportion.
- Consideration of jugular foramen stenosis and venous hypertension.
Main Results:
- Multiple pathogenetic pathways may lead to the radiological association of ventricular enlargement and hindbrain herniation.
- Supratentorial hypertensive hydrocephalus can exert pressure causing CIM.
- Cephalo-cranial disproportion in complex craniosynostosis can lead to secondary hydrocephalus and CIM.
Conclusions:
- The diverse etiologies of hydrocephalus and CIM necessitate tailored therapeutic strategies.
- Endoscopic third ventriculocisternostomy is an emerging treatment option for its physiological correction of CSF dynamics.
- This endoscopic approach offers minimal interference with developmental processes involved in hydrocephalus and CIM.
Introduction:
[corrected] Hydrocephalus has been related to Chiari type I malformation (CIM) for a long time. The pathogenesis of this association is complex and still debated.
Discussion:
A supratentorial hypertensive hydrocephalus may cause CIM, exerting pressure from above. Another pathogenetic hypothesis is based on the clinical and radiological data from patients affected by complex craniosynostosis, in which this association is more commonly observed as the consequence of a "cephalo-cranial disproportion" ultimately leading to a secondary hydrocephalus. In some cases, the concomitant presence of a stenosis of the jugular foramina would determine a condition of upward venous hypertension, resulting in the development of CIM and an associated hydrocephalus due to cerebellar parenchyma turgor.
Conclusions:
The radiological association of ventricular enlargement and hindbrain herniation would be the result of heterogeneous pathogenetic mechanisms which would then require specific therapeutic approaches. In this context, the endoscopic third ventricle-cisternostomy is gaining an increasing interest because of its more physiologic correction of the altered CSF dynamics and its minor interference on the developmental processes responsible for the association of hydrocephalus and CIM.

Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:18
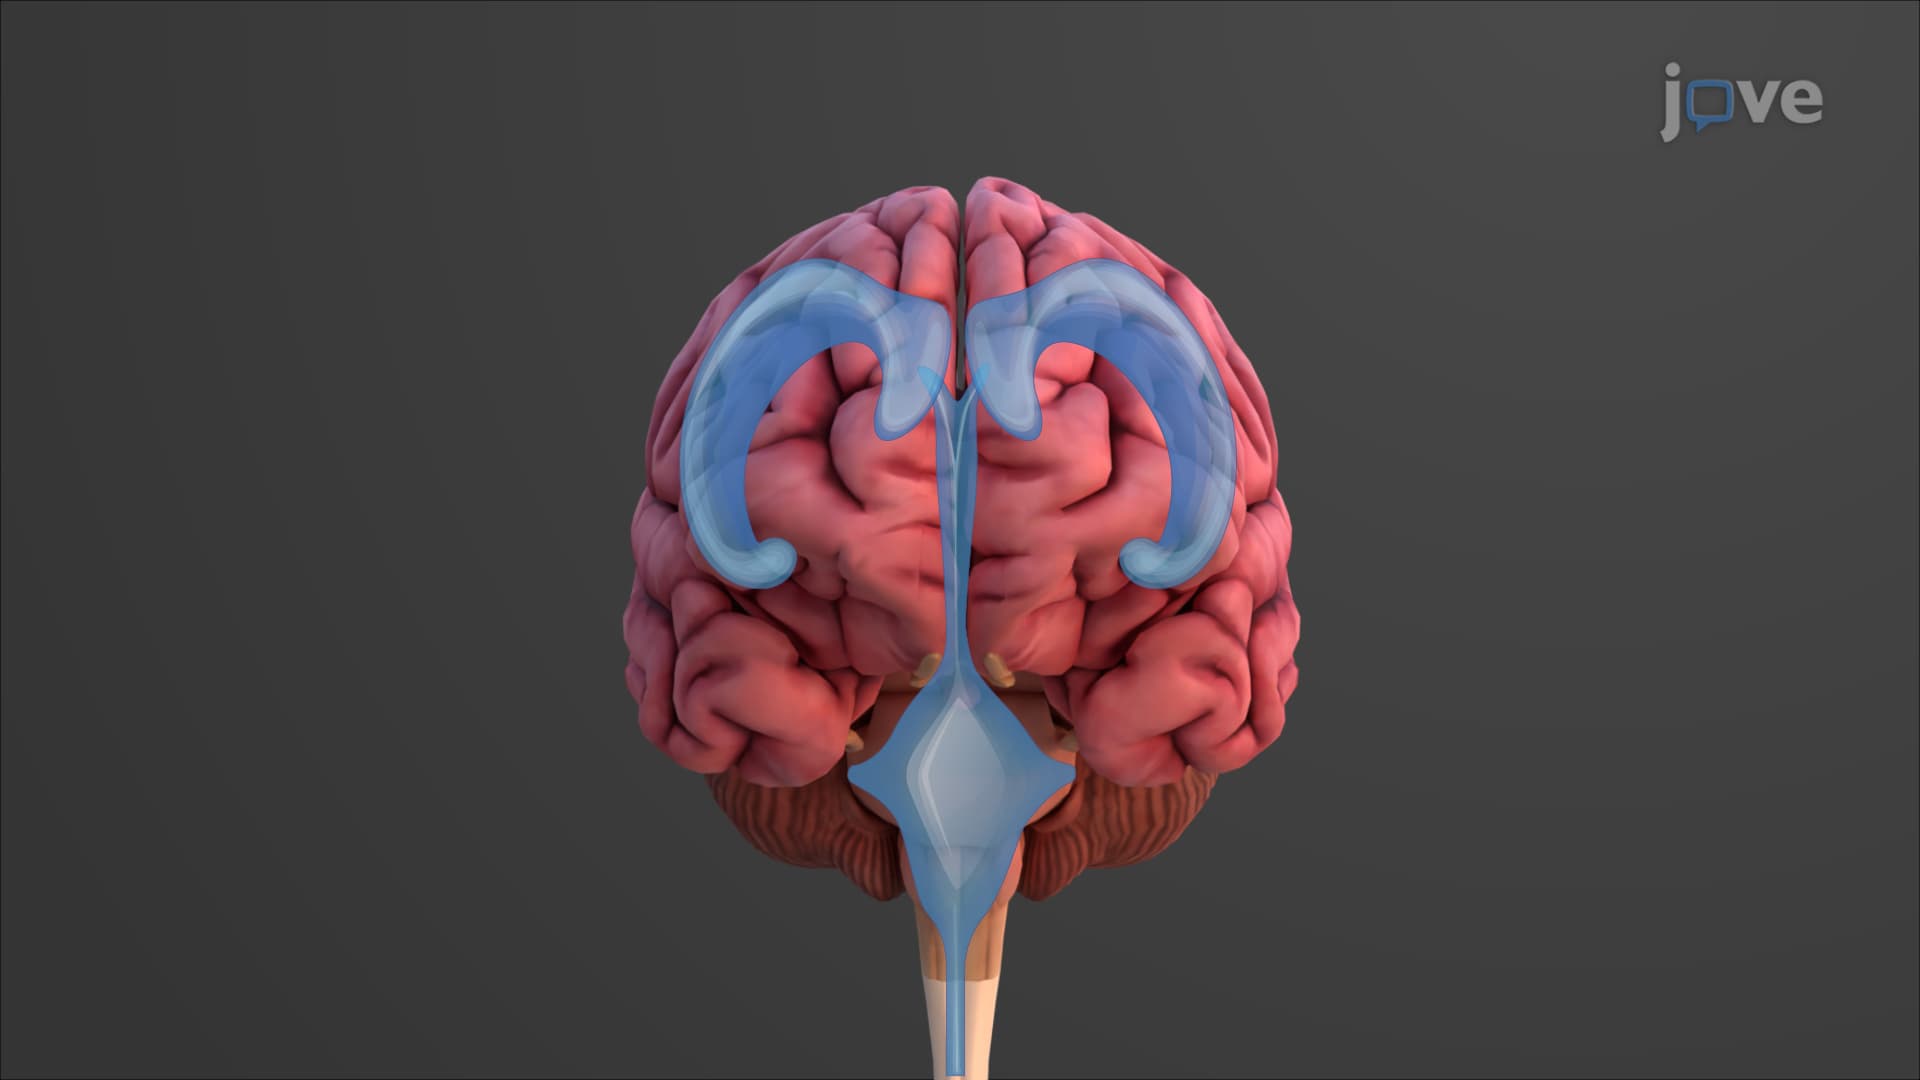
Anatomy of the Brain: Ventricles
 01:26
Bacterial Meningitis II: Pathophysiology