Related Experiment Video
Updated: May 29, 2026
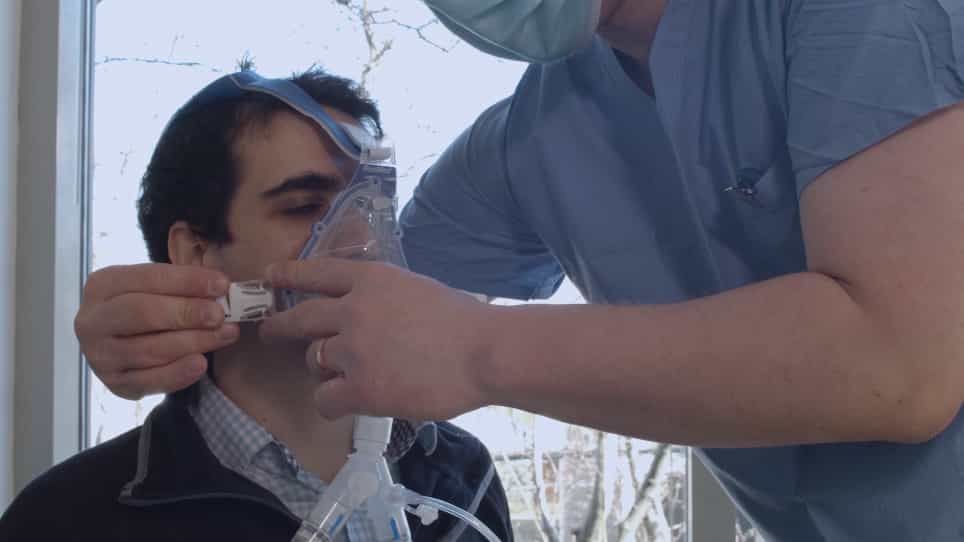

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Inhaled nitric oxide in preterm infants: an individual-patient data meta-analysis of randomized trials
Lisa M Askie1, Roberta A Ballard, Gary R Cutter
1National Health and Medical Research Council Clinical Trials Centre, University of Sydney, Sydney, Australia. laskie@ctc.usyd.edu.au

Insights
Routine inhaled nitric oxide (iNO) is not recommended for preterm infants with respiratory failure. Higher starting doses may offer benefits, but further research is needed due to trial design variations.
Area of Science:
- Neonatal Medicine
- Respiratory Physiology
- Clinical Trials
Background:
- Inhaled nitric oxide (iNO) is used for pulmonary hypertension and hypoxic respiratory failure in term infants.
- Previous randomized controlled trials (RCTs) on preterm infants at risk for chronic lung disease (CLD) yielded contradictory results.
- A comprehensive meta-analysis was needed to clarify iNO's efficacy in this vulnerable population.
Purpose of the Study:
- To determine the overall effectiveness of inhaled nitric oxide (iNO) in preterm infants at risk for chronic lung disease (CLD).
- To investigate the impact of varying iNO doses and treatment protocols on clinical outcomes.
- To provide evidence-based recommendations for the use of iNO in neonatal respiratory care.
Main Methods:
- Individual-patient data meta-analysis of randomized controlled trials involving preterm infants (<37 weeks' gestation).
- Outcomes were statistically adjusted for trial-level differences and intrafamilial correlations.
- Data from 3298 infants across 12 trials (96% of enrolled infants) were analyzed.
Main Results:
- No statistically significant effect of iNO on the composite outcome of death or CLD (RR: 0.96; 95% CI: 0.92-1.01).
- No significant differences observed in severe neurologic events on imaging (RR: 1.12; 95% CI: 0.98-1.28).
- A potential benefit was suggested with higher starting iNO doses (>5 ppm) in one trial, but this requires further investigation due to confounding factors.
Conclusions:
- Routine use of inhaled nitric oxide (iNO) for respiratory failure in preterm infants is not recommended.
- Higher starting doses of iNO may warrant further examination but require careful consideration of trial design and patient characteristics.
- Current evidence does not support widespread iNO use in this population without additional research.
Background:
Inhaled nitric oxide (iNO) is an effective therapy for pulmonary hypertension and hypoxic respiratory failure in term infants. Fourteen randomized controlled trials (n = 3430 infants) have been conducted on preterm infants at risk for chronic lung disease (CLD). The study results seem contradictory.
Design/Methods:
Individual-patient data meta-analysis included randomized controlled trials of preterm infants (<37 weeks' gestation). Outcomes were adjusted for trial differences and correlation between siblings.
Results:
Data from 3298 infants in 12 trials (96%) were analyzed. There was no statistically significant effect of iNO on death or CLD (59% vs 61%: relative risk [RR]: 0.96 [95% confidence interval (CI): 0.92-1.01]; P = .11) or severe neurologic events on imaging (25% vs 23%: RR: 1.12 [95% CI: 0.98-1.28]; P = .09). There were no statistically significant differences in iNO effect according to any of the patient-level characteristics tested. In trials that used a starting iNO dose of >5 vs ≤ 5 ppm there was evidence of improved outcome (interaction P = .02); however, these differences were not observed at other levels of exposure to iNO. This result was driven primarily by 1 trial, which also differed according to overall dose, duration, timing, and indication for treatment; a significant reduction in death or CLD (RR: 0.85 [95% CI: 0.74-0.98]) was found.
Conclusions:
Routine use of iNO for treatment of respiratory failure in preterm infants cannot be recommended. The use of a higher starting dose might be associated with improved outcome, but because there were differences in the designs of these trials, it requires further examination.

