Related Experiment Video
Updated: May 29, 2026


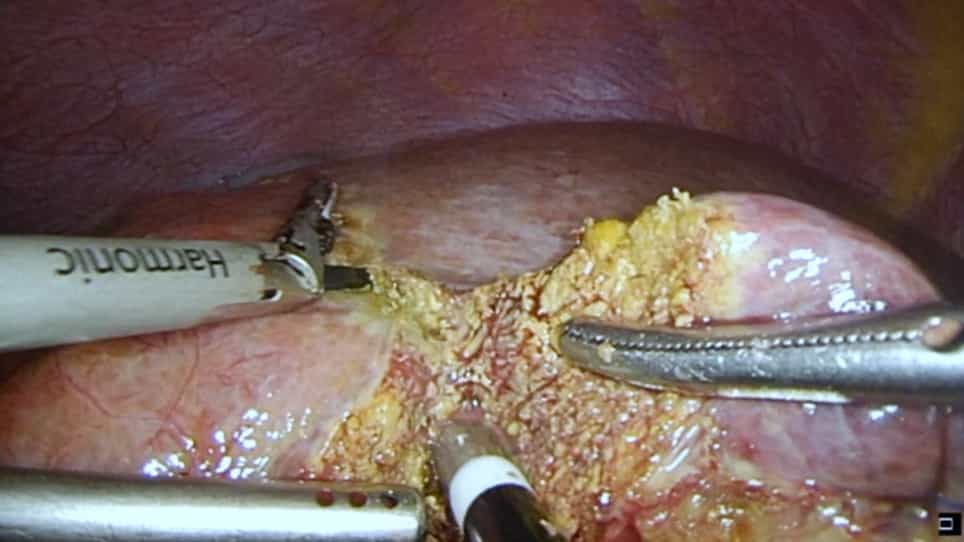
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
General surgery in patients with a bleeding diathesis: how we do it
Kamal R Aryal1, D Wiseman, Ajith K Siriwardena
1Department of General Surgery, Central Manchester and Manchester Children's University Hospitals NHS Foundation Trust, and University of Manchester, Manchester Royal Infirmary, Oxford Road, Manchester, M13 9WL, UK. kamal.aryal@jpaget.nhs.uk

Background:
This study was undertaken to assess perioperative management, postoperative complications, and the adequacy of perioperative plasma factor levels in a regional hemophilia center.
Methods:
A total of 113 consecutive patients (75 men, 38 women; median age 48 years, range 18-86 years) with bleeding disorders undergoing general surgical and endoscopic procedures (144 procedures: 15 urgent, 129 elective) were reviewed. The episodes were identified from a prospectively collected database at a regional hemophilia center from 1998 to the end of 2008. In all, 46% of the surgical patients had hemophilia A, 38% had von Willebrand disease, 6% had hemophilia B, 5% had factor XI deficiency, and 4% had other disorders.
Results:
Procedures carried out were endoscopic in 40%, minor in 25%, and intermediate and major in 35%. There were two postoperative deaths, both in patients undergoing urgent major procedures. Postoperative complications occurred after 7.6% (4.0% hemorrhagic, 3.6% nonhemorrhagic) of the procedures. Four of six patients with postoperative hemorrhage required further operative intervention. The median dose of clotting factor for Hemophilia A patients was 2240 U for endoscopic procedures, 7500 U for minor procedures, and 23,500 U for intermediate/major procedures. In hemophiliacs, the mean preoperative plasma factor level attained was 129 IU/dl (SD 16) in patients who developed postoperative hemorrhagic complications and 125 IU/dl (SD 37) in those who did not have bleeding, indicating that in no case was hemorrhage attributable to inadequate factor replacement.
Conclusions:
General surgical and endoscopic procedures can be performed with low morbidity and mortality rates when there is appropriate factor replacement and good support from the hemophilia team.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:30
Venous Thrombosis IV: Nursing Management