Related Experiment Video
Updated: May 29, 2026
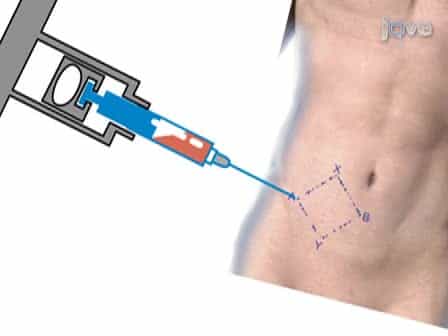

Performing and Processing FNA of Anterior Fat Pad for Amyloid
Published on: October 30, 2010
Endoscopic and histopathological features of gastrointestinal amyloidosis
Akira Hokama1, Kazuto Kishimoto, Manabu Nakamoto
1Akira Hokama, Kazuto Kishimoto, Tetsuo Hirata, Jiro Fujita, Department of Infectious, Respiratory, and Digestive Medicine, Faculty of Medicine, University of the Ryukyus, Okinawa 903-0125, Japan.

Abstract:
Amyloidosis is a rare disorder, characterized by the extracellular deposition of an abnormal fibrillar protein, which disrupts tissue structure and function. Amyloidosis can be acquired or hereditary, and systemic or localized to a single organ, such as the gastrointestinal (GI) tract. Clinical manifestations may vary from asymptomatic to fatal forms. Primary amyloidosis (monoclonal immunoglobulin light chains, AL) is the most common form of amyloidosis. AL amyloidosis has been associated with plasma cell dyscrasias, such as, multiple myeloma. Secondary amyloidosis is caused by the deposition of fragments of the circulating acute-phase reactant, serum amyloid A protein (SAA). Common causes of AA amyloidosis are chronic inflammatory disorders. Although GI symptoms are usually nonspecific, histopathological patterns of amyloid deposition are associated with clinical and endoscopic features. Amyloid deposition in the muscularis mucosae, submucosa, and muscularis propria has been dominant in AL amyloidosis, leading to polypoid protrusions and thickening of the valvulae conniventes, whereas granular amyloid deposition mainly in the propria mucosae has been related to AA amyloidosis, resulting in the fine granular appearance, mucosal friability, and erosions. As a result, AL amyloidosis usually presents with constipation, mechanical obstruction, or chronic intestinal pseudo-obstruction while AA amyloidosis presents with diarrhea and malabsorption Amyloidotic GI symptoms are mostly refractory and have a negative impact on quality of life and survival. Diagnosing GI amyloidosis requires high suspicion of evaluating endoscopists. Because of the absence of specific treatments for reducing the abundance of the amyloidogenic precursor protein, we should be aware of certain associations between patterns of amyloid deposition and clinical and endoscopic features.
Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
03:03Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:27
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...
 01:28
Amebiasis
 01:26
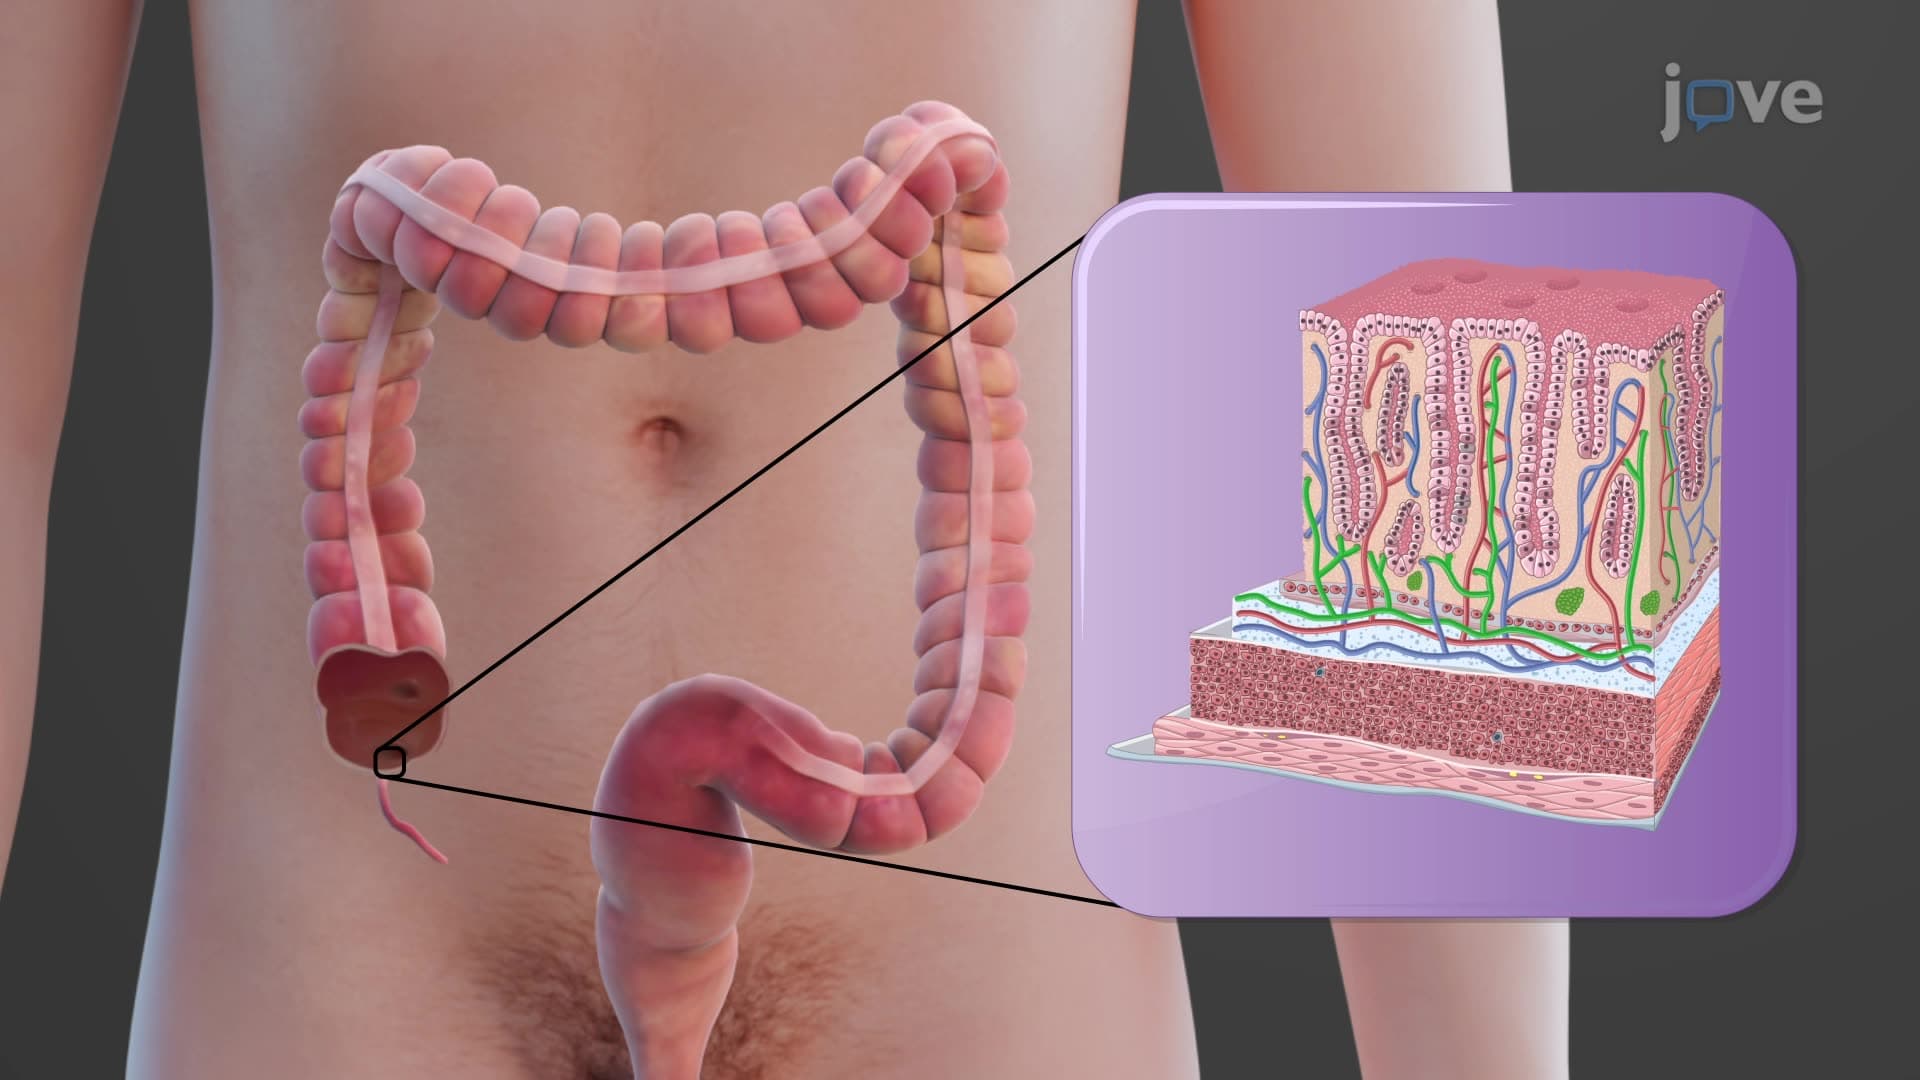
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...