Related Experiment Video
Updated: May 29, 2026


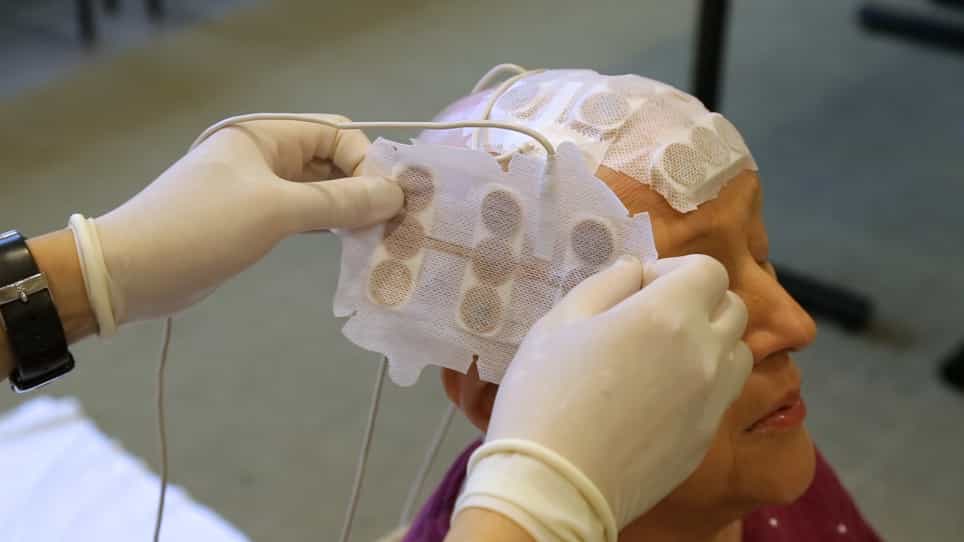
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Medical treatment of recurrent meningiomas
Marc C Chamberlain1, Jill S Barnholtz-Sloan
1Department of Neurology, Division of Neuro-Oncology, University of Washington, Fred Hutchinson Research Cancer Center, Seattle Cancer Care Alliance, 825 Eastlake Avenue East, Mailstop: G4-940, Seattle, WA 98109-1023, USA. chambemc@u.washington.edu

Abstract:
Meningiomas are the second most common primary brain tumor and are primarily treated with surgery (with or without embolization) and radiotherapy. Increasingly today, meningiomas undergo multiple resections and two radiotherapy treatments (either stereotactic or conventional external beam) before consideration for hormonal, chemotherapy or targeted therapy. The failure of hormonal and cytotoxic chemotherapy in the treatment of recurrent meningioma and increasing understanding of potential molecular targets in meningioma has resulted in multiple studies utilizing single-agent targeted therapy directed at biologically relevant signaling pathways, such as somatostatin (Sandostatin(®) LAR, SOM230c), PDGF (imatinib), EGF (erlotinib) and VEGF (sunitinib and vatalanib). Early results using a targeted approach have been modest at best and are often associated with significant toxicity. Consequently and at present, the brain tumor guidelines recognize only three medical therapies for inoperable and radiation-refractory meningiomas: hydroxyurea, IFN-α and Sandostatin LAR, a somatostatin analogue. Clearly, there remains an unmet need in neuro-oncology with respect to the medical treatment of recurrent meningiomas.