Related Experiment Video
Updated: May 28, 2026

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Maximal oxygen consumption is best predicted by measures of cardiac size rather than function in healthy adults
André La Gerche1, Andrew T Burns, Andrew J Taylor
1Department of Medicine, St Vincent's Hospital, University of Melbourne, Fitzroy, Australia. Andre.LaGerche@svhm.org.au

Abstract:
Training induces changes in cardiac structure and function which improves cardiac output (CO) and oxygen delivery during exercise. It is unclear whether it is cardiac structure or function which is of greatest importance in determining maximal oxygen consumption (VO(2max)). In 55 subjects (15 non-athletes, 32 amateur and 8 elite athletes), left and right ventricular (LV and RV) volumes and mass were assessed by magnetic resonance imaging (CMR). Comprehensive traditional and novel echocardiographic measures included colour-coded Doppler echocardiography to assess myocardial velocities, strain and strain rate at rest and maximal exercise in both ventricles. Measures of cardiac size and function were assessed as univariate and multivariate predictors of VO(2max). LV and RV mass correlated strongly with VO(2max) (r = 0.79 and r = 0.65, respectively, p < 0.0001), as did LV and RV end-diastolic volumes (r = 0.68 and r = 0.75, p < 0.0001) and heart rate reserve (r = 0.60, p < 0.0001). Measures of myocardial function were not predictive of VO(2max) with the exception of RV diastolic velocities (r = 0.32 and r = 0.36 for rest and exercise, respectively, p < 0.05). On multivariate analysis, only RV end-diastolic volume, LV mass and heart rate reserve were independent predictors (beta = 0.28, 0.45 and 0.27 respectively, p < 0.0001) and together explained 73% of the variance in VO(2max). Measures of cardiac morphology are strongly associated with VO(2max) in healthy adults and well-trained athletes. A combination of ventricular volume, mass and heart rate reserve explains much of the variance in VO(2max), whilst measures of myocardial function do not further strengthen predictive models.
More Related Videos
 07:26
Conducting Maximal and Submaximal Endurance Exercise Testing to Measure Physiological and Biological Responses to Acute Exercise in Humans
Published on: October 17, 2018
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Related Concept Videos
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...
 01:22
Respiratory Volumes and Capacities
 01:29
Pathophysiology of Cardiac Performance
 01:19
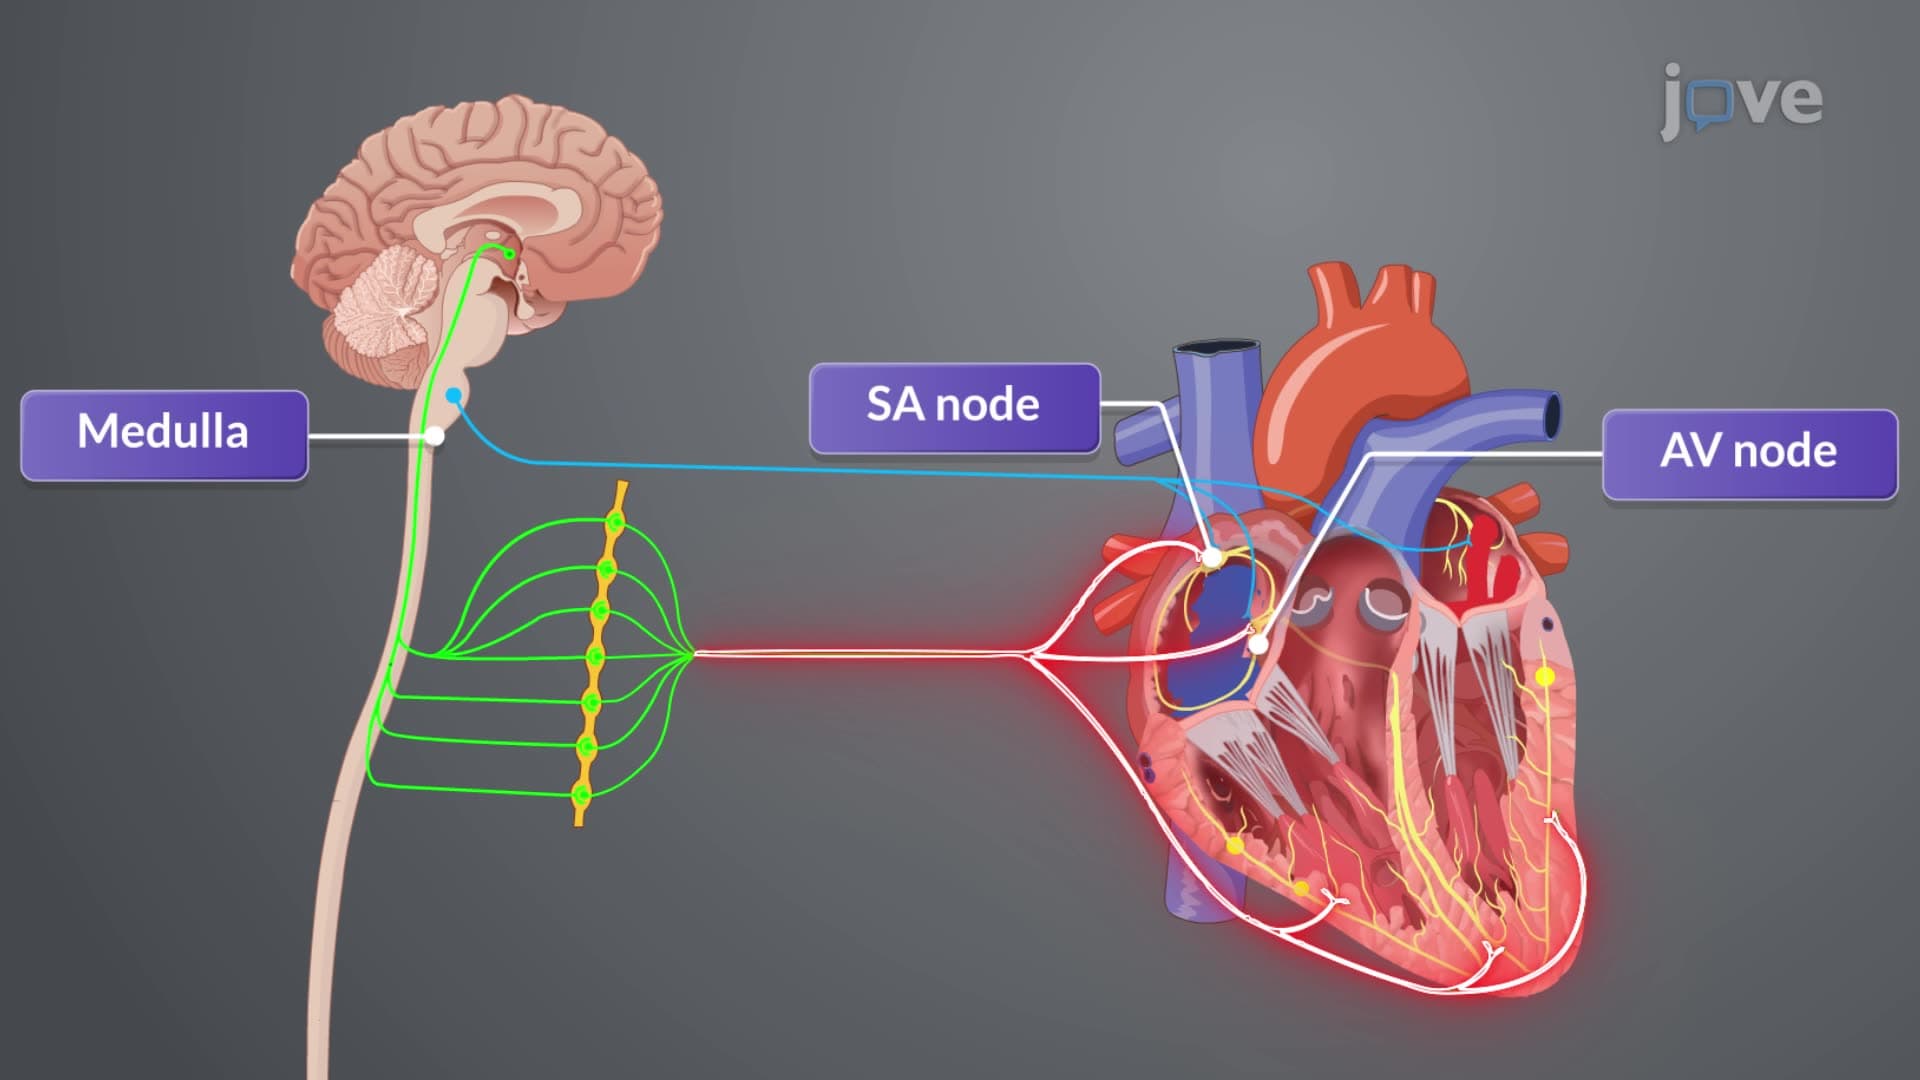
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...