Related Experiment Video
Updated: May 28, 2026
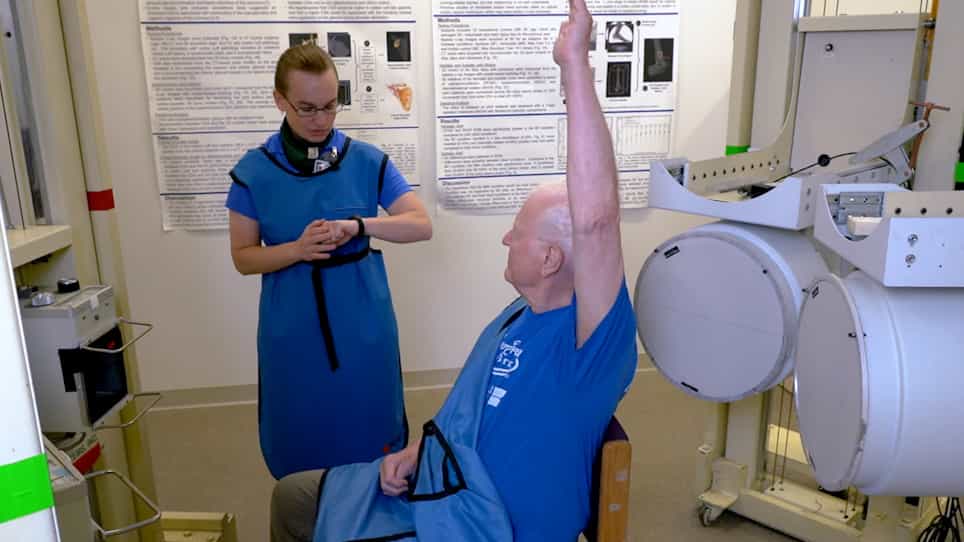

Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
In vivo analysis of coracoclavicular ligament kinematics during shoulder abduction
Kaywan Izadpanah1, Elizabeth Weitzel, Matthias Honal
1Department of Orthopaedic and Trauma Surgery, University Hospital Freiburg, Freiburg, Germany. izadpanah@me.com

Background:
Anatomic reconstruction of the coracoclavicular ligaments for the treatment of acromioclavicular joint separations provides superior biomechanical stability compared with other procedures. Clavicular and coracoidal footprints of the conoid ligament (CL) and the trapezoid ligament (TL) are well described. So far, little is known about their kinematics and the changes of the coracoclavicular distance during shoulder abduction.
Hypothesis:
The coracoclavicular distance along the coracoclavicular ligaments changes significantly with shoulder abduction and weightbearing.
Study Design:
Descriptive laboratory study.
Methods:
With use of an open magnetic resonance imaging scanner, the shoulders of 13 healthy volunteers were examined in supine and sitting positions. Three-dimensional magnetic resonance images of the shoulders were obtained in 30° increments of abduction (0°-120°). A manual segmentation of the scapula, the clavicle, and the coracoclavicular ligaments was performed. The insertion points of the coracoclavicular ligaments were identified, and automated measures along the ligamentous course were carried out.
Results:
During transfer from the lying to sitting position, the coracoclavicular distance showed significant lengthening of 3 mm along the center of the CL, which significantly increased another 3 mm during shoulder abduction to a total lengthening of 6 mm. In the supine position, the coracoclavicular distance along the TL did not elongate significantly. In the sitting position, the distance along the medial portion of the TL shortened significantly, whereas the distance along the center portion did not elongate significantly during shoulder abduction.
Conclusion:
The distances between the coracoclavicular insertion points depend on both patient and shoulder positioning. To prevent overconstraining of the graft, the CL should be fixated during 90° to 120° of shoulder abduction in a sitting position. Isometric reconstruction of the TL can be achieved if precise fixation of the graft at the centers of the conoidal and clavicular footprints is performed.
More Related Videos
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:19
Bones of the Upper Limb: Humerus
 01:25
Relative Motion Analysis using Rotating Axes
However, to express the relative position of point B relative to point A, an additional frame of reference, denoted as x'y', is necessary. This additional frame not only translates but also rotates relative to the fixed frame, making it instrumental in...
 01:10
Ankle Joint
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...