Related Experiment Video
Updated: Apr 8, 2026
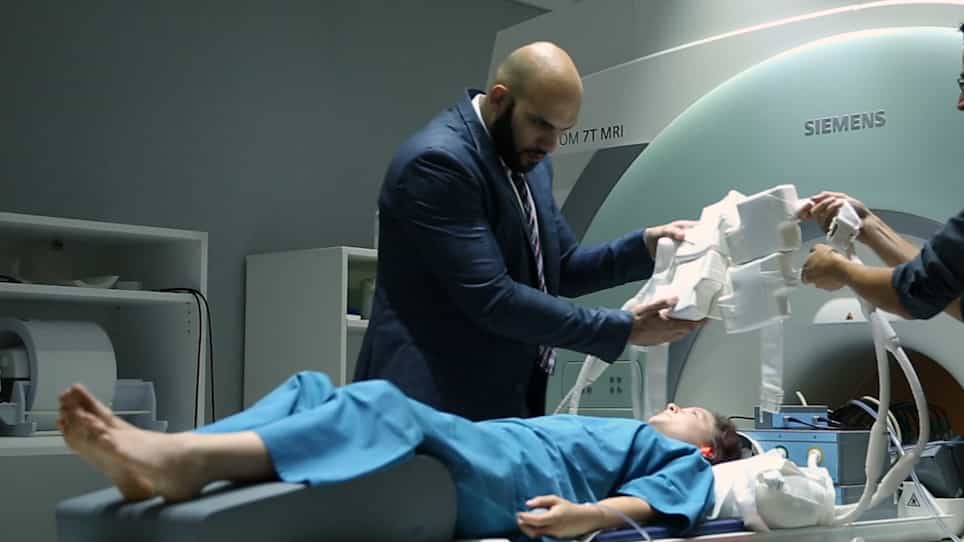
Cardiac Magnetic Resonance Imaging at 7 Tesla
Published on: January 6, 2019
A prospective evaluation of a protocol for magnetic resonance imaging of patients with implanted cardiac devices
Saman Nazarian1, Rozann Hansford, Ariel Roguin
1Johns Hopkins University, Baltimore, Maryland 21287, USA. snazarian@jhmi.edu

Background:
Magnetic resonance imaging (MRI) is avoided in most patients with implanted cardiac devices because of safety concerns.
Objective:
To define the safety of a protocol for MRI at the commonly used magnetic strength of 1.5 T in patients with implanted cardiac devices.
Design:
Prospective nonrandomized trial. (ClinicalTrials.gov registration number: NCT01130896) SETTING: One center in the United States (94% of examinations) and one in Israel.
Patients:
438 patients with devices (54% with pacemakers and 46% with defibrillators) who underwent 555 MRI studies.
Intervention:
Pacing mode was changed to asynchronous for pacemaker-dependent patients and to demand for others. Tachyarrhythmia functions were disabled. Blood pressure, electrocardiography, oximetry, and symptoms were monitored by a nurse with experience in cardiac life support and device programming who had immediate backup from an electrophysiologist.
Measurements:
Activation or inhibition of pacing, symptoms, and device variables.
Results:
In 3 patients (0.7% [95% CI, 0% to 1.5%]), the device reverted to a transient back-up programming mode without long-term effects. Right ventricular (RV) sensing (median change, 0 mV [interquartile range {IQR}, -0.7 to 0 V]) and atrial and right and left ventricular lead impedances (median change, -2 Ω [IQR, -13 to 0 Ω], -4 Ω [IQR, -16 to 0 Ω], and -11 Ω [IQR, -40 to 0 Ω], respectively) were reduced immediately after MRI. At long-term follow-up (61% of patients), decreased RV sensing (median, 0 mV, [IQR, -1.1 to 0.3 mV]), decreased RV lead impedance (median, -3 Ω, [IQR, -29 to 15 Ω]), increased RV capture threshold (median, 0 V, IQR, [0 to 0.2 Ω]), and decreased battery voltage (median, -0.01 V, IQR, -0.04 to 0 V) were noted. The observed changes did not require device revision or reprogramming.
Limitations:
Not all available cardiac devices have been tested. Long-term in-person or telephone follow-up was unavailable in 43 patients (10%), and some data were missing. Those with missing long-term capture threshold data had higher baseline right atrial and right ventricular capture thresholds and were more likely to have undergone thoracic imaging. Defibrillation threshold testing and random assignment to a control group were not performed.
Conclusion:
With appropriate precautions, MRI can be done safely in patients with selected cardiac devices. Because changes in device variables and programming may occur, electrophysiologic monitoring during MRI is essential.
More Related Videos
 08:19
Protocol for the Evaluation of MRI Artifacts Caused by Metal Implants to Assess the Suitability of Implants and the Vulnerability of Pulse Sequences
Published on: May 17, 2018
 06:29
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
Related Concept Videos
 01:24
Magnetic Resonance Imaging
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:27
Imaging Studies IV: Magnetic Resonance Imaging