Related Experiment Video
Updated: May 28, 2026

A Modified Technique for Arteriovenous Fistula Construction in Rabbits
Published on: February 10, 2023
Vascular access flow reduction for arteriovenous fistula salvage in symptomatic patients with central venous
William C Jennings1, Gregg A Miller, M Zachary Coburn
1Department of Surgery, College of Medicine, University of Oklahoma-Tulsa, Tulsa, OK 74135, USA. William-Jennings@ouhsc.edu

Insights
A precision inflow banding procedure effectively treated central venous stenosis in hemodialysis patients when angioplasty failed. This method preserved vascular access functionality and resolved symptoms, offering a viable solution for complex cases.
Area of Science:
- Vascular Surgery
- Nephrology
- Interventional Radiology
Background:
- Central venous stenosis or occlusion significantly impacts hemodialysis vascular access functionality and patient well-being.
- Conventional treatments like angioplasty and stenting for central venous lesions often face challenges with recurrence and non-correctability.
- Surgical bypass is invasive, and access ligation can lead to catheter dependency.
Purpose of the Study:
- To evaluate the efficacy of a precision inflow banding procedure for managing symptomatic central venous obstruction in hemodialysis patients.
- To assess the ability of this technique to limit vascular access flow and pressure while preserving access functionality.
Main Methods:
- Retrospective identification of patients with symptomatic central venous occlusive disease who underwent autogenous vascular access inflow restriction.
- All patients had previously failed angioplasty and stenting attempts.
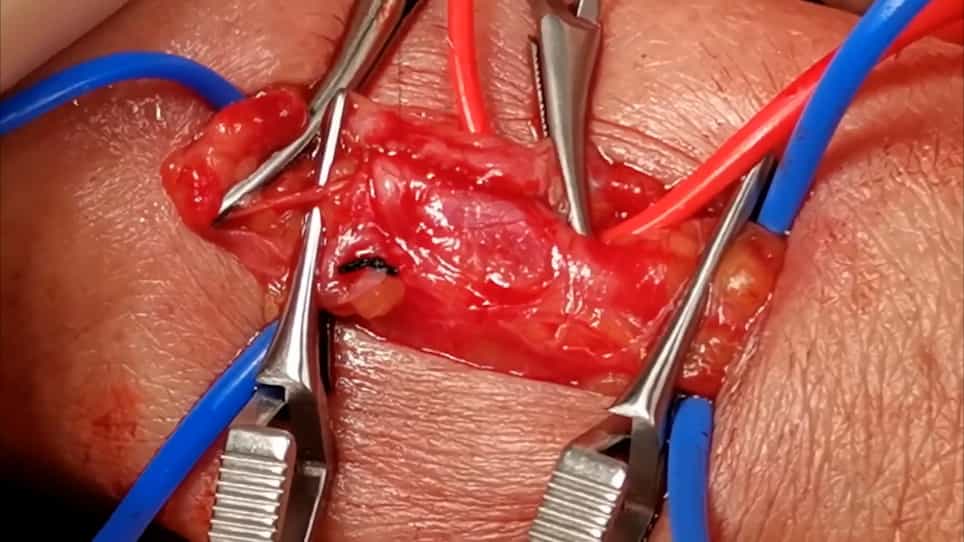
- A precision banding procedure was employed for access inflow reduction, incorporating real-time intravascular flow monitoring.
Main Results:
- Twenty-two patients (mean age 43 years) were included; 40.9% were women, 36.4% obese.
- Mean access flow significantly decreased from 1640 mL/minute to 820 mL/minute post-banding (P< .01).
- Access salvage was achieved in all patients, with prompt resolution of swelling in 20 individuals. Two fistulas failed after 8 and 13 months, with a mean follow-up of 8 months.
Conclusions:
- The precision inflow banding procedure successfully resolved symptoms associated with non-correctable central venous lesions in hemodialysis patients.
- This technique effectively maintained vascular access functionality, offering a valuable alternative for complex cases.
- The study highlights the procedure's role in salvaging vascular access and improving patient outcomes.
Purpose:
Vascular access patients with central vein (CV) stenosis or occlusion may have significant symptoms. Treatment is generally by balloon angioplasty, with or without stenting. However, CV lesions may not be correctable and when treated, tend to recur. Surgical bypass of CV obstruction is a major procedure and ligation of the access may leave the patient dependent on catheter dialysis. We review a precision inflow banding procedure to limit vascular access flow and pressure for symptomatic patients with CV obstruction while preserving access functionality.
Materials And Methods:
All individuals with symptomatic CV occlusive disease who underwent an autogenous vascular access inflow restriction procedure by the two senior authors were identified. All had failed attempts to correct CV lesions by angioplasty and stent placement. A precision banding procedure was used for access inflow reduction with the addition of real-time intravascular flow monitoring.
Results:
Twenty-two patients were identified. Ages were 22-72 years (mean=43 years). Nine patients (40.9%) were women, and 8 (36.4%) obese. Mean access flow was 1640 mL/minute before banding decreased to 820 mL/minute after banding (P< .01). All patients had access salvage. Swelling resolved promptly in 20 patients and was markedly improved in two individuals. Three patients underwent aneurysm repair with simultaneous inflow banding and decreased intra-access pressure after flow restriction. Two fistulas failed at eight and 13 months. Mean follow-up was 8 months.
Conclusions:
The symptoms of hemodialysis vascular access patients associated with non-correctable central venous lesions resolved successfully and their access was maintained using a precision inflow banding procedure.

Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care