Related Experiment Video
Updated: May 28, 2026


Hydra, a Computer-Based Platform for Aiding Clinicians in Cardiovascular Analysis and Diagnosis
Published on: September 26, 2018
Should preclinical vascular abnormalities be measured in asymptomatic adults to improve cardiovascular risk
Jacqueline de Graaf1, Suzanne Holewijn, Anton F Stalenhoef
1Division of Vascular Medicine, Department of Internal Medicine, Radboud University Nijmegen Medical Centre, Nijmegen, The Netherlands. j.degraaf@aig.umcn.nl

Insights
Noninvasive cardiovascular tests for intermediate-risk adults offer limited reclassification benefits. Routine screening is not advised; focus on individuals whose results will alter clinical care, particularly for statin initiation.
Area of Science:
- Cardiology
- Diagnostic Testing
- Preventive Medicine
Background:
- Conflicting guidelines exist on the utility of noninvasive tests for asymptomatic adults with intermediate cardiovascular risk.
- Reclassification of risk is a recent criterion for evaluating diagnostic test utility.
- This review assesses limitations in reclassification and the clinical utility of specific noninvasive tests.
Purpose of the Study:
- To examine limitations in risk reclassification by noninvasive tests.
- To evaluate the clinical utility of carotid ultrasound, pulse wave velocity, and ankle-brachial index.
- To provide a clinical perspective on the use of these diagnostic tools.
Main Methods:
- Review of existing literature and guideline recommendations.
- Analysis of the concept of risk reclassification in diagnostic testing.
- Clinical evaluation of carotid ultrasound, pulse wave velocity, and ankle-brachial index.
Main Results:
- Risk reclassification is less impactful than presumed, as many intermediate-risk patients already warrant therapy.
- Withholding treatment based on downgraded risk is uncertain, and intensified therapy offers marginal additional benefit.
- Noninvasive tests require improved reproducibility, standardization, and reference values for clinical integration.
Conclusions:
- Routine screening for all intermediate-risk individuals is not generally justified.
- Screening should target individuals where noninvasive tests alter clinical management, such as those with LDL < 2.5 mmol/L who may initiate statin therapy.
- The primary value of these tests lies in identifying preclinical disease rather than solely determining risk.
Purpose Of Review:
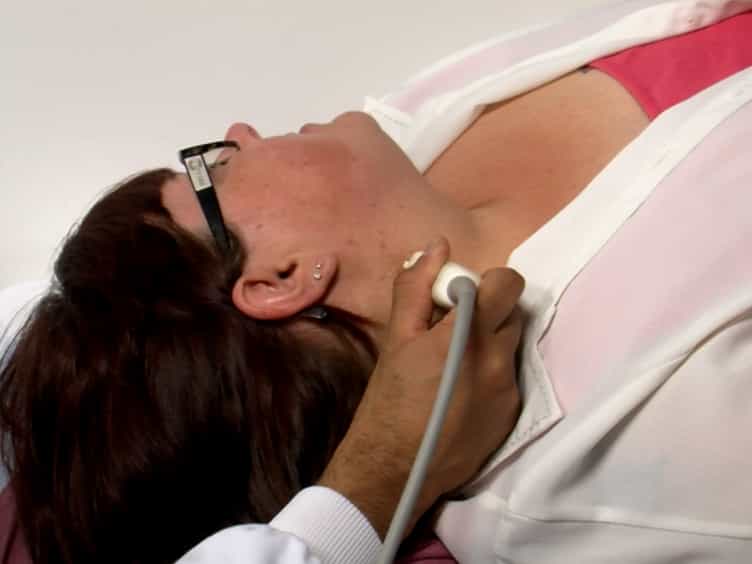
Guideline groups have issued contradictory decisions as to the value of noninvasive tests in asymptomatic adults at intermediate cardiovascular risk. Reclassification has only recently been accepted as a critical criterion to determine the utility of a diagnostic test. The present review examines potential limitations in reclassification and evaluates the utility of carotid ultrasound, pulse wave velocity and ankle brachial index from a clinical perspective.
Recent Findings:
Reclassification is less useful than generally believed, because therapy is already indicated in the majority of patients at intermediate risk and it is far from clear that treatment should be withheld in those who are downgraded in risk. Moreover, the additional benefit from more intensive therapy is much less than often thought. Reproducibility, standardization and reference values of noninvasive tests are obligatory before introduction in clinical care.
Summary:
Routine screening of all those at intermediate risk does not appear to be justified. Screening should be performed on those individuals in whom the noninvasive test changes clinical care, which is most apparent for individuals at intermediate risk with LDL level less than 2.5 mmol/l, in whom positive noninvasive tests will result in the start of statin treatment. The primary value of these tests should not be to determine risk but to identify preclinical anatomic disease.
Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Aneurysm III: Interprofessional Care
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation