Related Experiment Video
Updated: May 28, 2026


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Diaphragmatic hernia after laparoscopic esophagomyotomy for esophageal achalasia in pregnancy
Meena Khandelwal1, Chad Krueger
1Department of Obstetrics & Gynecology, Cooper University Hospital, University of Medicine & Dentistry of New Jersey, 1 Cooper Plaza, 623 Dorrance Building, Camden, NJ 08103, USA.

Background. The optimal treatment for management of esophageal achalasia in pregnancy is controversial. Little information exists about pregnancy outcome after successful myotomy. Case. Achalasia in pregnancy was diagnosed when a patient presented with pneumomediastinum from microrupture of the overdistended esophagus. An attempt at surgical correction failed due to the development of aspiration pneumonia with general anesthesia. Conservative medical therapy was undertaken, but fetal growth restriction developed. The patient underwent interval surgical correction, but subsequent pregnancy 6 months later was complicated by acute diaphragmatic hernia necessitating preterm delivery. Conclusion. Prior to surgery in pregnancy, emptying the dilated esophagus via nasoesophageal tube suctioning maybe warranted to avoid aspiration. Women, despite having undergone successful myotomy, should be counseled on the risks of pregnancy and to avoid pregnancy for at least 1 year thereafter.
Background. The optimal treatment for management of esophageal achalasia in pregnancy is controversial. Little information exists about pregnancy outcome after successful myotomy. Case. Achalasia in pregnancy was diagnosed when a patient presented with pneumomediastinum from microrupture of the overdistended esophagus. An attempt at surgical correction failed due to the development of aspiration pneumonia with general anesthesia. Conservative medical therapy was undertaken, but fetal growth restriction developed. The patient underwent interval surgical correction, but subsequent pregnancy 6 months later was complicated by acute diaphragmatic hernia necessitating preterm delivery. Conclusion. Prior to surgery in pregnancy, emptying the dilated esophagus via nasoesophageal tube suctioning maybe warranted to avoid aspiration. Women, despite having undergone successful myotomy, should be counseled on the risks of pregnancy and to avoid pregnancy for at least 1 year thereafter.


Related Concept Videos
 01:25
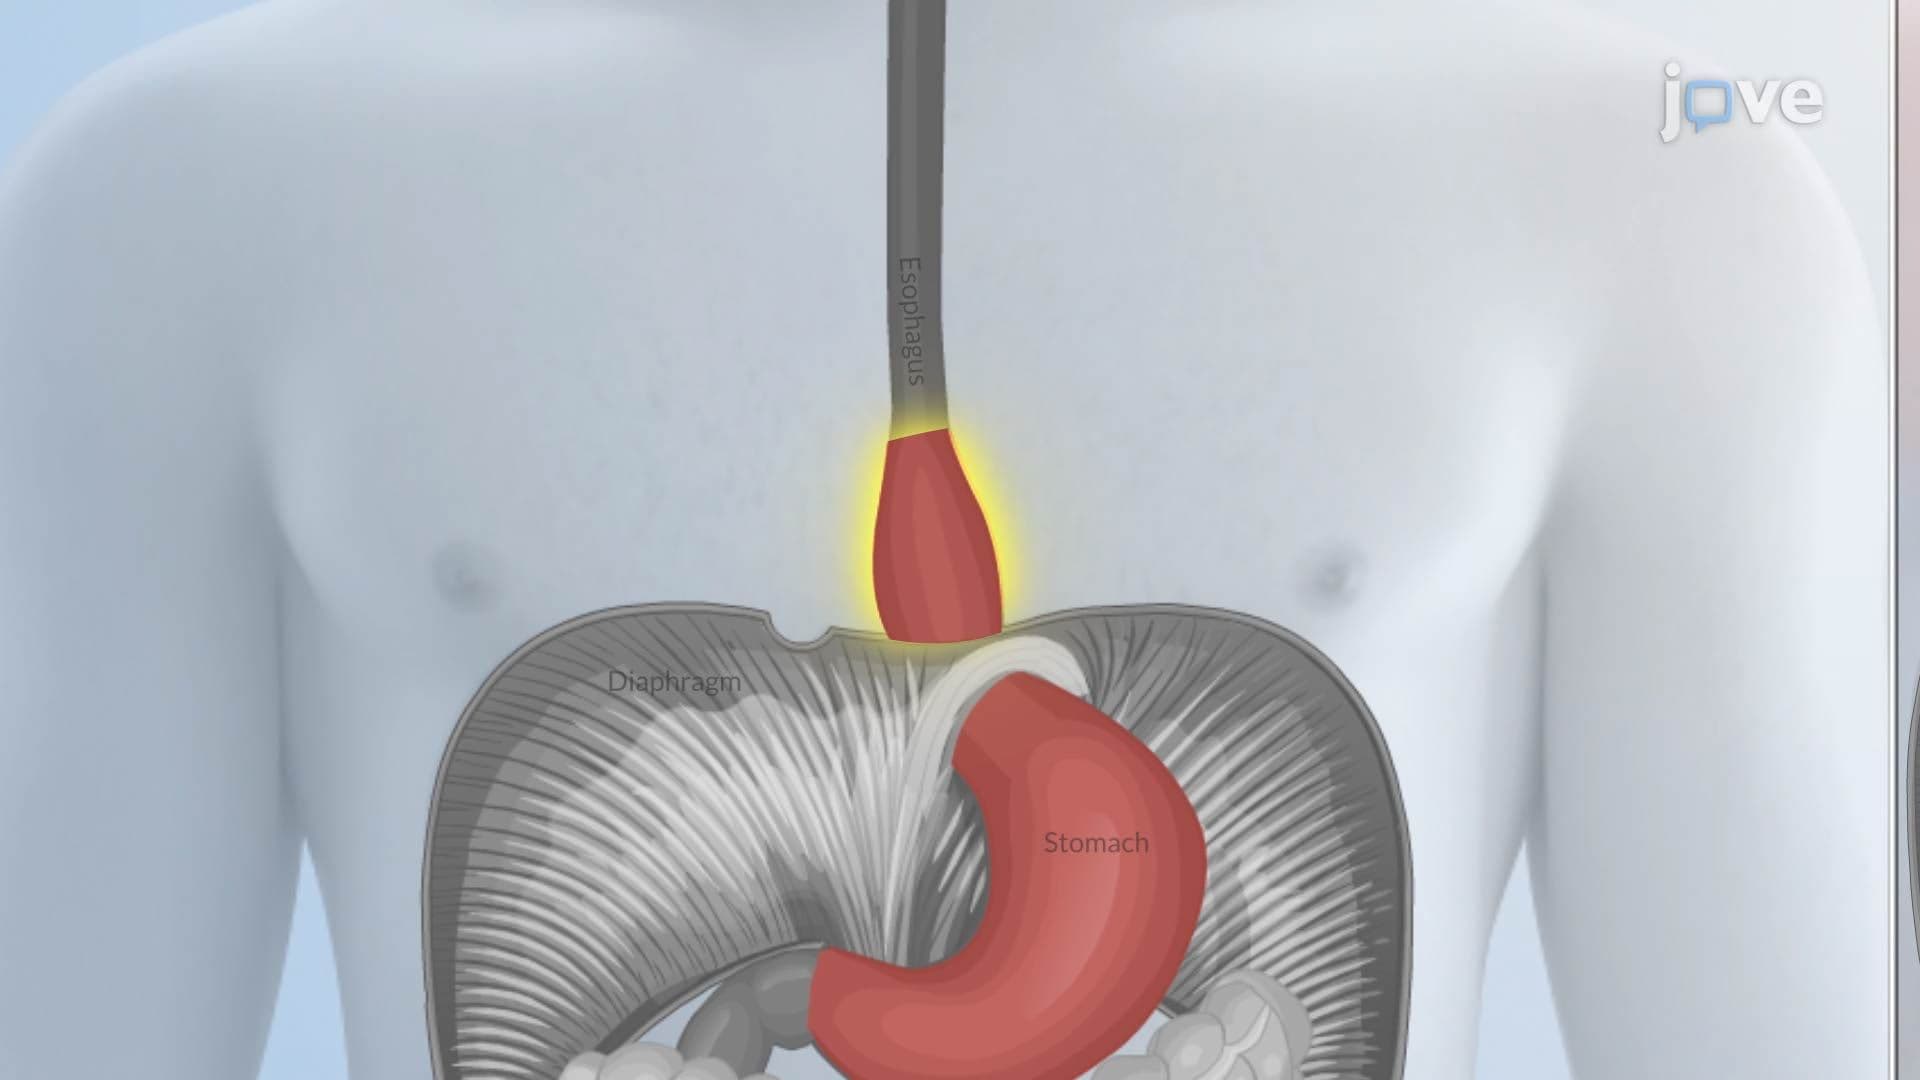
Hiatal Hernia
 01:27
Esophageal Achalasia
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...