Related Experiment Video
Updated: May 28, 2026


Three Dimensional Vestibular Ocular Reflex Testing Using a Six Degrees of Freedom Motion Platform
Published on: May 23, 2013
Three Similar But Unique Cases Of Isolated Superior Rectus ExtraOcular Muscle (EOM) Palsy Strabismus, Presenting With

Insights
Three pediatric patients with isolated superior rectus palsy underwent surgery. Initial surgery corrected head tilts, but a contralateral tilt developed, revealing underlying superior rectus palsy. Further surgery successfully addressed these rare cases.
Area of Science:
- Ophthalmology
- Pediatric Strabismus Surgery
Background:
- Isolated superior rectus (SR) palsy is rare in pediatric patients.
- Patients with SR palsy often present with compensatory head tilts.
Purpose of the Study:
- To describe three rare cases of isolated SR palsy in young children.
- To detail the surgical management and outcomes for these patients.
Main Methods:
- Three pediatric patients with head tilts underwent left inferior rectus (LIR) recession with nasal transposition.
- Two patients required subsequent right inferior rectus (RIR) recession for persistent SR palsy.
- One patient needed LIR advancement for weakness; two required inferior oblique weakening.
Main Results:
- Initial LIR recession corrected head tilts, but a contralateral tilt emerged in all patients.
- Secondary surgery successfully resolved remaining head tilts in all three cases.
- No lower lid retraction occurred post-operatively due to specialized surgical techniques.
Conclusions:
- Congenital hypoplasia of the superior rectus muscle is a potential cause of these SR palsy cases.
- The absence of blepharoptosis supports the hypothesis of congenital muscle hypoplasia.
- Advanced MRI techniques are needed for definitive diagnosis but are limited in young children.
Purpose:
To report 3 rare cases, seen over 15 years, of isolated superior rectus (SR) palsy in binocularly fusing pediatric patients presenting with appropriate head tilts.
Patients And Method:
All 3 children, ages 11, 16, and 34 mos, presented with large right head tilts and secondary overactions of the right inferior oblique indicating LSR palsy. All 3 children received recessions of the antagonist left inferior rectus (LIR) 8 to 9 mm with 3 mm of nasal transposition to prevent exotropia in down gaze.
Results:
All 3 children had zero head tilt 4 weeks after their LIR recessions of 8 to 9 mm, but all 3 children developed a significant contralateral left head tilt three months after their LIR recessions. Two of the 3 them three-stepped to produce a pattern of (previously occult) SR palsy. These 2 received recessions of the RIR 5.8 to 6.5 mm. One of the 3 had a pattern that indicated LIR weakness; his LIR was advanced 2.5 mm from a 9 mm recession to a 6.5 mm recession. No significant head tilts remained or developed anew after the second surgery, but two of the three cases eventually developed apparent primary overactions of the inferior obliques and received successful weakening procedures of the inferior obliques. Due to inclusion in each case of special handling of the intermuscular septa and Lockwoods ligament (for details see later text), none of the 3 children had lower lid retraction after the large IR recessions.
Conclusions:
In view of the fact that the superior division of the Third Cranial Nerve also innervates the adjacent levator and these three cases have had no blepharoptosis suggests that these apparently palsied superior rectus muscles may have been congenitally hypoplastic. Classic MRI (Magnetic Resonance Imaging) of the EOM by the techniques of Demer, to confirm this hypothesis, have not been available in these children, because of the current technical limitations of such diagnostic imaging in the case of young children who cannot maintain steady fixation for the time required.
Related Concept Videos
 01:20
Muscles of the Eye
Extraocular Muscles
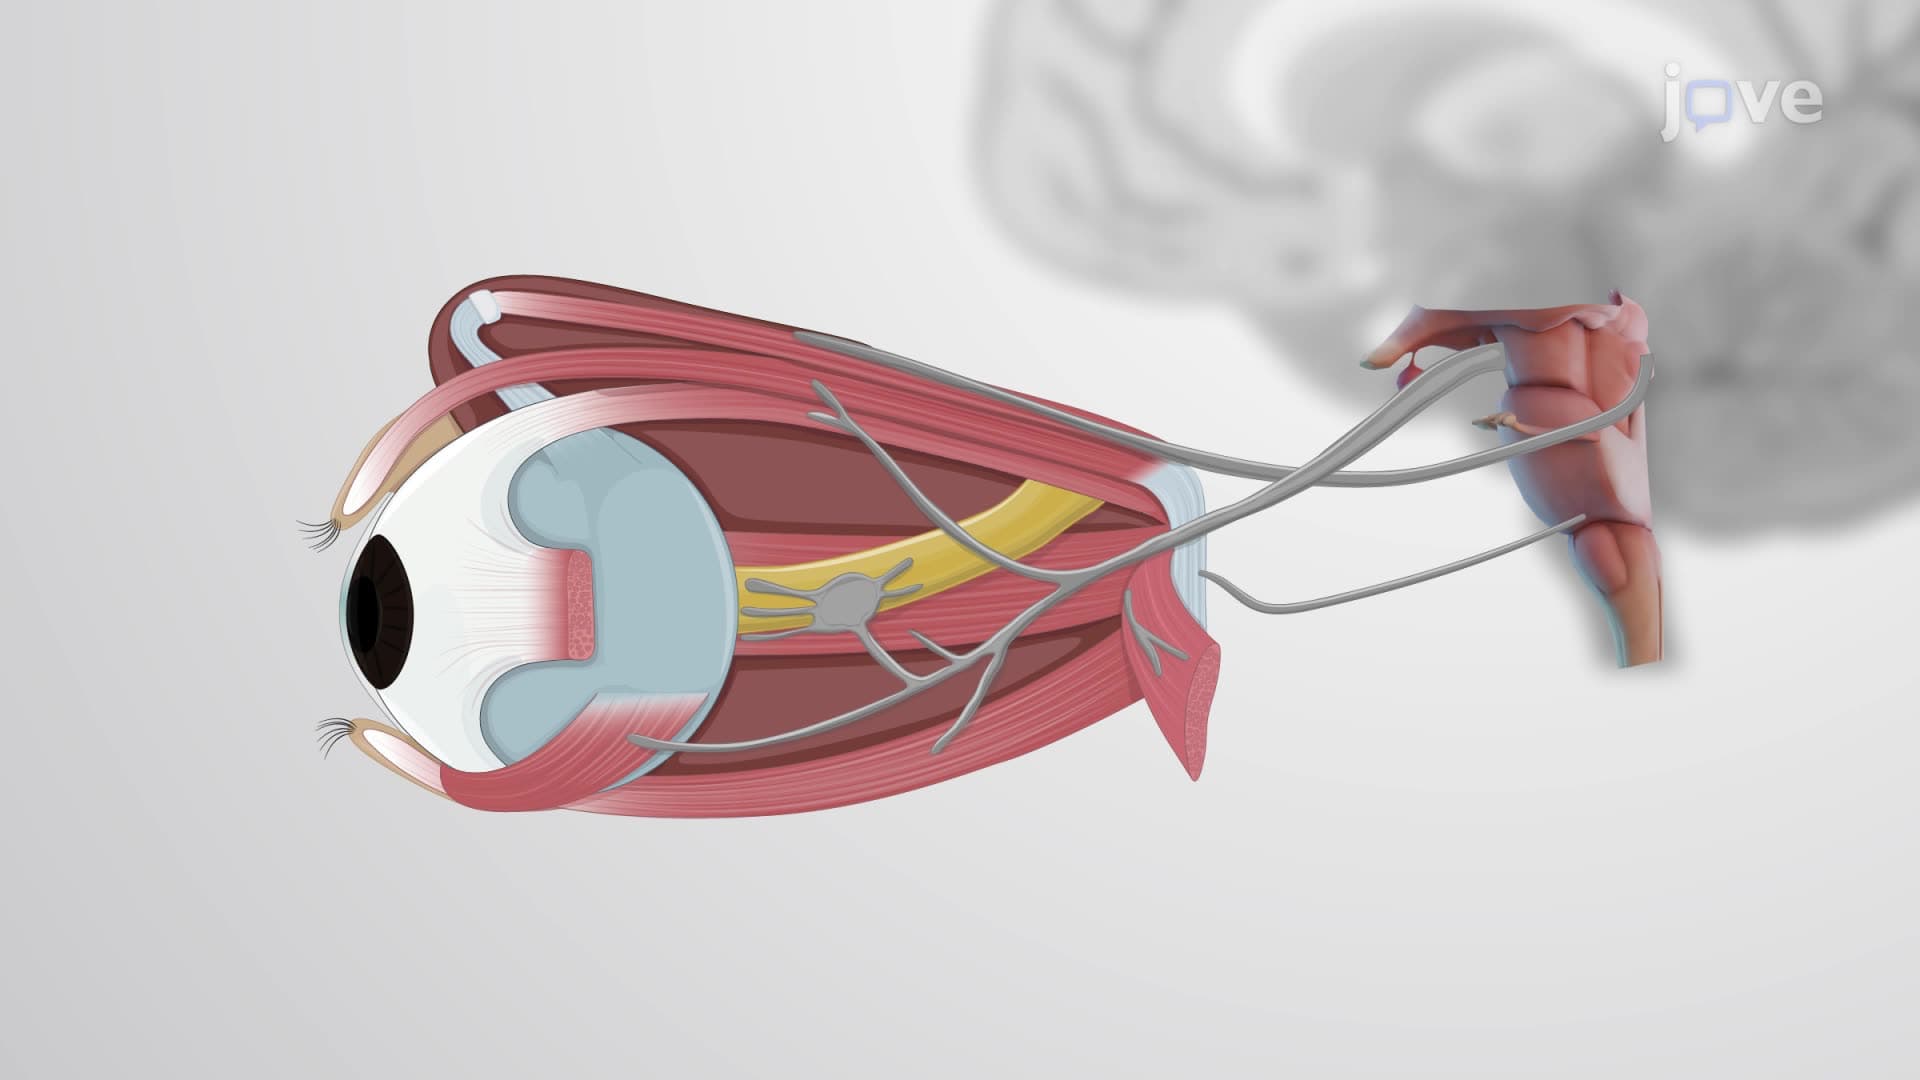
The six extraocular muscles surround the eyeball and control its movements. They are responsible for a wide range of eye motions, including looking up, down, left, right, and rotating...
 01:17
Accessory Structures of the Eye
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...