Related Experiment Video
Updated: May 28, 2026
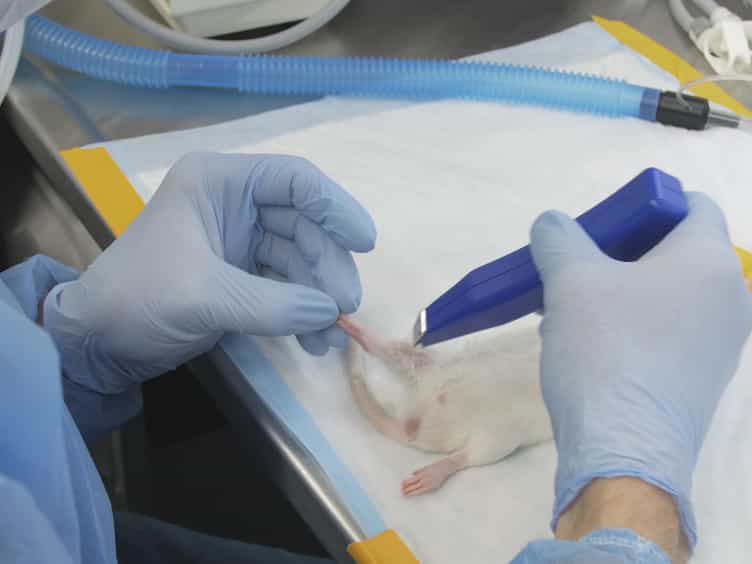
A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
Three-year growth hormone treatment in short children with X-linked hypophosphatemic rickets: effects on linear
M Živičnjak1, D Schnabel, H Staude
1Department of Pediatric Kidney, Liver, and Metabolic Diseases, Hannover Medical School, Carl-Neuberg-Strasse 1, 30625 Hannover, Germany. zivicnjak.miroslav@mh-hannover.de

Insights
Growth hormone (GH) treatment improved linear growth in children with X-linked hypophosphatemic rickets (XLH). This treatment enhanced stature and body segment lengths without worsening disproportionate stunting.
Area of Science:
- Pediatric Endocrinology
- Skeletal Dysplasias
- Growth Hormone Therapy
Background:
- X-linked hypophosphatemic rickets (XLH) causes progressive disproportionate stunting in children.
- Standard phosphate and vitamin D treatment is often insufficient to correct growth deficits.
Purpose of the Study:
- To evaluate the efficacy of growth hormone (GH) treatment on linear growth and body proportions in children with XLH.
- To compare growth outcomes in GH-treated XLH patients with a reference population.
Main Methods:
- A 3-year randomized controlled open-label study involving 16 prepubertal children with XLH receiving GH, phosphate, and calcitriol.
- A reference cohort of 76 XLH patients on conservative treatment was used for comparison.
- Changes in standard deviation scores (SDS) for stature and linear body segments (sitting height, leg length, arm length) and sitting height index were measured.
Main Results:
- XLH patients exhibited significant growth impairments at baseline, with leg length most affected.
- GH treatment led to sustained improvements in stature, sitting height, leg length, and arm length (P < 0.05 vs. baseline).
- The sitting height index remained stable in GH-treated patients, unlike the XLH reference population.
Conclusions:
- Three-year GH treatment effectively improved linear growth in short children with XLH.
- GH therapy demonstrated the potential to enhance growth without exacerbating body disproportion in XLH patients.
Context:
Children with X-linked hypophosphatemic rickets (XLH) are prone to progressive disproportionate stunting despite oral phosphate and vitamin D treatment.
Objective:
Our objective was to analyze the effects of GH treatment on stature and lengths of linear body segments in short children with XLH.
Design, Settings, And Patients:
A 3-yr randomized controlled open-label GH study in short prepubertal children with XLH (n = 16) on phosphate and calcitriol treatment was conducted. A cohort of XLH patients (n = 76) on conservative treatment served as an XLH reference population.
Main Outcome Measures:
Changes in SD scores (SDS) of stature and linear body segments, i.e. sitting height, leg and arm length, and sitting height index (i.e. ratio between sitting height and stature) were the main outcome measures.
Results:
XLH patients presented at time of enrollment with significant impairments of stature (-3.3 SDS) and linear body segments compared with healthy children. Leg length (-3.8 SDS) was most impaired, whereas sitting height (-1.7 SDS) was best preserved. The markedly elevated mean sitting height index (+3.3 SDS) reflected severe body disproportion. GH resulted in a sustained increase in linear growth (stature, +1.1 SDS; sitting height, +1.3 SDS; leg length, +0.8 SDS; arm length, +1.1 SDS; each P < 0.05 vs. baseline), whereas no significant changes were observed in controls. Mean height SDS at 3 yr did not significantly differ between groups. Sitting height index remained stable in both the GH-treated patients and in study controls but increased further in the XLH-reference population.
Conclusions:
The 3-yr GH treatment improved linear growth without progression of body disproportion in short children with XLH.
Related Concept Videos
 01:10
Nature and Nurture
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
Signs of Puberty
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism