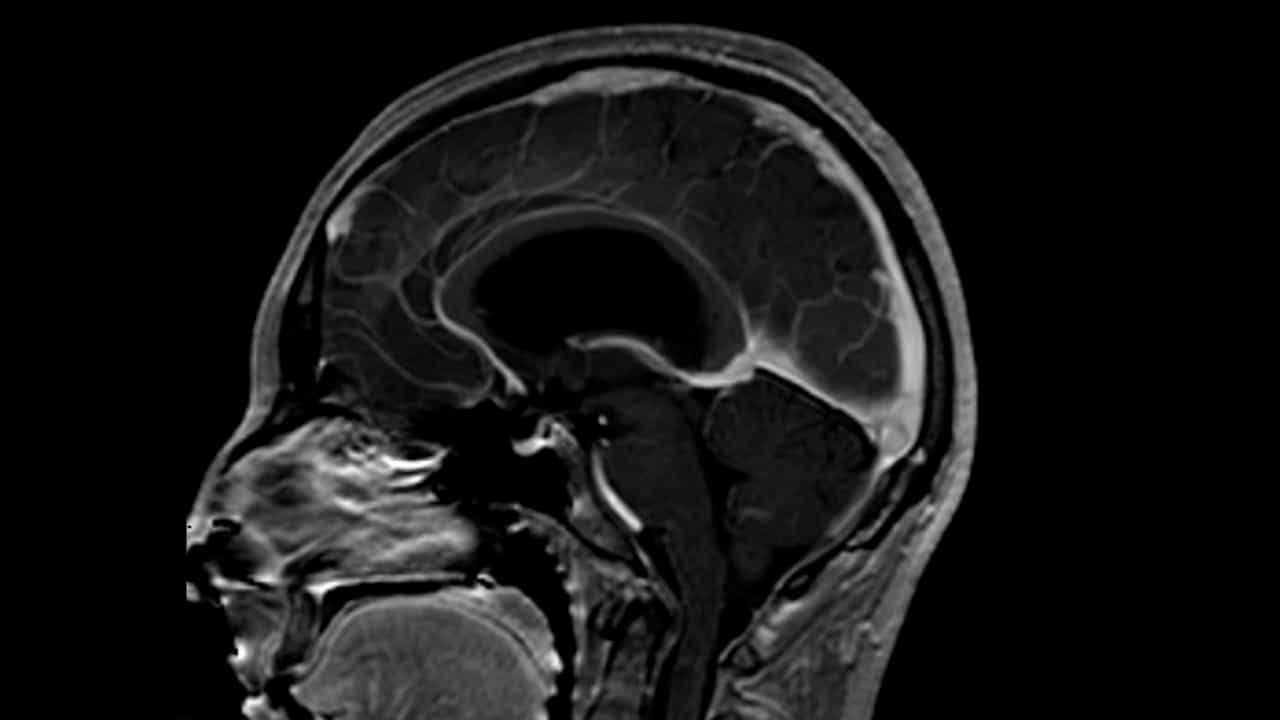
Atypical syncope in a child due to a colloid cyst of the third ventricle

Ethan M Goldberg1, Erin S Schwartz, Donald Younkin

  • 1Division of Neurology, Children's Hospital of Philadelphia, Philadelphia, Pennsylvania 19104, USA. goldberge@email.chop.edu

Pediatric Neurology
|October 18, 2011
PubMed

Related Concept Videos

Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Cerebral Edema l: Introduction01:19

Cerebral Edema l: Introduction

Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
Cytotoxic Edema: Pathophysiology01:21

Cytotoxic Edema: Pathophysiology

Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...
Aneurysm II: Clinical Manifestations and Diagnostic Studies01:21

Aneurysm II: Clinical Manifestations and Diagnostic Studies

Thoracic, aortic arch and abdominal aneurysms are significant vascular conditions that can present with various clinical manifestations and lead to serious complications. Understanding these manifestations and the appropriate diagnostic studies is essential for effective management and treatment.Thoracic Aortic AneurysmsThoracic aortic aneurysms often remain asymptomatic until they reach a size that impinges on adjacent structures. They typically cause deep, diffuse chest pain that radiates to...
Increased Intracranial Pressure ll: Pathophysiology01:29

Increased Intracranial Pressure ll: Pathophysiology

Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins with...
Pathophysiology of Vomiting01:22

Pathophysiology of Vomiting

Vomiting is a complex physiological response to expel harmful or irritating substances from the body. It's a defensive mechanism triggered by stimuli like poisons, microbial toxins, cytotoxic drugs, and mechanical abdominal distension. The process is centrally coordinated by the vomiting (or emetic) center located in the medulla of the brainstem. This area, rich in muscarinic M1, histamine H1, neurokinin 1 (NK1), and serotonin 5-HT3 receptors, coordinates the act of vomiting through interaction...