Related Experiment Videos
[Prediction of cerebrovascular event risk following myocardial infarction]
Sérgio Barra1, Rui Providência, Pedro Lourenço Gomes
1Serviço de Cardiologia, Centro Hospitalar de Coimbra, Coimbra, Portugal. sergioncbarra@gmail.com

Insights
Patients with myocardial infarction (MI) face increased stroke risk. Key predictors of stroke post-MI include elevated blood glucose and the GRACE score, not traditional cardiovascular risk factors.
Area of Science:
- Cardiology
- Neurology
- Clinical Medicine
Context:
- Patients with coronary artery disease (CAD) have a higher risk of stroke.
- Myocardial infarction (MI) survivors are particularly vulnerable to cerebrovascular events.
- Accurate stroke risk prediction post-MI is crucial for effective secondary prevention.
Purpose:
- To evaluate the prognostic accuracy of clinical and laboratory variables for stroke risk prediction in patients after MI.
- To identify key predictors of stroke or transient ischemic attack (TIA) within two years of MI discharge.
- To determine if traditional cardiovascular risk factors improve stroke risk prediction beyond established mortality scores.
Summary:
- A study of 404 MI patients found that elevated admission blood glucose (BG) and the GRACE score for 6-month mortality were significant independent predictors of stroke.
- Variables like GFR <60ml/min/m(2), Killip class >1, and peak troponin >42ng/ml were also associated with increased stroke risk.
- Traditional cardiovascular risk factors, prior CAD, and extent of CAD did not improve stroke risk prediction.
Impact:
- Identifies specific biomarkers and scores (admission BG, GRACE score) for enhanced stroke risk stratification in post-MI patients.
- Suggests that current stroke risk prediction models for CAD patients may need refinement.
- Highlights the need for more aggressive secondary prevention strategies in high-risk MI survivors.
Introduction:
Patients with coronary artery disease (CAD) are at increased risk of stroke. The aim of this study was to analyze the prognostic accuracy of selected clinical and laboratory variables in stroke risk prediction following discharge after myocardial infarction (MI).
Methods:
We analyzed 404 consecutive patients (aged 68.1±13.7 years; 63.4% male; 37.4% with diabetes) without previous stroke who were discharged in sinus rhythm after being admitted for MI. The following data were collected: cardiovascular risk factors, admission blood glucose (BG), HbA1c, creatinine, peak troponin levels; glomerular filtration rate (GFR) by the MDRD formula; maximum Killip class; GRACE score for in-hospital and 6-month mortality; and extent of CAD. Patients were followed for two years and each variable was tested as a possible predictor of cerebrovascular events (stroke or transient ischemic attack [TIA]).
Results:
During follow-up, 27 patients were admitted for stroke or TIA. The presence of diabetes, hypertension, dyslipidemia and previously known CAD, type of MI (STEMI vs NSTEMI) and extent of CAD did not predict cerebrovascular risk. The following variables were associated with higher stroke risk: GFR <60ml/min/m(2) (p=0.029, OR 2.65, 95% CI 1.07-6.55); maximum Killip class >1 (p=0.025, OR 2.71, 95% CI 1.10-6.69); GRACE in-hospital mortality >180 (p=0.001, OR 4.09, 95% CI 1.64-10.22); admission BG >140 mg/dl (p=0.001, OR 5.74, 95% CI 1.87-17.58); GRACE 6-month mortality >150 (p=0.001, OR 4.50, 95% CI 1.80-6.27); and peak troponin >42ng/ml (p=0.032, OR 2.64, 95% CI 1.06-6.59). Logistic regression analysis produced a model with the predictors GRACE 6-month mortality >150 (OR 3.26; p=0.014) and admission BG >7.7mmol/l (OR 4.09; p=0.017) that fitted the data well (Hosmer-Lemeshow: p=0.916).
Discussion/Conclusions:
In patients with MI, variables known to be predictors of in-hospital mortality, including admission BG, renal function, acute heart failure and GRACE score, were found to be useful predictors of stroke during 2-year follow-up. While both GRACE score for 6-month mortality >150 and admission BG >7.7 mmol/l were independent predictors of stroke, CV risk factors, previously known CAD, and extent of CAD assessed by coronary angiography did not improve stroke risk prediction. This study highlights the need for even more aggressive secondary prevention in patients most at risk.
Related Concept Videos
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:26
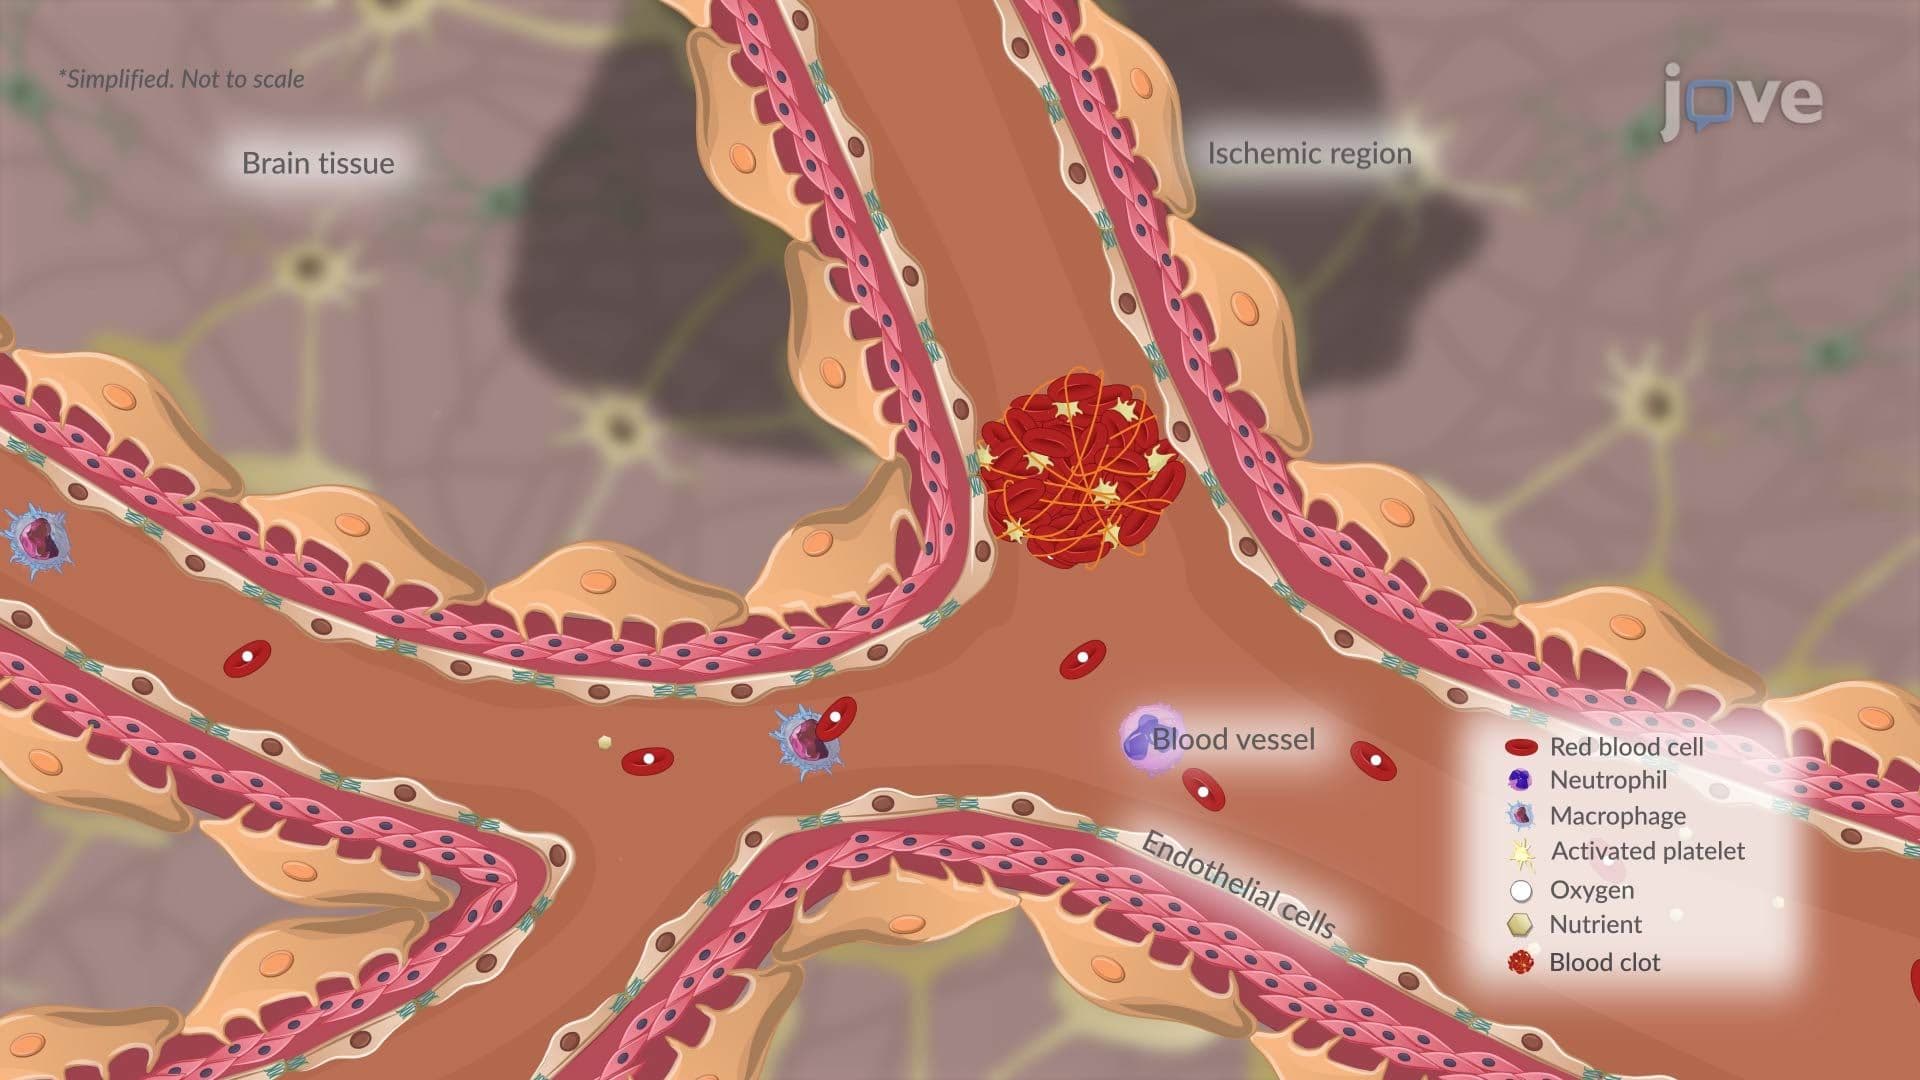
Transient Ischemic Attack l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:26
Coronary Artery Disease IV: Preventive Measures