Related Experiment Video
Updated: May 28, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Effects of oxygen on exertional dyspnoea and exercise performance in patients with chronic obstructive pulmonary
Keisuke Miki1, Ryoji Maekura, Toru Hiraga
1Department of Internal medicine, National Hospital Organization Toneyama National Hospital, Toyonaka, Osaka, Japan. mikisuke@toneyama.go.jp

Background And Objective:
The results of studies on the oxygen response in patients with COPD should provide important clues to the pathophysiology of exertional dyspnoea. We investigated the exercise responses to hyperoxia in relation to dyspnoea profile, as well as cardiopulmonary, acidotic and sympathetic parameters in 35 patients with stable COPD (mean FEV(1) 46% predicted).
Methods:
This was a single-blind trial, in which patients breathed 24% O(2) or compressed air (CA) in random order during two incremental cycle exercise tests.
Results:
PaO(2) and PaCO(2) were higher (P < 0.0001 and P < 0.05, respectively) at each exercise point while patients were breathing 24% O(2) compared with CA. At a standardized time point near peak exercise, use of O(2) resulted in reduced plasma lactate and plasma noradrenaline concentrations (P < 0.01). Peak minute ventilation/indirect maximum voluntary ventilation was similar while breathing 24% O(2) and CA. At peak exercise, the dyspnoea score, pH and plasma noradrenaline concentrations were similar while breathing 24% O(2) and CA. The dyspnoea-ratio (%) of Δoxygen uptake (peak minus resting oxygen uptake) curve reached a break point that occurred at a similar exercise point while breathing 24% O(2) or CA.
Conclusions:
Regardless of whether they breathed CA or 24% O(2) , patients with COPD did not develop ventilatory compensation for exertional acidosis, and the pH values measured were similar. Hyperoxia during a standardized exercise protocol did not alter the pattern of exertional dyspnoea in these patients, compared with breathing CA, although hyperoxia resulted in miscellaneous effects.
More Related Videos
 08:44
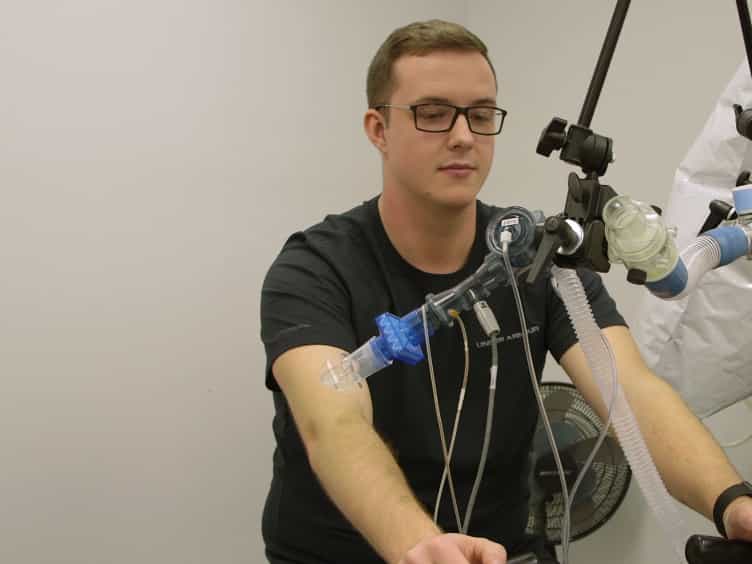
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:27
Oxygen Transport in the Blood
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction