Related Experiment Video
Updated: May 28, 2026
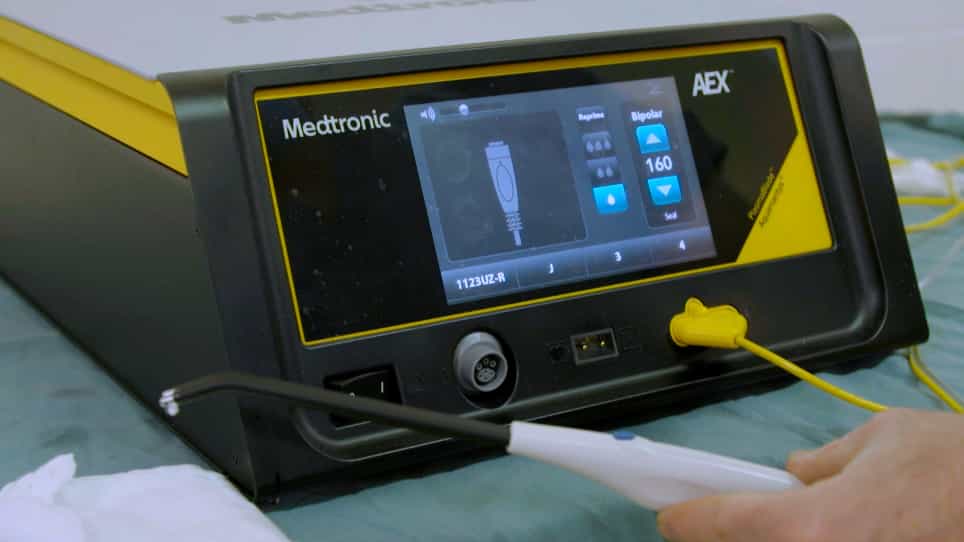
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Management of major trauma haemorrhage: treatment priorities and controversies
1Trauma Sciences, Blizard Institute, Bart's and the London School of Medicine & Dentistry, Queen Mary University of London, London, UK. ross.davenport@bartsandthelondon.nhs.uk

The severely injured trauma patient often arrives in the emergency department bleeding, coagulopathic and in need of a blood transfusion. The diagnosis and management of these patients has vastly improved with a better understanding of acute traumatic coagulopathy (ATC). In the emergency setting, traditional laboratory coagulation screens are of limited use in the diagnosis and management of life-threatening bleeding. Whole blood assays, such as thrombelastography (TEG) and rotational thrombelastometry (ROTEM) provide a rapid evaluation of clot formation, strength and lysis. Rapid diagnosis of ATC and aggressive haemostatic transfusion strategies utilizing early high doses of plasma are associated with improved outcomes in trauma. At present there is no accurate guide for transfusion in trauma, therefore blood and clotting products are administered on an empiric basis. Targeted transfusion therapy for major trauma haemorrhage based on comprehensive and rapid measures of coagulation e.g. TEG/ROTEM may lead to improved outcomes while optimizing blood utilization. Evidence for the clinical application of TEG and ROTEM in trauma is emerging with a number of studies evaluating their ability to diagnose coagulopathy early and facilitate goal-directed transfusion. This review explores current controversies and best practice in the diagnosis and management of major haemorrhage in trauma.
The severely injured trauma patient often arrives in the emergency department bleeding, coagulopathic and in need of a blood transfusion. The diagnosis and management of these patients has vastly improved with a better understanding of acute traumatic coagulopathy (ATC). In the emergency setting, traditional laboratory coagulation screens are of limited use in the diagnosis and management of life-threatening bleeding. Whole blood assays, such as thrombelastography (TEG) and rotational thrombelastometry (ROTEM) provide a rapid evaluation of clot formation, strength and lysis. Rapid diagnosis of ATC and aggressive haemostatic transfusion strategies utilizing early high doses of plasma are associated with improved outcomes in trauma. At present there is no accurate guide for transfusion in trauma, therefore blood and clotting products are administered on an empiric basis. Targeted transfusion therapy for major trauma haemorrhage based on comprehensive and rapid measures of coagulation e.g. TEG/ROTEM may lead to improved outcomes while optimizing blood utilization. Evidence for the clinical application of TEG and ROTEM in trauma is emerging with a number of studies evaluating their ability to diagnose coagulopathy early and facilitate goal-directed transfusion. This review explores current controversies and best practice in the diagnosis and management of major haemorrhage in trauma.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care