Related Experiment Video
Updated: May 28, 2026
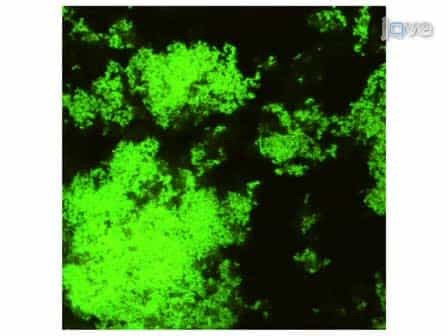

In vitro Biofilm Formation in an 8-well Chamber Slide
Published on: January 20, 2011
Multi-species bacterial biofilm and intracellular infection in otitis media
Ruth B Thornton1, Paul J Rigby, Selma P Wiertsema
1School of Paediatrics and Child Health, The University of Western Australia, Perth, Western Australia, Australia. rthornton@meddent.uwa.edu.au

Background:
Bacteria which are metabolically active yet unable to be cultured and eradicated by antibiotic treatment are present in the middle ear effusion of children with chronic otitis media with effusion (COME) and recurrent acute otitis media (rAOM). These observations are suggestive of biofilm presence or intracellular sequestration of bacteria and may play a role in OM pathogenesis. The aim of this project is to provide evidence for the presence of otopathogenic bacteria intracellularly or within biofilm in the middle ear mucosa of children with COME or rAOM.
Methods:
Middle ear mucosal biopsies from 20 children with COME or rAOM were examined for otopathogenic bacteria (either in biofilm or located intracellularly) using transmission electron microscopy (TEM) or species specific fluorescent in situ hybridisation (FISH) and confocal laser scanning microscopy (CLSM). One healthy control biopsy from a child undergoing cochlear implant surgery was also examined.
Results:
No bacteria were observed in the healthy control sample. In 2 of the 3 biopsies imaged using TEM, bacteria were observed in mucus containing vacuoles within epithelial cells. Bacterial species within these could not be identified and biofilm was not observed. Using FISH with CLSM, bacteria were seen in 15 of the 17 otitis media mucosal specimens. In this group, 11 (65%) of the 17 middle ear mucosal biopsies showed evidence of bacterial biofilm and 12 demonstrated intracellular bacteria. 52% of biopsies were positive for both biofilm and intracellular bacteria. At least one otopathogen was identified in 13 of the 15 samples where bacteria were present. No differences were observed between biopsies from children with COME and those with rAOM.
Conclusion:
Using FISH and CLSM, bacterial biofilm and intracellular infection with known otopathogens are demonstrated on/in the middle ear mucosa of children with COME and/or rAOM. While their role in disease pathogenesis remains to be determined, this previously undescribed infection pattern may help explain the ineffectiveness of current treatment strategies at preventing or resolving COME or rAOM.
Insights
Bacteria form biofilms and hide inside cells in children with chronic or recurrent ear infections, explaining why treatments often fail. This study found evidence of these hidden bacterial infections in middle ear tissues.
Area of Science:
- Microbiology
- Otolaryngology
- Pediatric Infectious Diseases
Background:
- Bacteria in middle ear effusion of children with chronic otitis media with effusion (COME) and recurrent acute otitis media (rAOM) are difficult to culture and eradicate.
- These persistent bacteria may exist in biofilms or intracellularly, potentially contributing to otitis media (OM) pathogenesis.
Purpose of the Study:
- To provide evidence for intracellular or biofilm-associated otopathogenic bacteria in the middle ear mucosa of children diagnosed with COME or rAOM.
Main Methods:
- Middle ear mucosal biopsies from 20 children with COME or rAOM were analyzed.
- Techniques included transmission electron microscopy (TEM), fluorescent in situ hybridization (FISH), and confocal laser scanning microscopy (CLSM).
- A healthy control biopsy was also examined.
Main Results:
- No bacteria were detected in the healthy control.
- TEM revealed intracellular bacteria in 2 of 3 COME/rAOM biopsies, but biofilm was not observed.
- FISH/CLSM detected bacteria in 15 of 17 COME/rAOM biopsies.
- Bacterial biofilm was present in 11 (65%) and intracellular bacteria in 12 (71%) of the 17 biopsies.
- 52% of biopsies showed both biofilm and intracellular bacteria.
- Otopathogens were identified in 13 of 15 positive samples.
Conclusions:
- Bacterial biofilm and intracellular infections by otopathogens are present in the middle ear mucosa of children with COME and/or rAOM.
- This infection pattern, previously undescribed, may explain the limited efficacy of current treatment strategies for COME and rAOM.
- Further research is needed to determine the precise role of these findings in disease pathogenesis.
Related Concept Videos
 01:29
Biofilms
 01:29
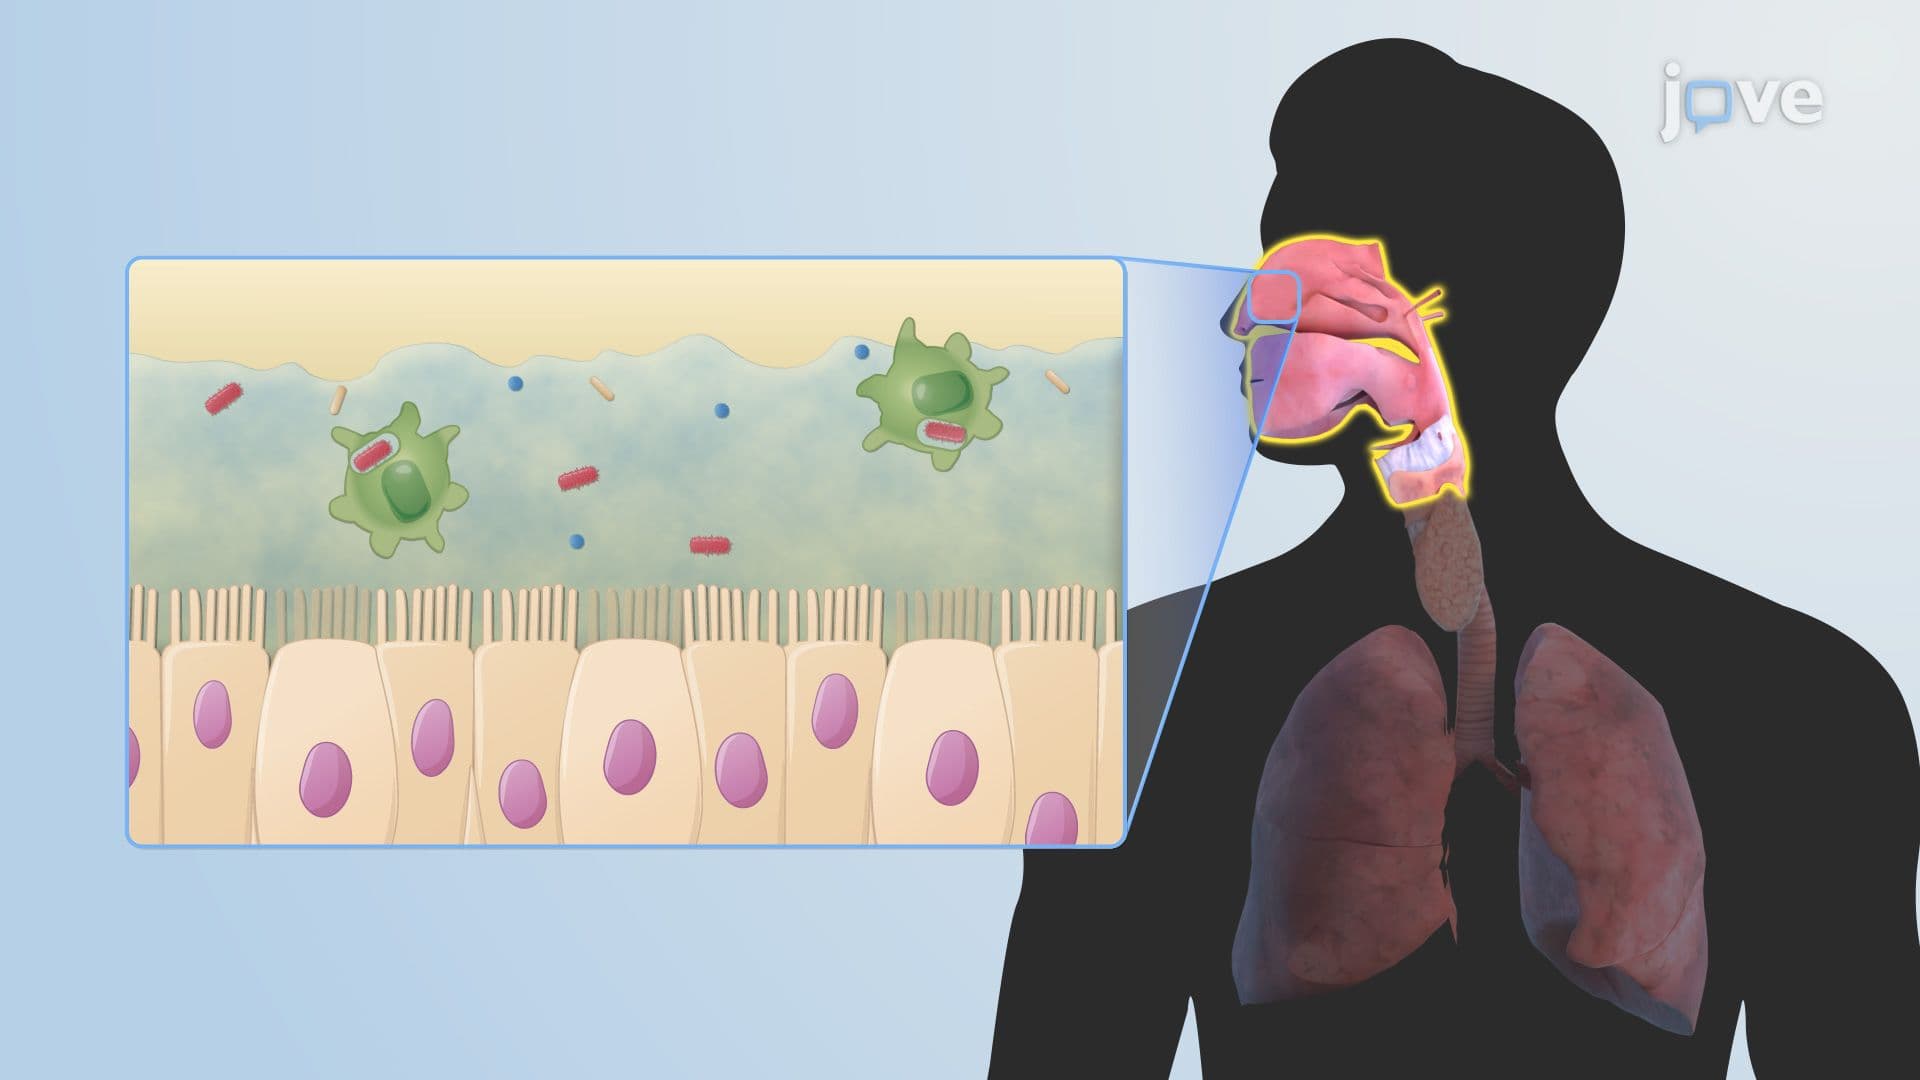
Microbiota of the Respiratory Tract
 01:22
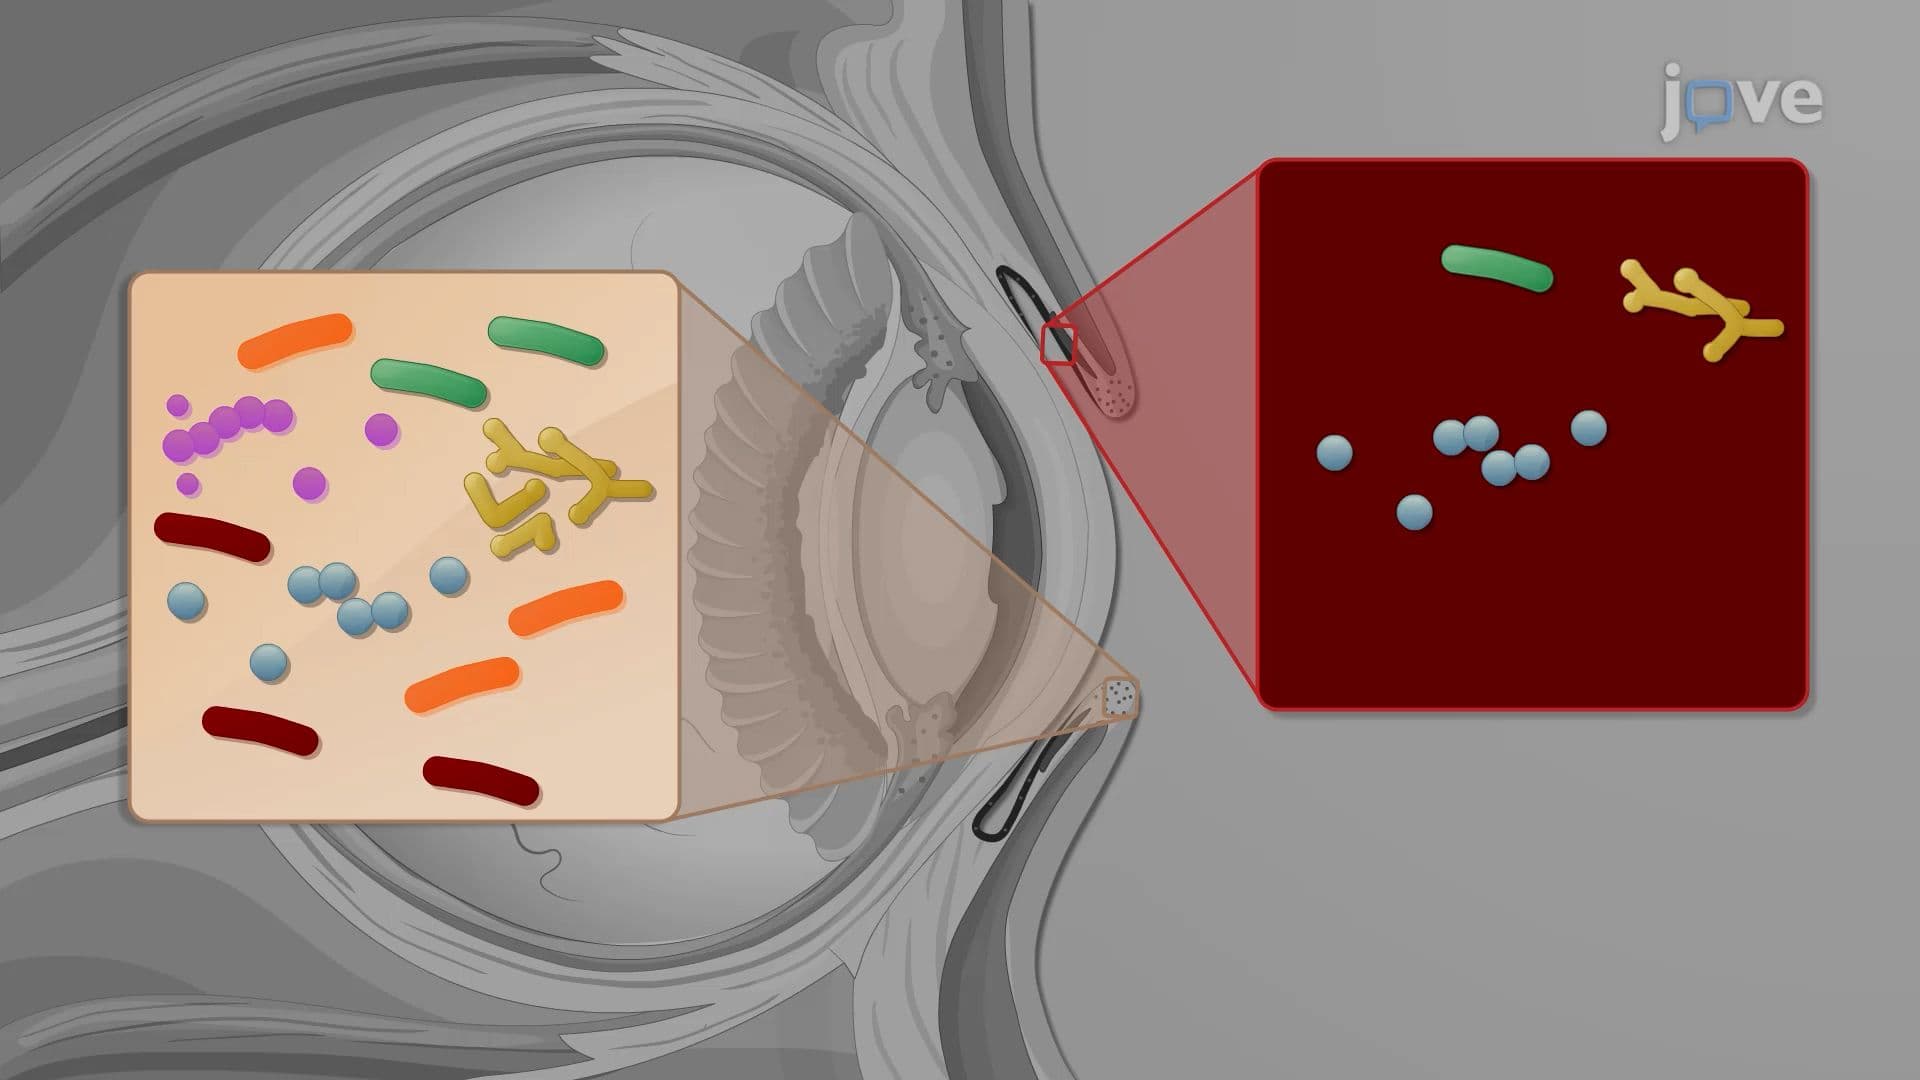
Microbiome of the Eye