Related Experiment Video
Updated: May 28, 2026
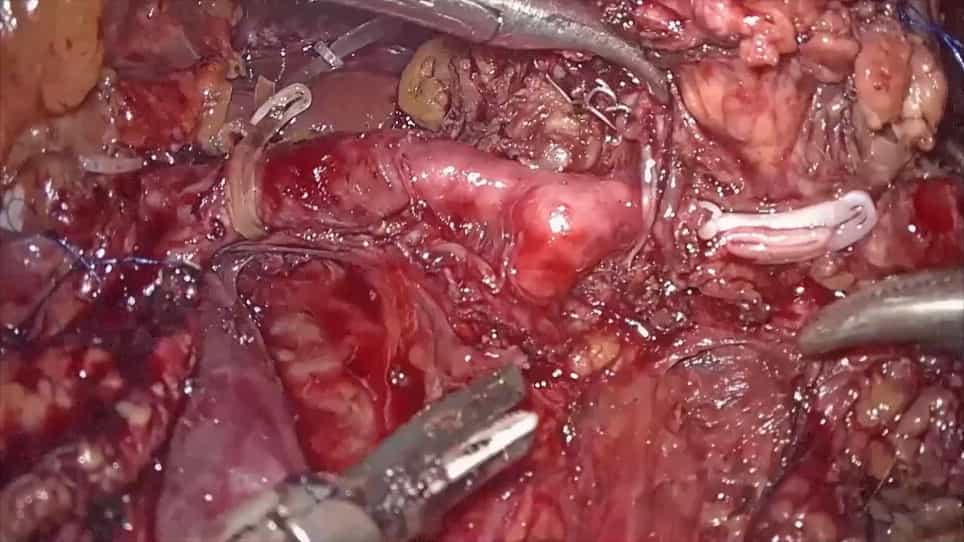
Laparoscopic Radical Antegrade Modular Pancreatosplenectomy via Dorsal-Caudal Artery Approach for Pancreatic Neck-Body Cancer
Published on: November 18, 2022
Long-term outcomes of neoadjuvant chemotherapy before chemoradiation for locally advanced pancreatic cancer
Nils D Arvold1, David P Ryan, Andrzej Niemierko
1Harvard Radiation Oncology Program, Boston, Massachusetts, USA.

Background:
Neoadjuvant chemotherapy before chemoradiation therapy (CRT) may improve outcomes for patients with locally advanced pancreatic cancer, but optimal management remains controversial, and prior reports have limited follow-up.
Methods:
Seventy consecutive patients with unresectable (n = 46) or borderline resectable (n = 24) locally advanced pancreatic cancer were treated with CRT from 2005 to 2009. Patients typically received 50.4 grays in 28 fractions (91%) with concurrent 5-fluorouracil (84%) or capecitabine (14%). Forty patients received CRT alone, and 30 patients received neoadjuvant chemotherapy before CRT for a median of 4 months, typically gemcitabine (93%). All patients without progression after neoadjuvant chemotherapy were offered CRT.
Results:
Median follow-up was 14.2 months (range, 3-57 months). Fifty-three percent of patients in the CRT group versus 83% in the neoadjuvant chemotherapy before CRT group had unresectable tumors at diagnosis; after completion of CRT, 20% of patients in both groups underwent resection. Compared with CRT alone, the neoadjuvant chemotherapy before CRT group demonstrated improved median overall survival (OS; 18.7 vs 12.4 months; P = .02) and progression-free survival (11.4 vs 6.7 months; P = .02). On multivariate analysis, receipt of neoadjuvant chemotherapy (adjusted hazard ratio [HR], 0.49; 95% CI, 0.28-0.87; P = .02) and surgical resection (adjusted HR, 0.38; 95% CI, 0.17-0.85; P = .02) were associated with increased OS.
Conclusions:
Gemcitabine-based neoadjuvant chemotherapy confers a significant OS advantage by allowing the selection of patients who will derive greatest benefit from CRT. Median survival with this approach was similar to that seen with surgical resection.
