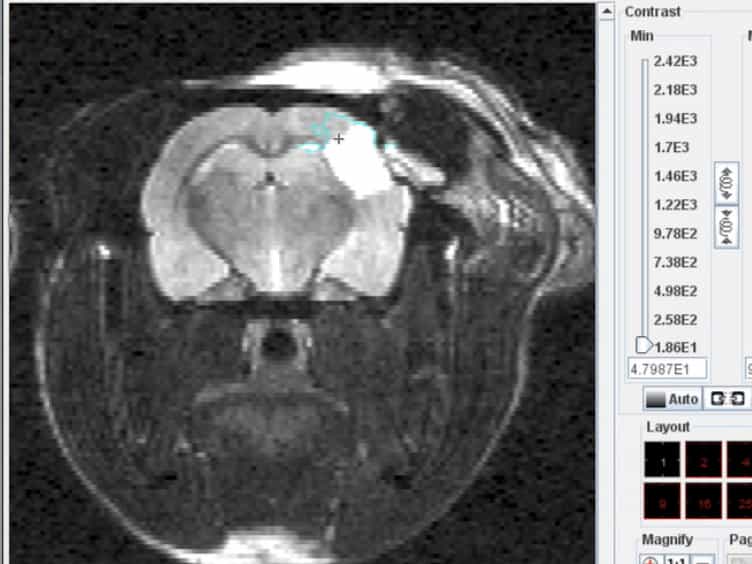

Pure motor monoparesis due to ischemic stroke
1Department of Neurology, Chiba Rosai Hospital, 2-16 Tatsumidai-Higashi, Ichihara-shi, Chiba, Japan. hiragaa@yahoo.co.jp

Background:
Pure motor monoparesis (PMM), an isolated motor deficit that occurs after ischemic stroke (IS) in a single arm or leg without accompanying cranial or sensory dysfunction, is rare and easily misdiagnosed as other causes of weakness.
Review Summary:
Cortical infarctions of the precentral knob and the anterior cerebral artery territory (for upper and lower limbs, respectively) are the most commonly reported lesion sites in PMM. Other sites include the subcortex, corona radiata, internal capsule, and brainstem; these sites are cited less frequently than those afflicted by cortical infarctions. PMM shows a complex weakness pattern; however, distal-dominant weakness, as well as the absence of pyramidal signs is most commonly observed in PMM owing to IS. Nevertheless, the overall prognosis is generally good.
Conclusions:
Physicians should carefully assess acute monoparesis, particularly in elderly patients with conventional risk factors, and should include IS in the differential diagnosis. Diffusion-weighted imaging is the most useful tool for diagnosing PMM owing to IS.
Insights
Pure motor monoparesis (PMM) following ischemic stroke (IS) is rare and often misdiagnosed. Early diagnosis using diffusion-weighted imaging is crucial for effective treatment and good prognosis.
Area of Science:
- Neurology
- Stroke Medicine
- Neuroimaging
Background:
- Pure motor monoparesis (PMM) is an uncommon ischemic stroke (IS) presentation.
- Characterized by isolated motor deficit in one limb without cranial or sensory deficits.
- Often misdiagnosed, delaying appropriate stroke management.
Purpose of the Study:
- To highlight the diagnostic challenges of PMM secondary to IS.
- To identify common lesion locations and clinical features of PMM.
- To emphasize the importance of early recognition and diagnosis.
Main Methods:
- Review of literature on pure motor monoparesis following ischemic stroke.
- Analysis of lesion sites, clinical presentations, and diagnostic tools.
- Focus on diffusion-weighted imaging (DWI) utility.
Main Results:
- Cortical lesions (precentral knob, anterior cerebral artery territory) are most common.
- Subcortical, corona radiata, internal capsule, and brainstem lesions are less frequent.
- Distal-dominant weakness without pyramidal signs is characteristic; prognosis is generally favorable.
Conclusions:
- Acute monoparesis warrants careful evaluation, especially in elderly patients with stroke risk factors.
- Ischemic stroke should be considered in the differential diagnosis of acute monoparesis.
- Diffusion-weighted imaging is the key diagnostic modality for PMM due to IS.
Related Concept Videos
 01:15
Ischemic Stroke l: Introduction
 01:26
Transient Ischemic Attack l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Poliomyelitis