Related Experiment Video
Updated: May 28, 2026
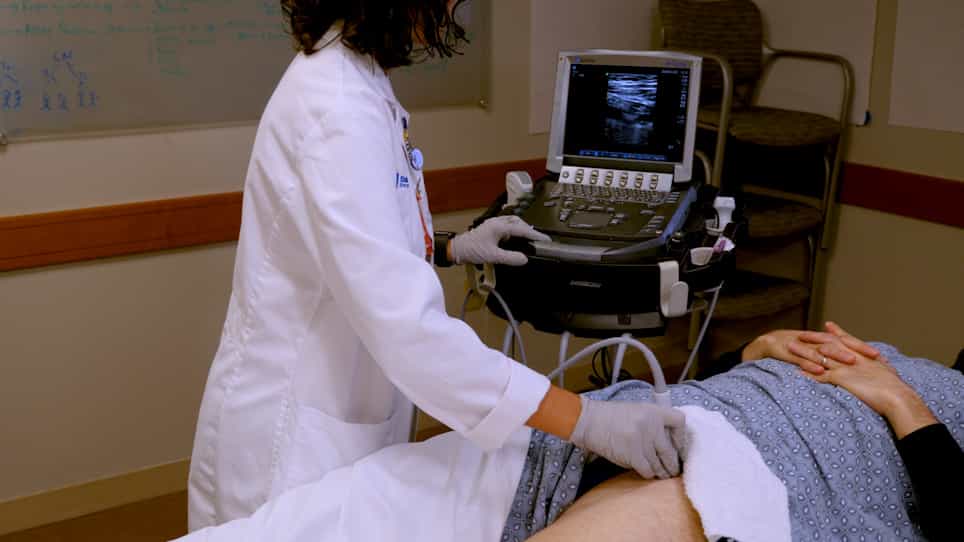

Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Risk factors for venous thromboembolism in critically ill trauma patients who cannot receive chemical prophylaxis
Darren Malinoski1, Tyler Ewing, Madhukar S Patel
1Department of Surgery, Cedars-Sinai Medical Center, USA. darren.malinoski@cshs.org

Background:
Standard venous thromboembolism (VTE) prevention for critically ill trauma patients includes sequential compression devices and chemical prophylaxis. When contraindications to anticoagulation are present, prophylactic inferior vena cava filters (IVCF) may be used to prevent pulmonary emboli (PE) in high-risk patients, but specific indications are lacking. We sought to identify independent predictors of VTE in critically-ill trauma patients who cannot receive chemical prophylaxis in order to identify a subset of patients who may benefit from aggressive screening and/or prophylactic IVCF placement.
Methods:
All trauma patients in the surgical ICU from 2008 to 2009 were prospectively followed. Patients with an ICU length of stay ≥2 days who had contraindications to prophylactic anticoagulation were included. Screening duplex exams were obtained within 48 h of admission and then weekly. CT-angiography for PE was obtained if clinically indicated. Patients were excluded if they did not receive a duplex or if they had a post-injury VTE prior to ICU admission. Data regarding VTE rates (lower extremity [LE] DVT or PE), demographics, past medical history (PMH), injuries, and surgeries were collected. Univariate and multivariable analyses were performed to identify independent predictors of VTE with a p<0.05.
Results:
411 trauma patients with a mean age of 48 (SD 22) years and 8 (SD 9) ICU days were included. 72% were male and the mean ISS was 22 (SD 13). 30 (7.3%) patients developed VTE: 28 (6.8%) with LEDVT and 2 (0.5%) with PE. Risk factors for VTE with a p<0.2 on univariate analysis included: PMH of DVT, injury severity score (ISS), extremity fractures (Fx), and a pelvis or LE extremity Fx repair. After logistic regression, only PMH of DVT (OR=22.6) and any extremity Fx (OR=2.4) remained as independent predictors.
Conclusion:
VTE occur in 7% of critically injured trauma patients who cannot receive chemical prophylaxis. Aggressive screening and/or prophylactic IVCF placement may be considered in patients with a PMH of DVT or extremity fractures when anticoagulation is prohibited.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies