Related Experiment Video
Updated: May 27, 2026


Electrophysiology on Isolated Brainstem-spinal Cord Preparations from Newborn Rodents Allows Neural Respiratory Network Output Recording
Published on: November 19, 2015
Phasic respiratory modulation of pharyngeal collapsibility via neuromuscular mechanisms in rats
Ying Cao1, Michelle McGuire, Chun Liu
1Division of Sleep Medicine, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts, USA.

Abstract:
Obstructive sleep apnea patients experience recurrent upper airway (UA) collapse due to decreases in the UA dilator muscle activity during sleep. In contrast, activation of UA dilators reduces pharyngeal critical pressure (Pcrit, an index of pharyngeal collapsibility), suggesting an inverse relationship between pharyngeal collapsibility and dilator activity. Since most UA muscles display phasic respiratory activity, we hypothesized that pharyngeal collapsibility is modulated by respiratory drive via neuromuscular mechanisms. Adult male Sprague-Dawley rats were anesthetized, vagotomized, and ventilated (normocapnia). In one group, integrated genioglossal activity, Pcrit, and maximal airflow (V(max)) were measured at three expiration and five inspiration time points within the breathing cycle. Pcrit was closely and inversely related to phasic genioglossal activity, with the value measured at peak inspiration being the lowest. In other groups, the variables were measured during expiration and peak inspiration, before and after each of five manipulations. Pcrit was 26% more negative (-15.0 ± 1.0 cmH(2)O, -18.9 ± 1.2 cmH(2)O; n = 23), V(max) was 7% larger (31.0 ± 1.0 ml/s, 33.2 ± 1.1 ml/s), nasal resistance was 12% bigger [0.49 ± 0.05 cmH(2)O/(ml/s), 0.59 ± 0.05 cmH(2)O/(ml/s)], and latency to induced UA closure was 14% longer (55 ± 4 ms, 63 ± 5 ms) during peak inspiration vs. expiration (all P < 0.005). The expiration-inspiration difference in Pcrit was abolished with neuromuscular blockade, hypocapnic apnea, or death but was not reduced by the superior laryngeal nerve transection or altered by tracheal displacement. Collectively, these results suggest that pharyngeal collapsibility is moment-by-moment modulated by respiratory drive and this phasic modulation requires neuromuscular mechanisms, but not the UA negative pressure reflex or tracheal displacement by phasic lung inflation.

Related Concept Videos
 01:22
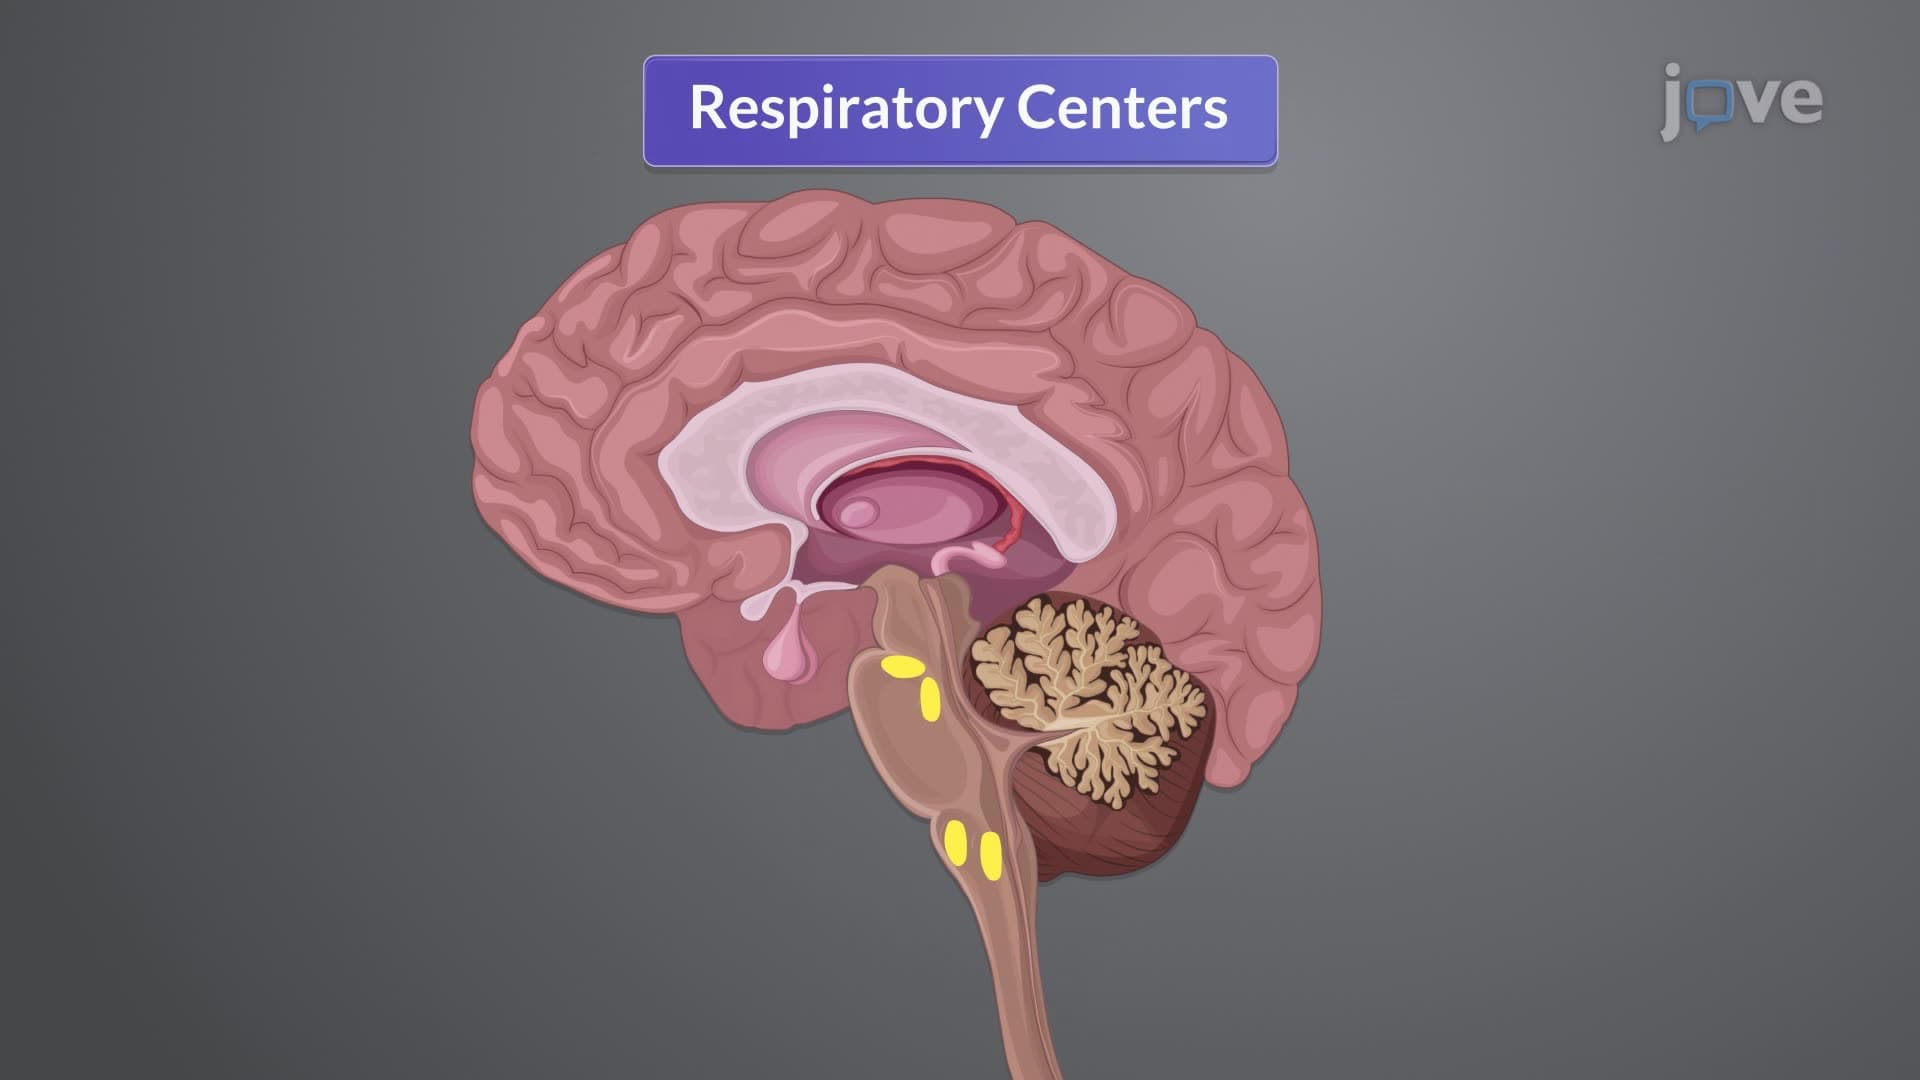
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
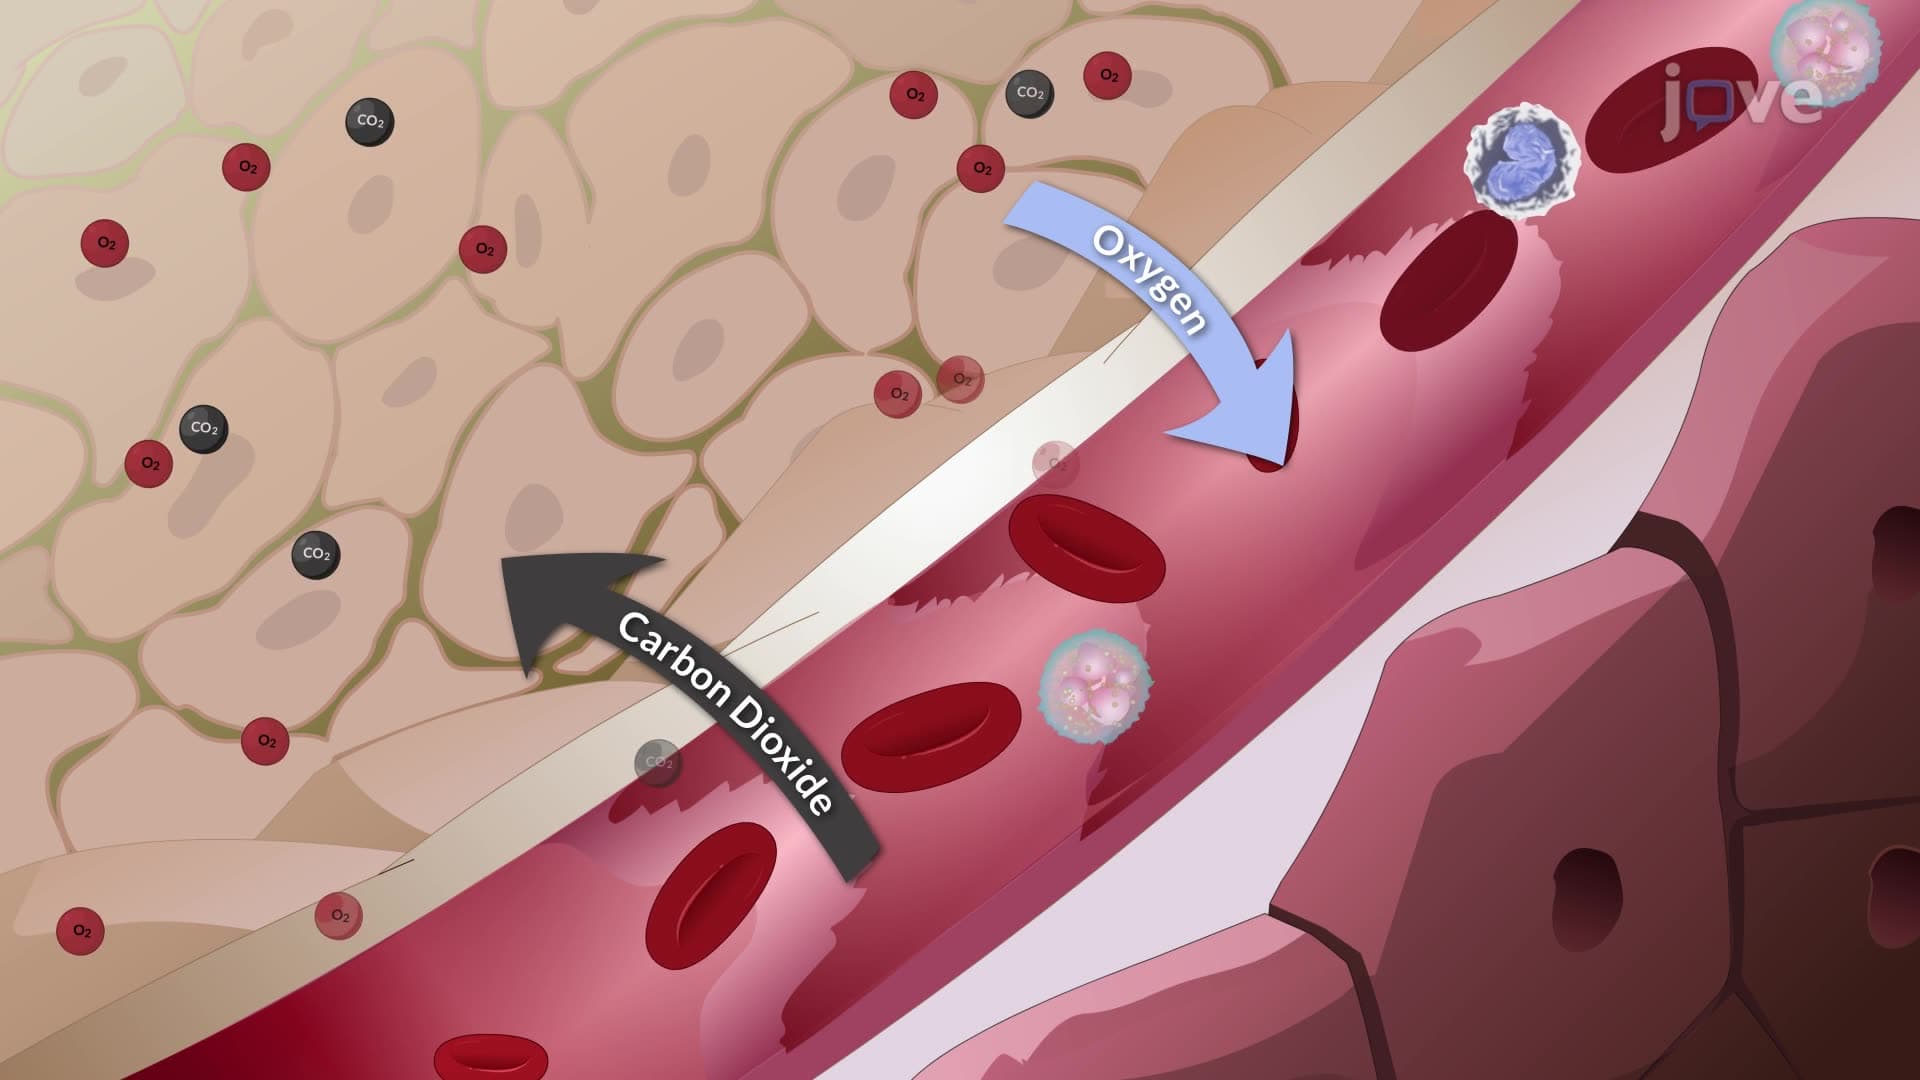
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are produced, leading to a...
 01:30
Acute Respiratory Failure-III
 01:21
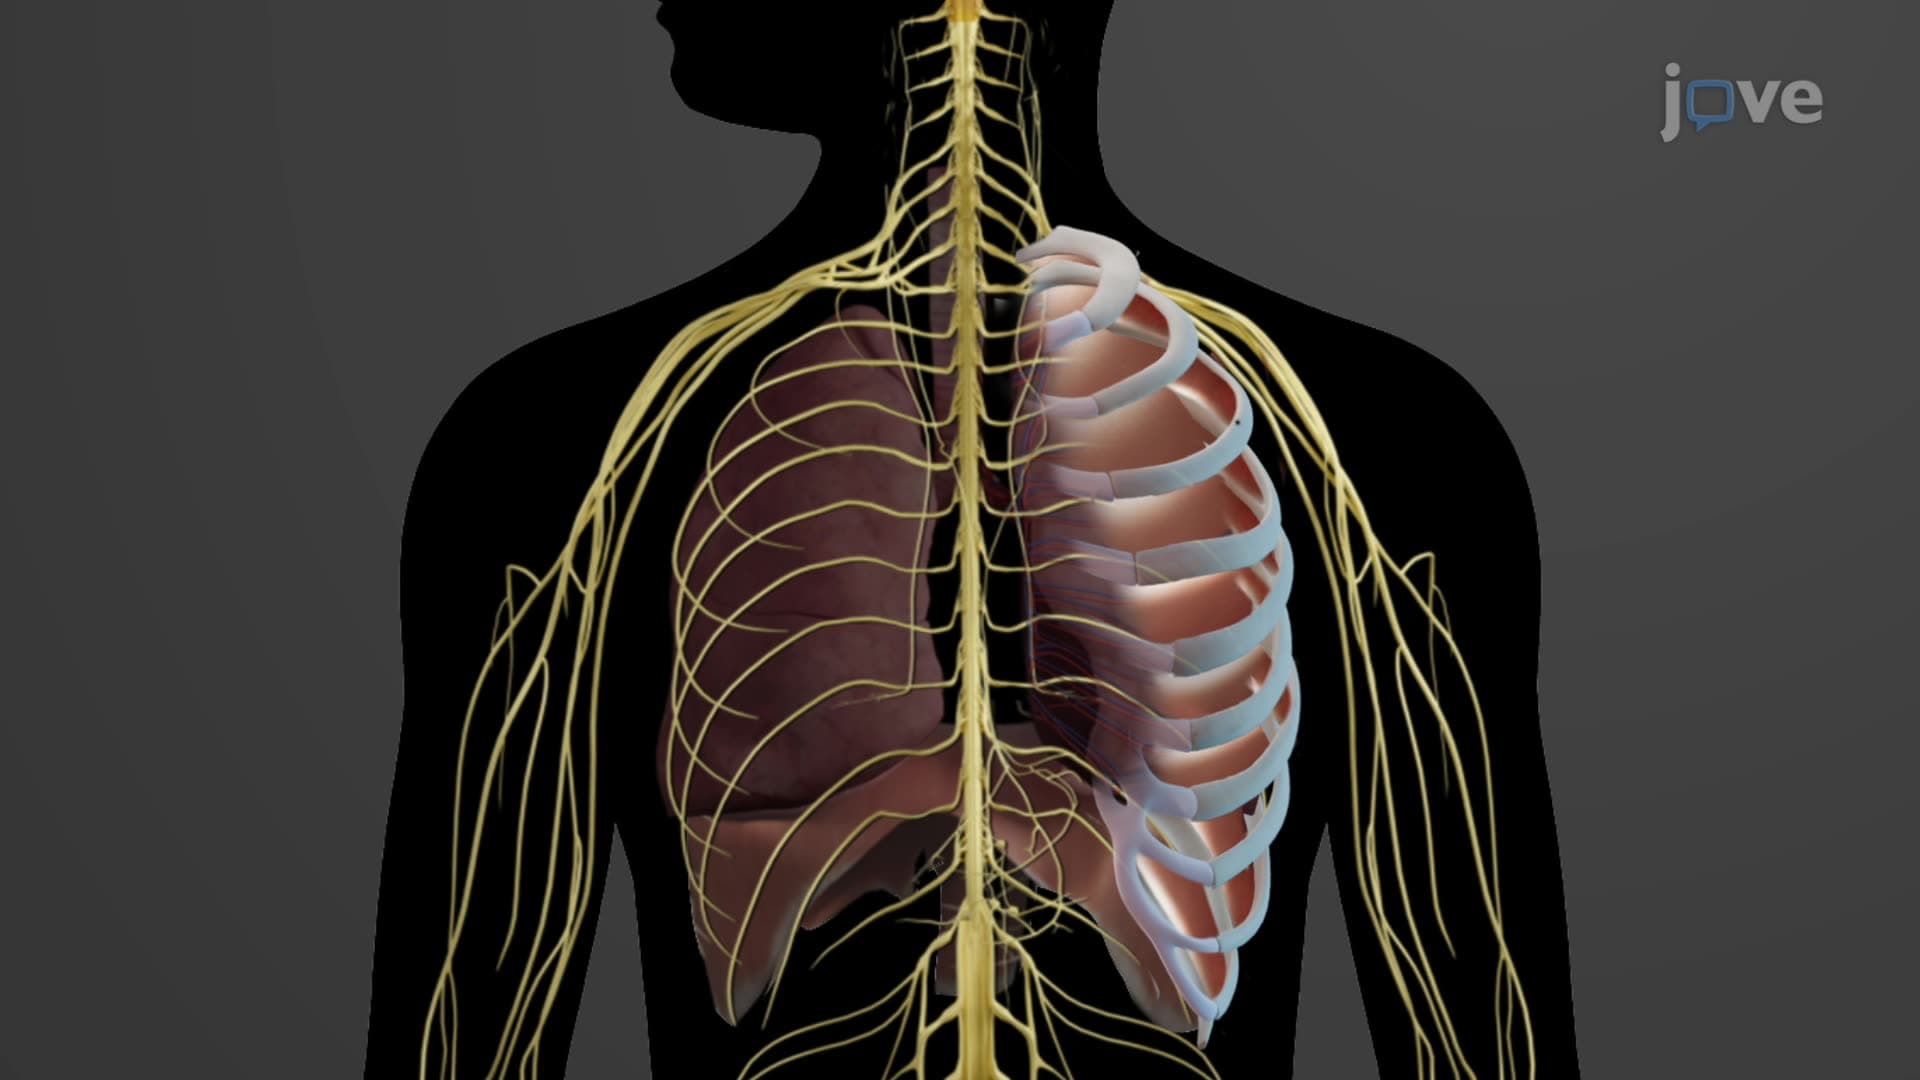
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...