Related Experiment Video
Updated: May 27, 2026
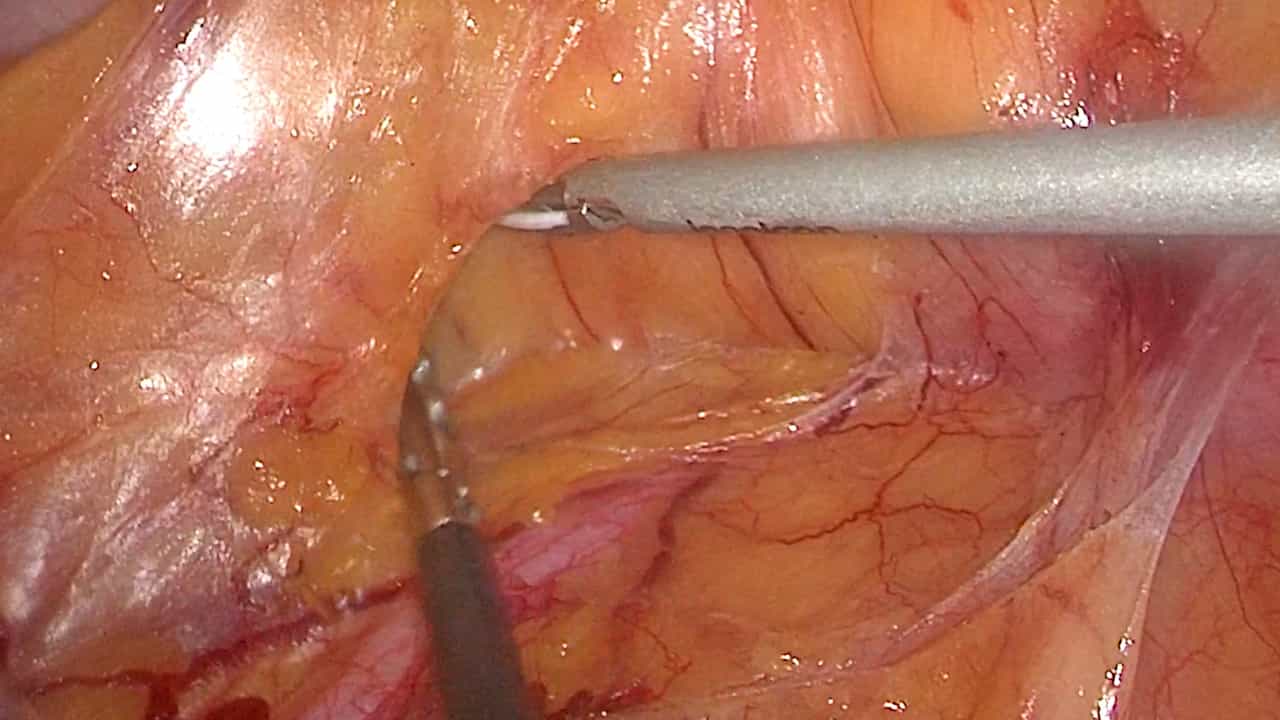

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
The anatomical and surgical consequences of right colectomy for cancer
Milan Spasojevic1, Bojan V Stimec, Lars Bergene Gronvold
1Department of Gastrointestinal Surgery, Vestfold Hospital, Tonsberg, Norway.

Background:
Current practice when performing right colectomy for cancer is to divide the feeding vessels for the right colon on the right side of the superior mesenteric vein.
Objective:
This study aims to show that arterial stumps can be visualized through an early postoperative CT and analyze their anatomical and surgical characteristics.
Design:
This study presents a retrospective review of prospective data.
Settings:
:The study was conducted at the Department of Surgery, Vestfold Hospital, Tonsberg, Norway.
Patients:
Patients with leakage after a right colectomy for cancer (2003-2011) were identified through a local prospective complication registry (FileMaker Pro 9.0v3 software).
Interventions:
Both preoperative and postoperative CTs were retrieved, reanalyzed, and 3-dimensionally reconstructed (Osirix v.3.0.2./Mimics v.13.1.). Patients without postoperative CTs were excluded.
Main Outcome Measures:
The main outcomes measured were length, caliber of presumed and actual arterial stumps, and their position relative to the superior mesenteric vein.
Results:
Eighteen patients, median age 69 (10 men) were included. All patients had postoperative CTs, and 15 patients had preoperative CTs. Median time from operation to postoperative CT was 5 days. The ileocolic artery was found in 14 (11 CT pairs) patients, and the right colic artery was found in 5 (4 pairs) patients. Actual stump lengths were 28.0 mm (SD 9.3) and 37.3 mm (SD 14.9). A significant statistical difference between presumed and actual ileocolic artery stump lengths was found (P = .002). Posterior crossing to the superior mesenteric vein was noticed in 8 of 14 ileocolic arteries and in 3 of 5 right colic arteries. There was no statistical difference in mean caliber for the preoperative and postoperative right colic artery (P = .505) and ileocolic artery (P = .474).
Limitations:
Difficulties when interpreting the postoperative images, due to intra-abdominal effusion, staples, edema, and altered syntopy of blood vessels, were overcome through comparison with preoperative CTs.
Conclusion:
An early postoperative CT can show arterial stumps after right colectomy for cancer. These stumps appear to be significantly longer than presumed; implying a significant improvement potential when specimen size is concerned.
More Related Videos

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...