Related Experiment Video
Updated: May 27, 2026

Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Muscle strength and soccer practice as major determinants of bone mineral density in adolescents
André Seabra1, Elisa Marques, João Brito
1Faculty of Sport, University of Porto, Centre of Research, Education, Innovation and Intervention in Sport, Porto, Portugal. aseabra@fade.up.pt

Objectives:
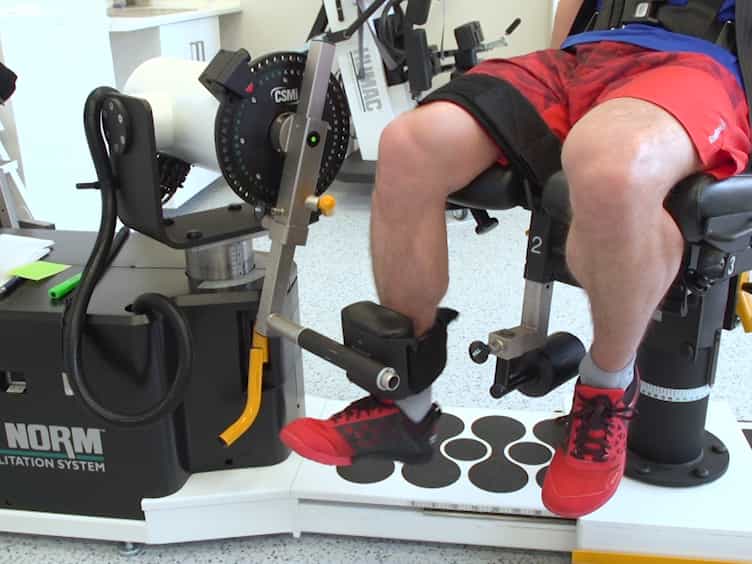
To analyse the relationship between isokinetic strength of the lower limb muscles and bone mineral density and content (BMD, BMC) of adolescent male soccer players and age-matched controls not involved in sport (12-15 years).
Methods:
A random sample of 151 young males was divided into soccer players (SG; n=117) and control subjects (CG; n=34). Peak torque of knee extensors (PTE) and flexors (PTF) was measured during isokinetic knee joint movement (90°/s) of the dominant and non-dominant lower limbs. BMD and BMC of the whole-body, lumbar spine, dominant/non-dominant lower limb were determined by dual-energy X-ray absorptiometry. Physical activity was monitored with accelerometers during 5 days. Estimated maturity offset was used as an indicator of biological maturity status.
Results:
Whole-body BMD (1.03±0.01 vs. 0.98±0.01 g/cm2, P=0.003) and dominant (1.09±0.01 vs. 1.02±0.01 g/cm2, P<0.001) and non-dominant (1.09±0.01 vs. 1.01±0.01 g/cm2, P<0.001) lower limb BMD was greater in SG compared to CG. No significant differences were found for BMC. Compared to CG, SG performed better in the YY-IE2 test (780±40 vs. 625±31 m), exhibited higher PTE (dominant limb: 155.2±30.3 vs. 123.4±37.0N m; non-dominant limb: 156.2±36.1 vs. 120.4±41.1 N m) and PTF muscles (dominant limb: 79.0±25.3 vs. 57.1±25.3 Nm; non-dominant limb: 73.3±20.7 vs. 57.0±24.2N m). Moreover, the PTE, soccer participation and maturity status were positively associated with the BMD at all body sites (r2=0.57-0.73, P<0.05).
Conclusions:
Muscle strength of knee extensors is associated with BMD and BMC at all body sites. Muscle-skeletal structures respond positively to the weight-bearing and impact-loading imposed by soccer practice. Soccer seemed to be a multilateral balanced sport activity.
More Related Videos

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:22
The Functions of the Skeletal System