Related Experiment Video
Updated: May 27, 2026
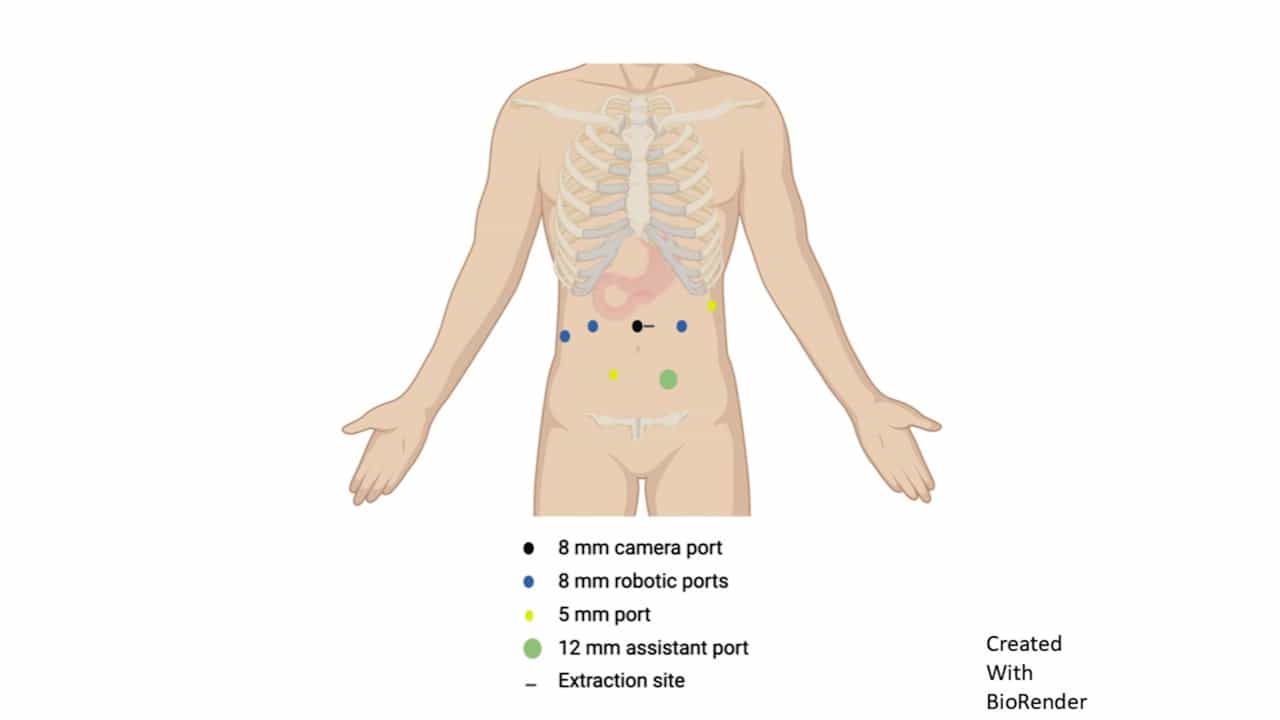

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Recurrence after complete resection and selective use of adjuvant therapy for stage I through III Merkel cell
Ryan C Fields1, Klaus J Busam, Joanne F Chou
1Department of Surgery, Memorial Sloan-Kettering Cancer Center, New York, New York 10065, USA.

Background:
Merkel cell carcinoma (MCC) is a rare cutaneous neuroendocrine neoplasm whose natural history is poorly understood. Here, the authors describe their experience with a large cohort of patients who were treated at a single institution to describe patterns of recurrence after curative therapy.
Methods:
Review of a prospective database was performed. Patient-related, tumor-related, and treatment-related variables were recorded, and the site and timing of initial recurrence were recorded. Factors associated with receipt of adjuvant therapy and recurrence were determined.
Results:
In total, 364 patients with stage I through III MCC who underwent complete resection were identified. Adjuvant local radiation therapy (RT), lymph node RT, and chemotherapy were received selectively by 23%, 23%, and 15% of patients, respectively. Factors associated with the receipt of adjuvant therapy included younger age, primary tumor features (larger size, lymphovascular invasion [LVI], positive margin excision), and increasing pathologic stage. With median follow-up of 3.6 years, 108 patients (30%) developed a recurrence, including 11 local recurrences (3%), 12 in-transit recurrences (3%), 43 lymph node recurrences (12%), and 42 distant recurrences (12%). Clinically involved lymph nodes, primary tumor LVI, and a history of leukemia/lymphoma were predictive of recurrence. The majority of recurrences (80%) occurred in patients who had clinically involved lymph nodes or patients who did not undergo pathologic lymph node evaluation.
Conclusions:
A low recurrence rate in patients with clinically lymph node-negative MCC was achieved with adequate surgery (including sentinel lymph node biopsy) and the selective use of adjuvant RT for high-risk tumors. In contrast, patients with clinically lymph node-positive MCC had significantly higher rates of recurrence, especially distant recurrence. The authors concluded that contemporary natural history studies are critical in designing treatment pathways and clinical trials for MCC.

