Related Experiment Video
Updated: May 27, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
The diagnosis and management of pleural effusions in the ICU
David M Maslove1, Benson Tze-Ming Chen, Helena Wang
1Division of Pulmonary and Critical Care Medicine, Stanford University School of Medicine, Stanford, CA, USA.

Pleural effusions are common in critically ill patients. Most effusions in intensive care unit (ICU) patients are of limited clinical significance; however, some are important and require aggressive management. Transudative effusions in the ICU are commonly caused by volume overload, decreased plasma oncotic pressure, and regions of altered pleural pressure attributable to atelectasis and mechanical ventilation. Exudates are sequelae of pulmonary or pleural infection, pulmonary embolism, postsurgical complications, and malignancy. Increases in pleural fluid volume are accommodated principally by chest wall expansion and, to a lesser degree, by lung collapse. Studies in mechanically ventilated patients suggest that pleural fluid drainage can result in improved oxygenation for up to 48 hours, but data on clinical outcomes are limited. Mechanically ventilated patients with pleural effusions should be semirecumbant and treated with higher levels of positive-end expiratory pressure. Rarely, large effusions can cause cardiac tamponade or tension physiology, requiring urgent drainage. Bedside ultrasound is both sensitive and specific for diagnosing pleural effusions in mechanically ventilated patients. Sonographic findings of septation and homogenous echogenicity may suggest an exudative effusion, but definitive diagnosis requires pleural fluid sampling. Thoracentesis should be carried out under ultrasound guidance. Antibiotic regimens for parapneumonic effusions should be based on current pneumonia guidelines, and anaerobic coverage should be included in the case of empyema. Decompression of the pleural space may be necessary to improve respiratory mechanics, as well as to treat complicated effusions. While small-bore catheters inserted under ultrasound guidance may be used for nonseptated effusions, surgical consultation should be sought in cases where this approach fails, or where the effusion appears complex and septated at the outset. Further research is needed to determine the effects of pleural fluid drainage on clinical outcomes in mechanically ventilated patients, to evaluate weaning strategies that include pleural fluid drainage, and to better identify patients in whom pleural effusions are more likely to be infected.
Pleural effusions are common in critically ill patients. Most effusions in intensive care unit (ICU) patients are of limited clinical significance; however, some are important and require aggressive management. Transudative effusions in the ICU are commonly caused by volume overload, decreased plasma oncotic pressure, and regions of altered pleural pressure attributable to atelectasis and mechanical ventilation. Exudates are sequelae of pulmonary or pleural infection, pulmonary embolism, postsurgical complications, and malignancy. Increases in pleural fluid volume are accommodated principally by chest wall expansion and, to a lesser degree, by lung collapse. Studies in mechanically ventilated patients suggest that pleural fluid drainage can result in improved oxygenation for up to 48 hours, but data on clinical outcomes are limited. Mechanically ventilated patients with pleural effusions should be semirecumbant and treated with higher levels of positive-end expiratory pressure. Rarely, large effusions can cause cardiac tamponade or tension physiology, requiring urgent drainage. Bedside ultrasound is both sensitive and specific for diagnosing pleural effusions in mechanically ventilated patients. Sonographic findings of septation and homogenous echogenicity may suggest an exudative effusion, but definitive diagnosis requires pleural fluid sampling. Thoracentesis should be carried out under ultrasound guidance. Antibiotic regimens for parapneumonic effusions should be based on current pneumonia guidelines, and anaerobic coverage should be included in the case of empyema. Decompression of the pleural space may be necessary to improve respiratory mechanics, as well as to treat complicated effusions. While small-bore catheters inserted under ultrasound guidance may be used for nonseptated effusions, surgical consultation should be sought in cases where this approach fails, or where the effusion appears complex and septated at the outset. Further research is needed to determine the effects of pleural fluid drainage on clinical outcomes in mechanically ventilated patients, to evaluate weaning strategies that include pleural fluid drainage, and to better identify patients in whom pleural effusions are more likely to be infected.
More Related Videos
 03:32
A Pleural Effusion Model in Rats by Intratracheal Instillation of Polyacrylate/Nanosilica
Published on: April 12, 2019
 08:22
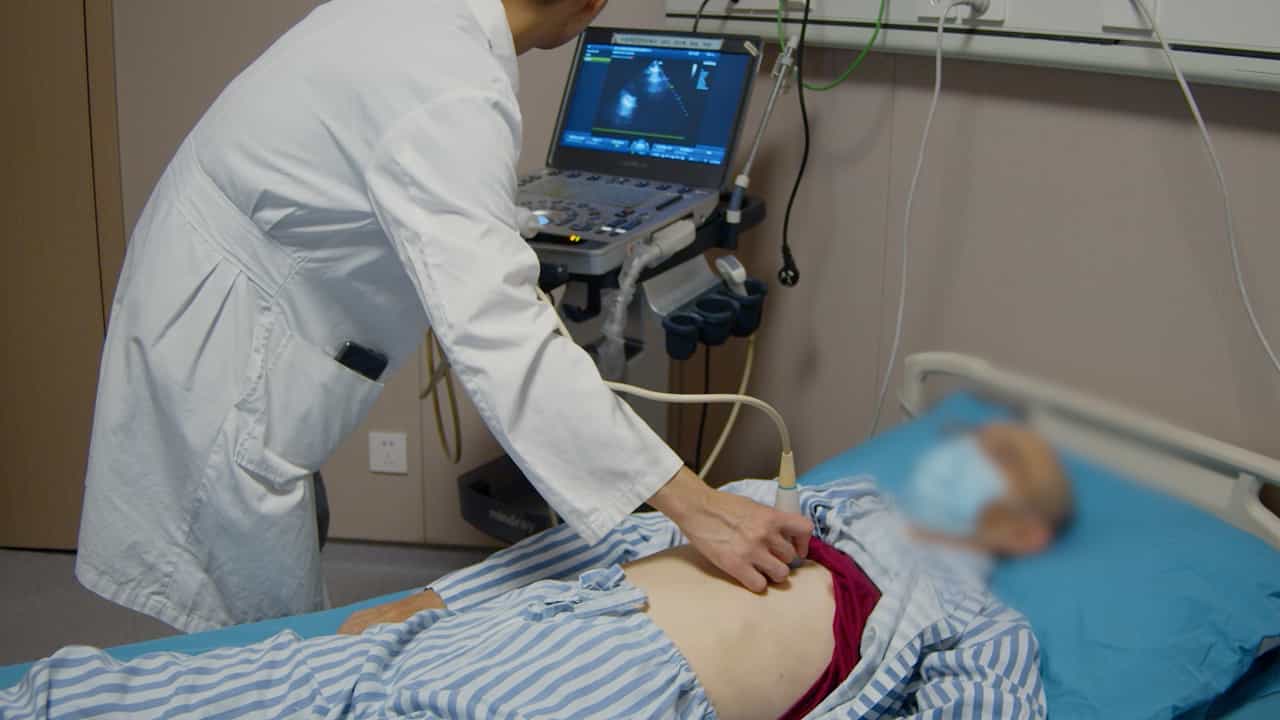
The Application of Point-of-Care Ultrasonography (POCUS) in the Management of Acute Respiratory Distress Syndrome (ARDS) in the Intensive Care Unit
Published on: December 12, 2025
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:30
Pneumonia III: Complications and Assessment