Partial adenosine A1 receptor agonists for cardiovascular therapies
Related Experiment Video
Updated: May 27, 2026
Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Barbara E Albrecht-Küpper1, Kirsten Leineweber, Peter G Nell
1Research Center Wuppertal, Department of Heart Diseases, Institute of Cardiology, Bayer Pharma AG, Aprather Weg 18a, 42096, Wuppertal, Germany, barbara.albrecht@bayer.com.

Abstract:
Adenosine, a purine nucleoside, is present in all cells in tightly regulated concentrations. It has many different physiological effects in the whole body and in the heart. Adenosine activates four G protein-coupled receptors A1, A2a, A2b, and A3. Activation of myocardial A1 receptors has been shown to inhibit a variety of myocardial pathologies associated with ischemia and reperfusion injury, including stunning, arrhythmogenesis, coronary and ventricular dysfunction, acute myocardial infarction, apoptosis, and chronic heart failure, implying several options for new cardiovascular therapies for diseases, like angina pectoris, control of cardiac rhythm, ischemic injury during an acute coronary syndrome, or heart failure. However, the main issue of using full A1 receptor agonists in such indications is the broad physiologic spectrum of cardiac and extracardiac effects. Desired A1 receptor-mediated protective and regenerative cardiovascular effects might be counter-regulated by unintended side effects when considering full A1 receptor agonists. These effects can be overcome by partial A1 agonists. Partial A1 agonists can be used to trigger only some of the physiological responses of receptor activation depending on endogenous adenosine levels and on receptor reserve in different tissues. CV-Therapeutics reported the identification of a partial A1 receptor agonist CVT-3619, and recently, another partial A1 receptor agonist VCP28 was published. Both compounds are adenosine derivatives. Adenosine-like A1 receptor agonists often have the drawback of a short half-life and low bioavailability, making them not suitable for chronic oral therapy. We identified the first non-adenosine-like partial A1 receptor agonist(s) with pharmacokinetics optimal for oral once daily treatment and characterized the qualities of the partial character of the A1 receptor agonist(s) in preclinical and clinical studies.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:17
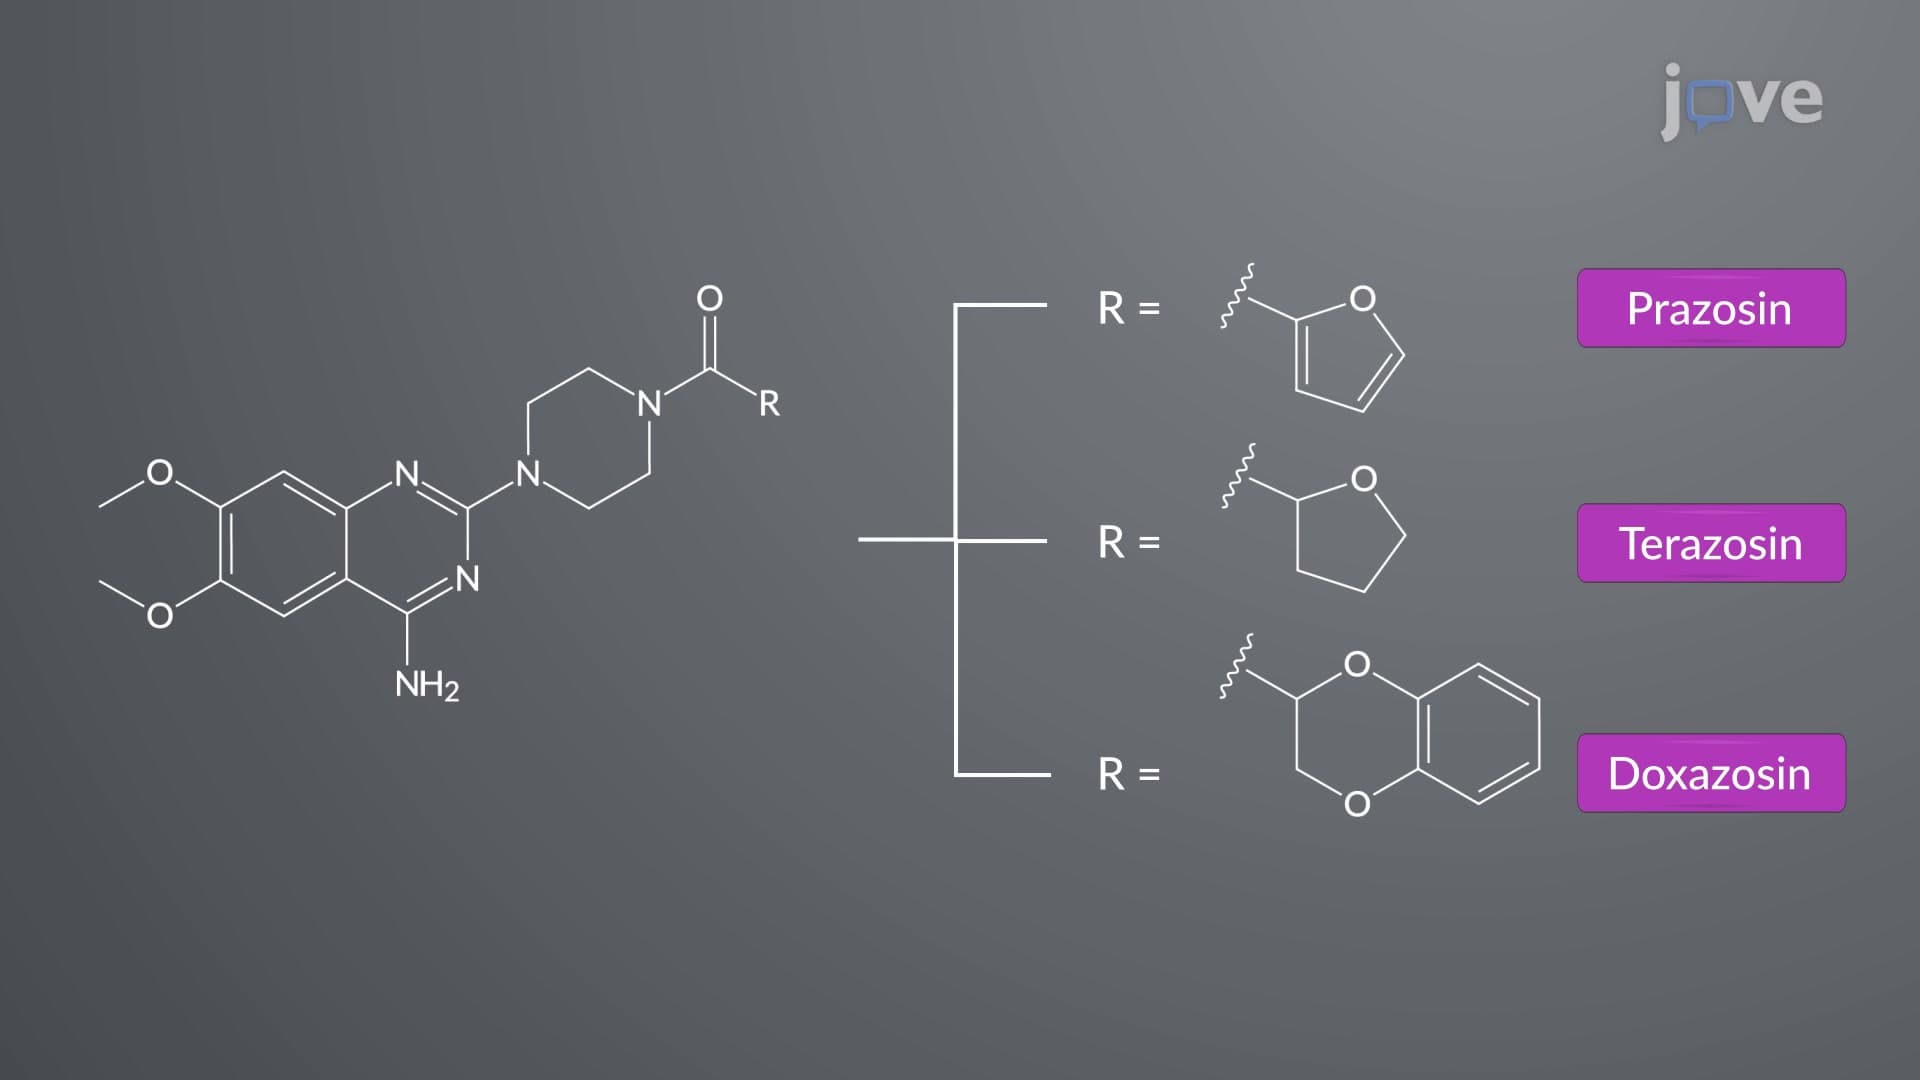
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
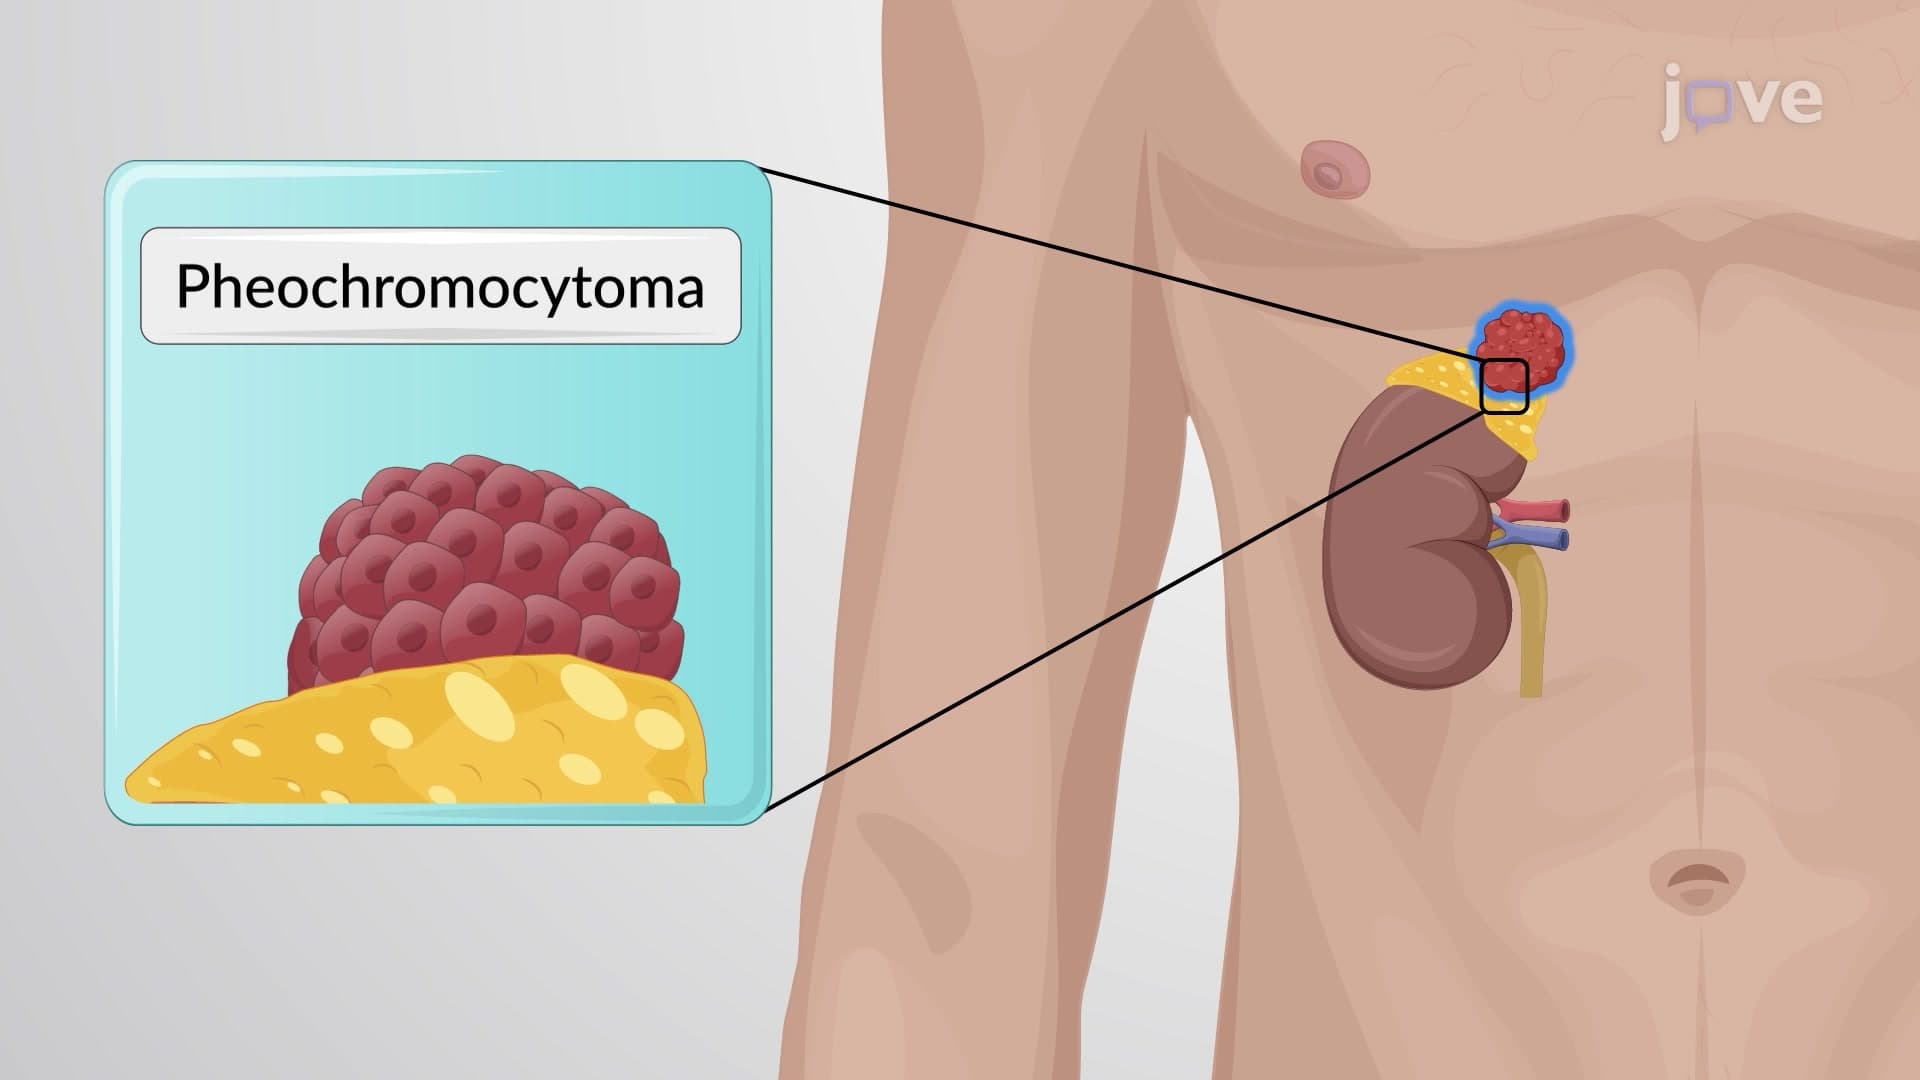
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...