Related Experiment Video
Updated: May 27, 2026
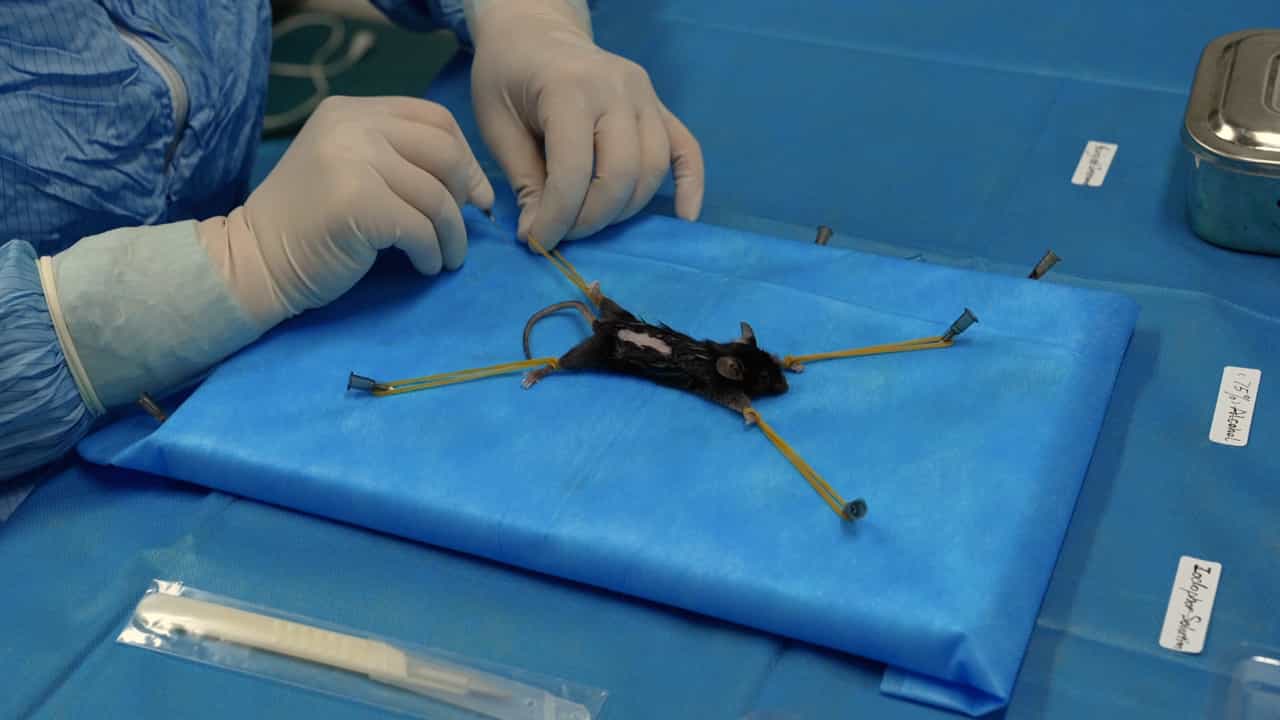

Exploring Independent Effects of Follicle-Stimulating Hormone In Vivo in a Mouse Model
Published on: August 11, 2023
Follicle-stimulating hormone is independently associated with lean mass but not BMD in younger postmenopausal women
Margaret L Gourlay1, Bonny L Specker, Chenxi Li
1Department of Family Medicine, University of North Carolina, Chapel Hill, NC 27599-7595, USA. margaret_gourlay@med.unc.edu

Purpose:
Increased follicle-stimulating hormone (FSH) has been associated with lower bone mineral density (BMD) in animal models and longitudinal studies of women, but a direct effect has not been demonstrated.
Methods:
We tested associations between FSH, non-bone body composition measures and BMD in 94 younger (aged 50 to 64 years) postmenopausal women without current use of hormone therapy, adjusting for sex hormone concentrations and clinical risk factors for osteoporosis. Lean mass, fat mass and areal BMD (aBMD) at the spine, femoral neck and total hip were measured using dual energy X-ray absorptiometry (DXA). Volumetric BMD (vBMD) was measured at the distal radius using peripheral quantitative computed tomography (pQCT).
Results:
FSH was inversely correlated with lean and fat mass, bioavailable estradiol, spine and hip aBMD, and vBMD at the ultradistal radius. In the multivariable analysis, FSH was independently associated with lean mass (β=-0.099, p=0.005) after adjustment for age, race, years since menopause, bioavailable estradiol, bioavailable testosterone, LH, PTH, SHBG and urine N-telopeptide. FSH showed no statistically significant association with aBMD at any site or pQCT measures at the distal radius in adjusted models. Race was independently associated with aBMD, and race and urine N-telopeptide were independently associated with bone area and vBMD.
Conclusions:
After adjustment for hormonal measures and osteoporosis risk factors, higher concentrations of FSH were independently associated with lower lean mass, but not with BMD. Previously reported correlations between FSH and BMD might have been due to indirect associations via lean mass or weight.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:28
Menopause
 01:06
Multipotency and Niche of Bulge Stem Cell
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...