Related Experiment Video
Updated: May 27, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Voiding dysfunction after total mesorectal excision in rectal cancer
Jae Heon Kim1, Tae Il Noh, Mi Mi Oh
1Department of Urology, Korea University Ansan Hospital, Korea University College of Medicine, Ansan, Korea.

Purpose:
The aim of this study was to assess the voiding dysfunction after rectal cancer surgery with total mesorectal excision (TME).
Methods:
This was part of a prospective study done in the rectal cancer patients who underwent surgery with TME between November 2006 and June 2008. Consecutive uroflowmetry, post-voided residual volume, and a voiding questionnaire were performed at preoperatively and postoperatively.
Results:
A total of 50 patients were recruited in this study, including 28 male and 22 female. In the comparison of the preoperative data with the postoperative 3-month data, a significant decrease in mean maximal flow rate, voided volume, and post-voided residual volume were found. In the comparison with the postoperative 6-month data, however only the maximal flow rate was decreased with statistical significance (P=0.02). In the comparison between surgical methods, abdominoperineal resection patients showed delayed recovery of maximal flow rate, voided volume, and post-voided residual volume. There was no significant difference in uroflowmetry parameters with advances in rectal cancer stage.
Conclusions:
Voiding dysfunction is common after rectal cancer surgery but can be recovered in 6 months after surgery or earlier. Abdominoperineal resection was shown to be an unfavorable factor for postoperative voiding. Larger prospective study is needed to determine the long-term effect of rectal cancer surgery in relation to male and female baseline voiding condition.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:19
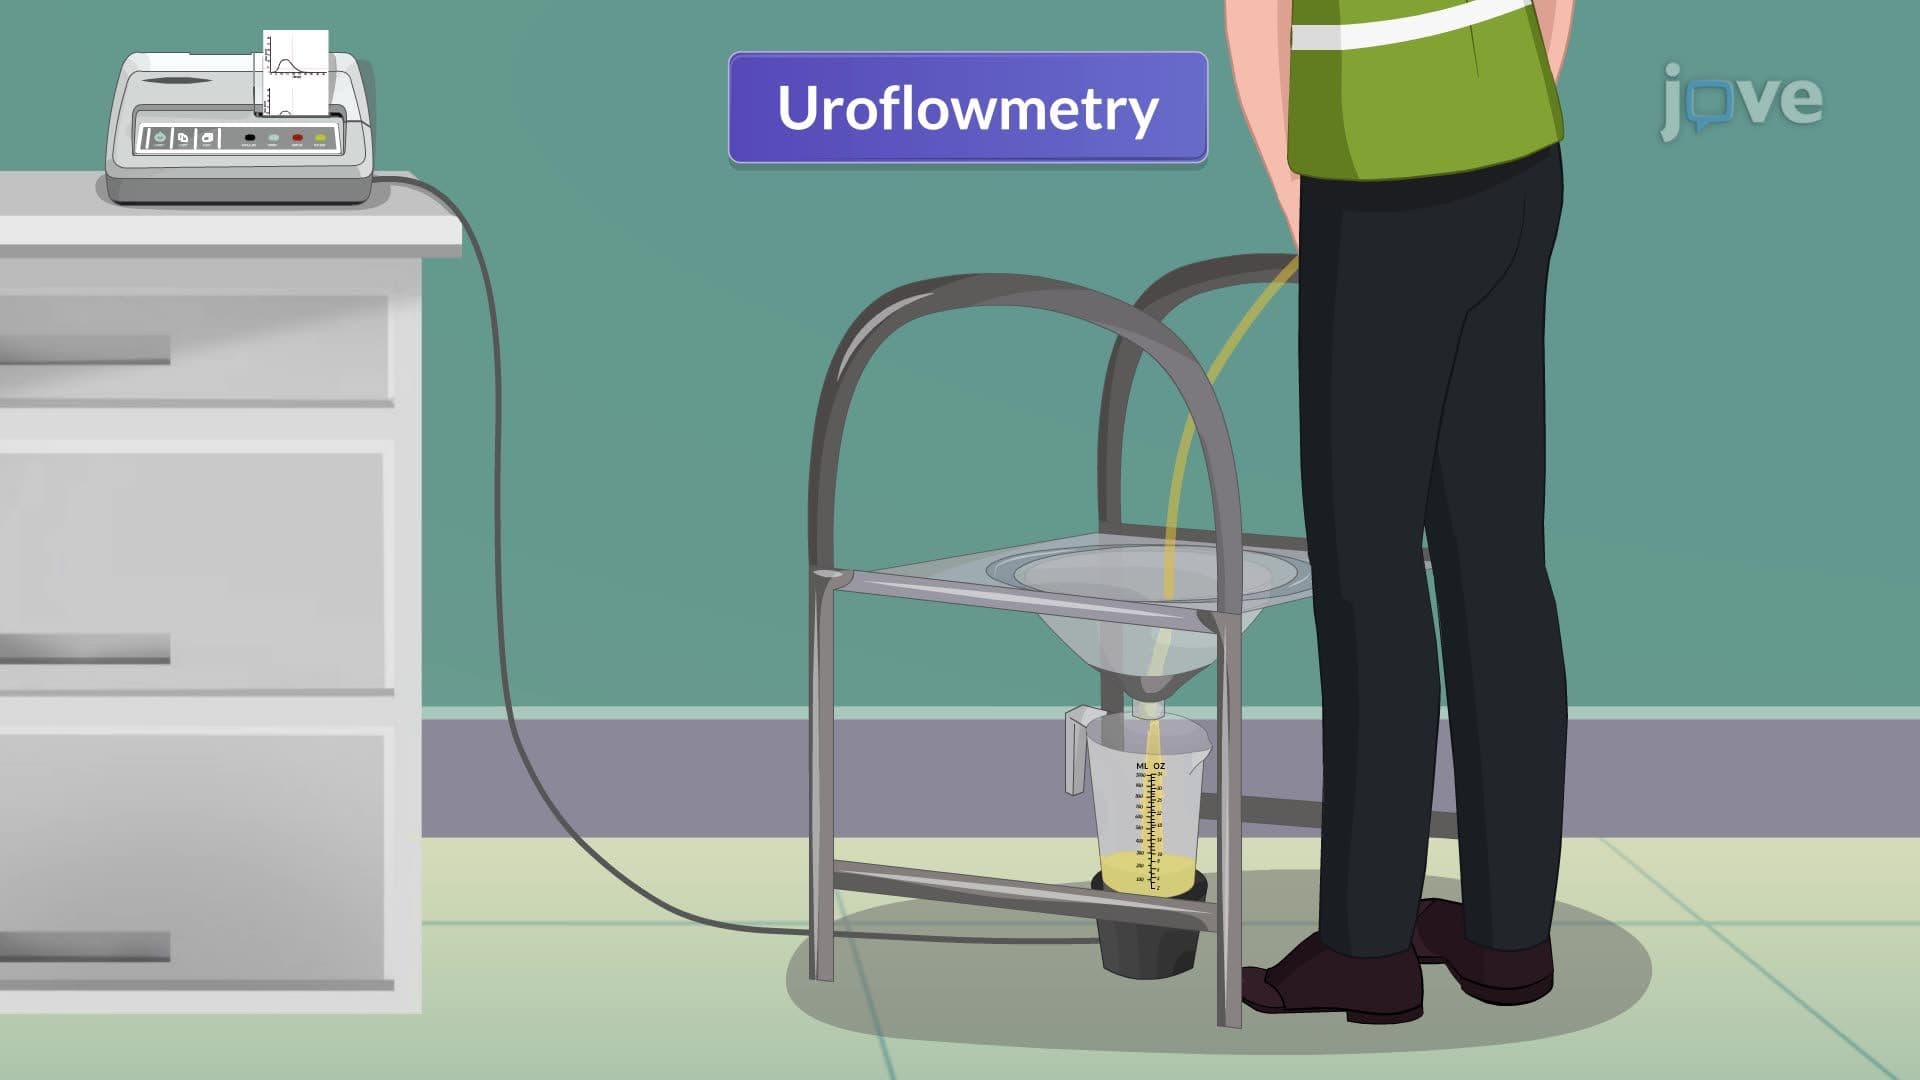
Urodynamic Studies: Uroflowmetry
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...