Effect of simvastatin on the pharmacokinetics of anastrozole

Ting Bao1, Amanda L Blackford, Vered Stearns

  • 1Sidney Kimmel Comprehensive Cancer Center, Johns Hopkins School of Medicine, 1650 Orleans Street, Room 144, Baltimore, MD 21231-1000, USA.

Related Concept Videos

Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism01:18

Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism

Geriatric patients show significant variation in how their bodies process medications, which can change how effective and safe treatments are. The liver is the primary organ where drug metabolism occurs, involving two main types of chemical reactions: phase I and II. Phase I metabolism is driven by the cytochrome P450 enzyme system, which includes key types such as CYP3A, CYP2D6, and CYP2C9. Research indicates that while aging doesn't notably alter the levels or activity of these enzymes, it...
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment01:08

Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
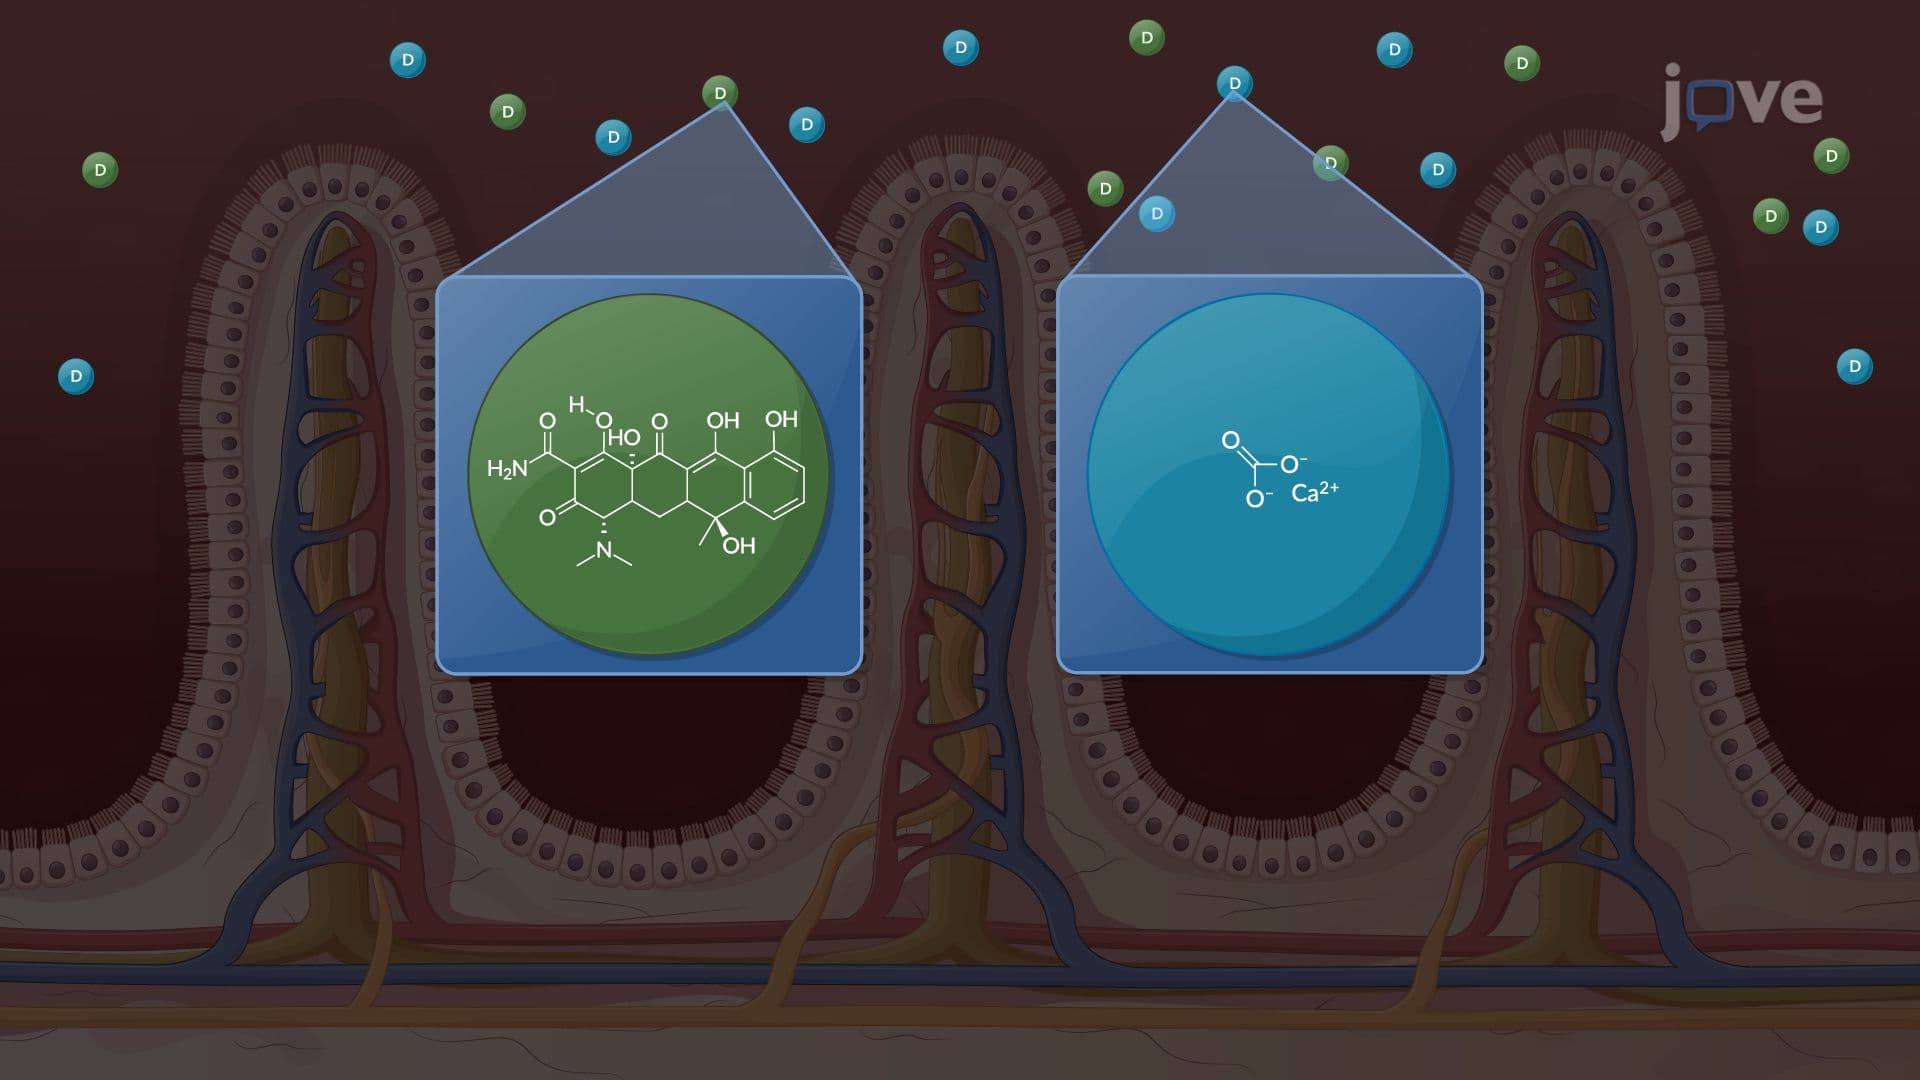
Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...
Pharmacokinetics: Drug–Drug Interactions01:25

Pharmacokinetics: Drug–Drug Interactions

Drug interactions occur when the pharmacological effect of one drug is altered by another substance, either enhancing or diminishing its activity. The drug whose activity is altered is known as the object drug, and the substance causing the alteration is called the agent drug or the precipitant. The net effects of these interactions are mostly undesirable, leading to decreased effectiveness or increased adverse effects. In rare cases, interactions can be beneficial, such as the enhanced...
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug01:14

Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
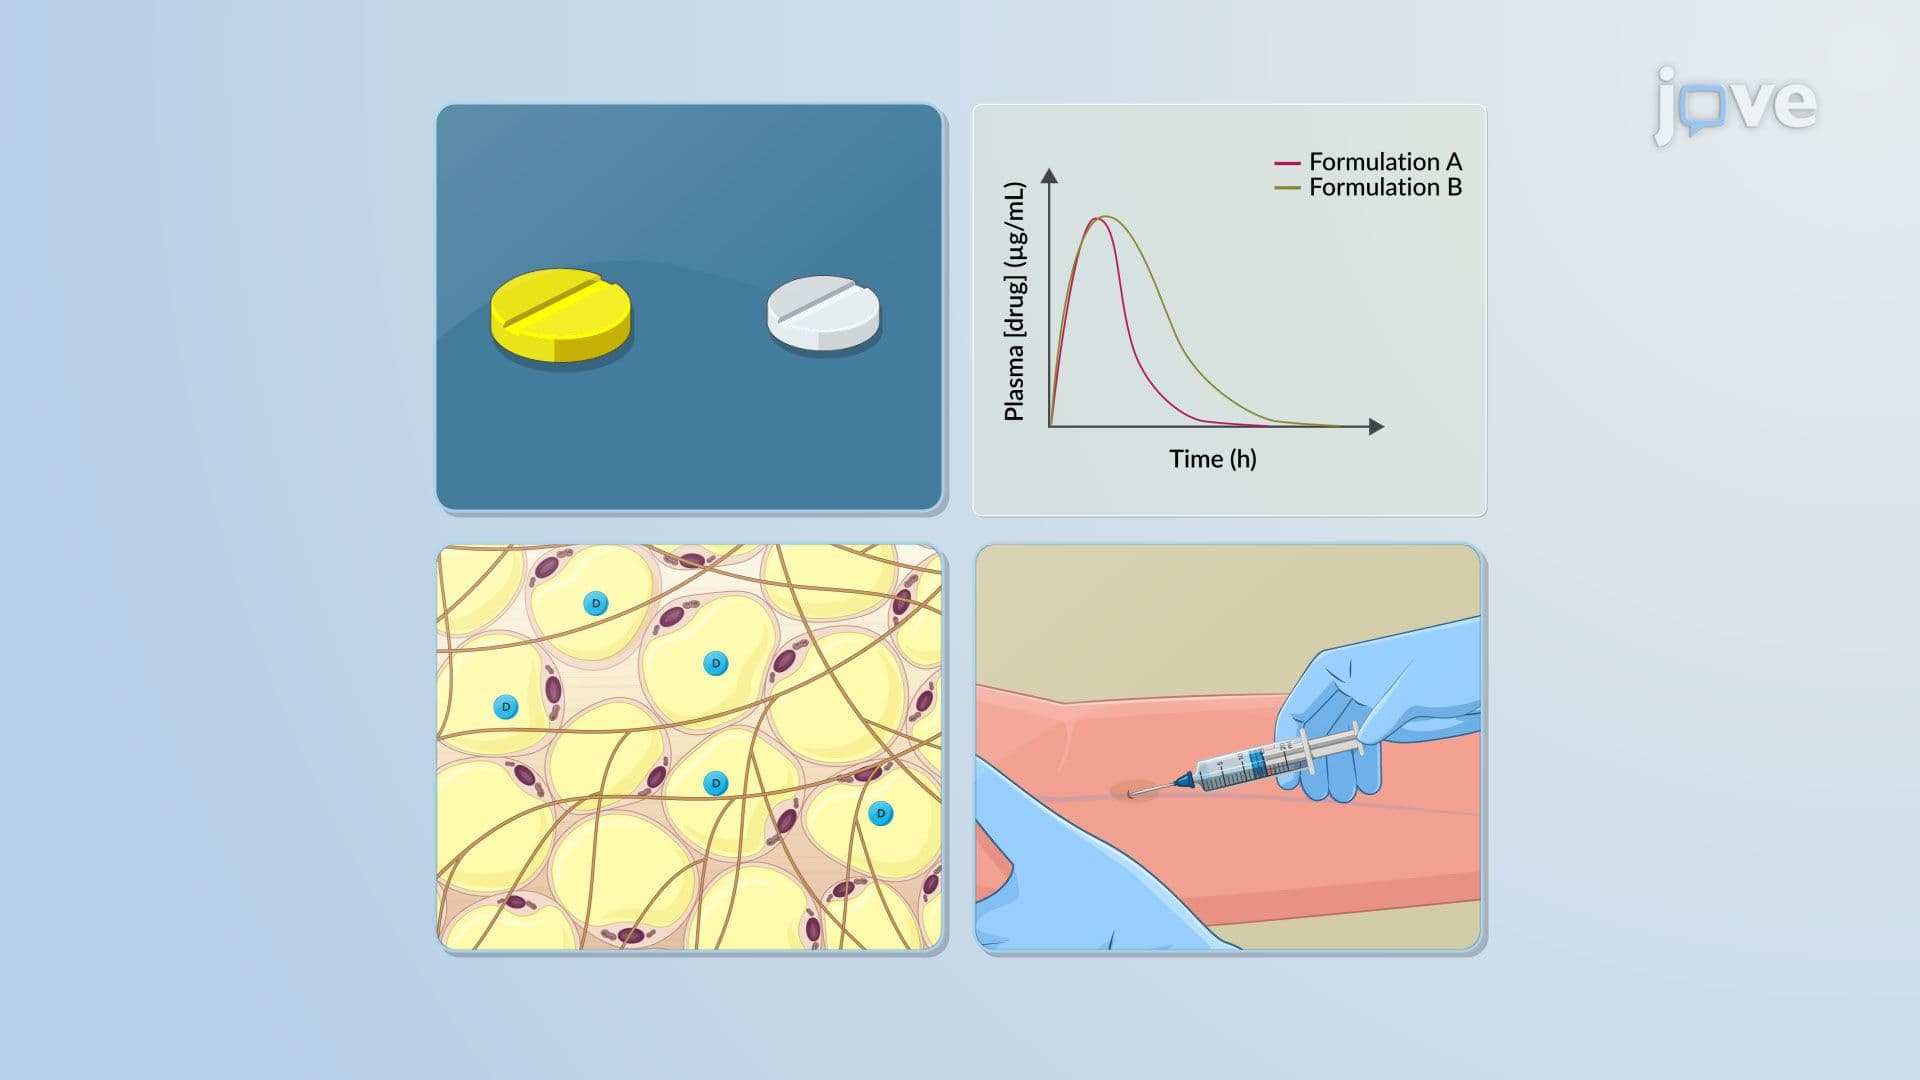
In pharmacotherapy, monitoring drug concentrations is paramount, especially for drugs whose therapeutic effects hinge on both the active compound and its metabolite. Hepatic impairment profoundly influences drug potency by altering liver function. If the drug is more potent than its metabolite, impaired liver function amplifies drug activity due to elevated drug concentration levels. Conversely, if the metabolite holds greater potency, diminished liver function diminishes drug activity by...
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship01:14

Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
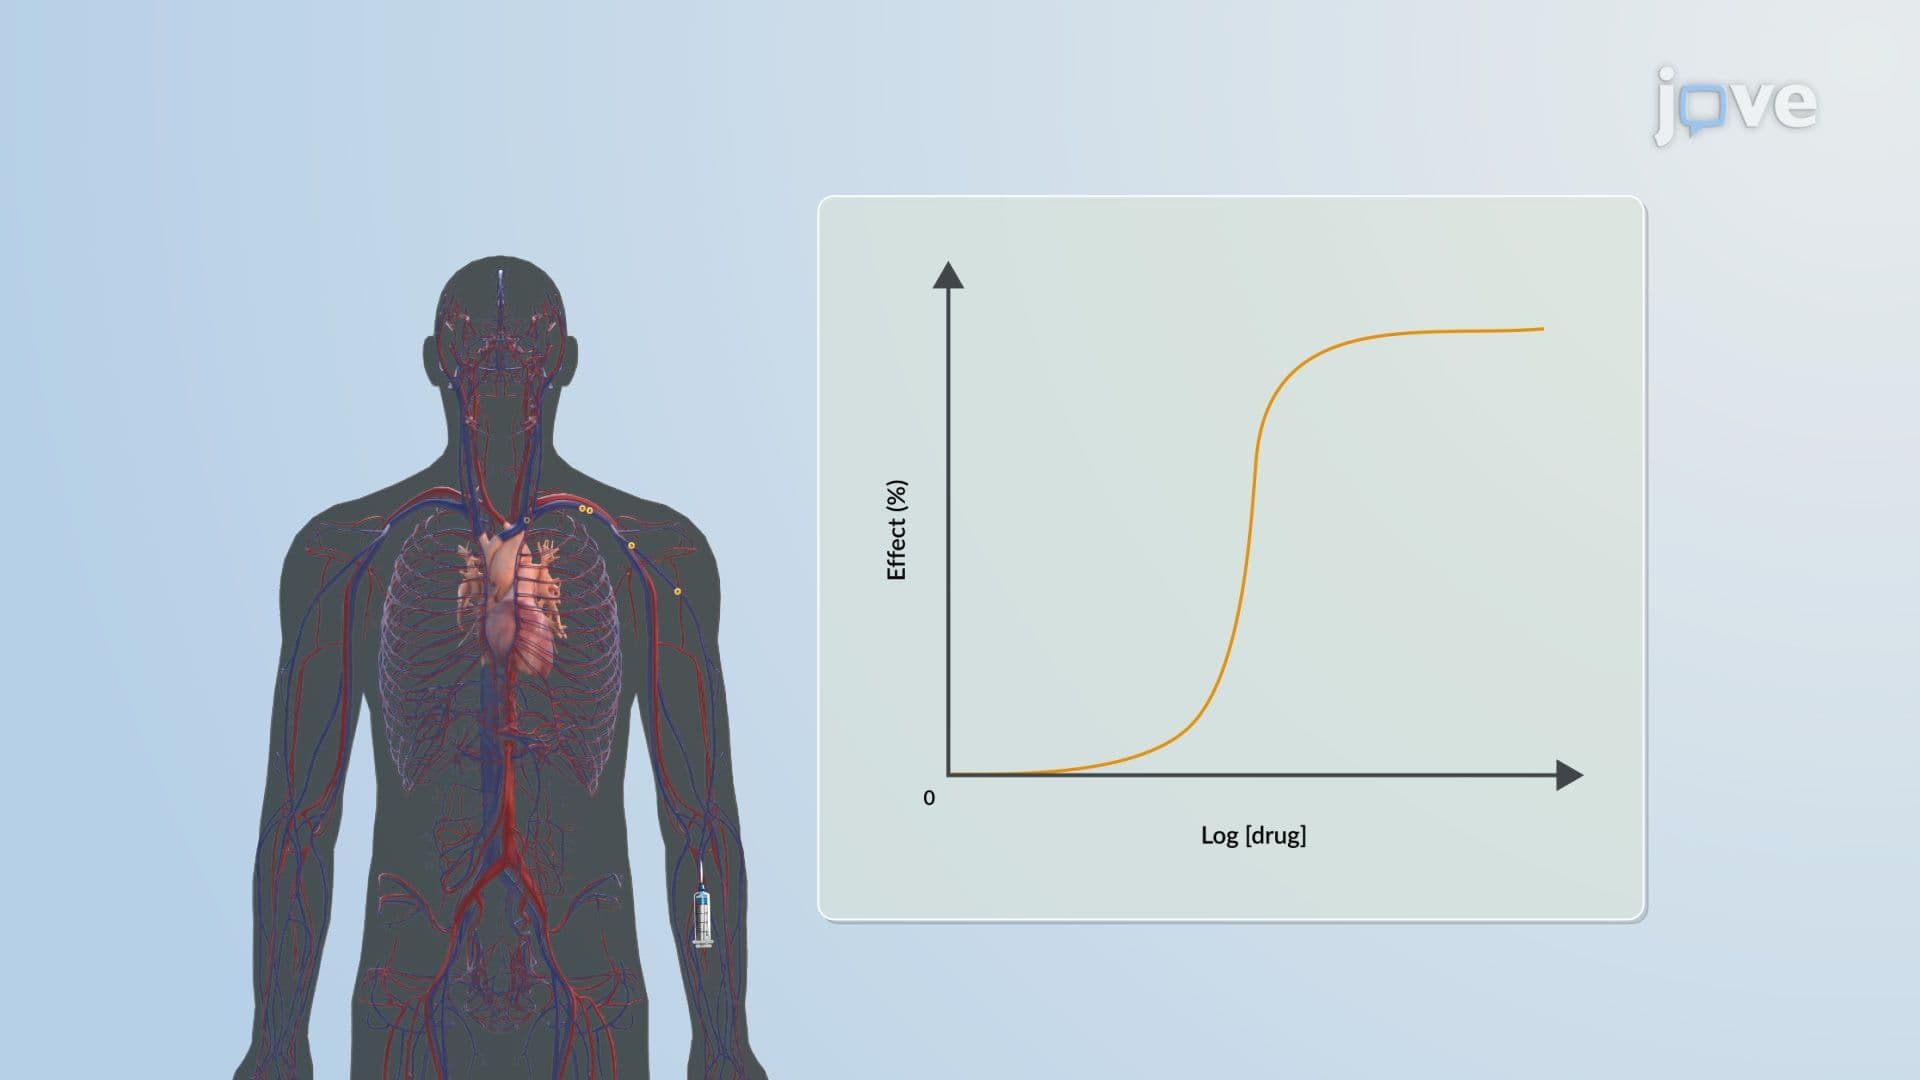
For drugs producing a quantal response, onset occurs when plasma concentration reaches a minimum effective level (Cmin). The drug's action duration depends on how long the plasma concentration remains above Cmin.Two primary factors influence this duration: dose size and the rate of drug removal from the action site. Both depend on the drug's redistribution to poorly perfused tissues and elimination processes. A larger dose promotes rapid onset and prolongs the effect's duration.Consider a...
Pharmacokinetic–Pharmacodynamic Relationship: Intensity of Dose-Effect Relationship01:23

Pharmacokinetic–Pharmacodynamic Relationship: Intensity of Dose-Effect Relationship

Pharmacodynamics explores the relationship between drug concentration and its effect. In a quantal response drug, the duration of action better correlates with drug concentration, while for graded effect drugs, the intensity of response is more relevant. This intensity depends on the dose, drug removal rate, and the region of the concentration–response curve.The concentration–response curve can be divided into three regions. Region 3 (80–100% maximum response) demonstrates that even as drug...
