Related Experiment Video
Updated: May 27, 2026

Digital Home-Monitoring of Patients after Kidney Transplantation: The MACCS Platform
Published on: April 12, 2021
Long-term evolution of the mineral metabolism after renal transplantation: a prospective, single-center cohort study
J Van de Cauter1, J Sennesael, P Haentjens
1Department of Internal Medicine, Universitair Ziekenhuis Brussel, Brussels, Belgium.

Background:
Abnormalities in bone and mineral metabolism are common after renal transplantation (RT) but information on their long-term time course is scarce.
Objectives:
(1) Evaluate the time course of biochemical parameters of bone and mineral metabolism over 60 months after RT; (2) identify predictors for persistent hyperparathyroidism (HPT).
Design:
Prospective, longitudinal, single-center cohort study.
Methods:
We determined serum levels (mean values ± standard deviations) of intact parathyroid hormone (iPTH), calcium (Ca), phosphorus (P), magnesium (Mg), alkaline phosphatase (APh), calcitriol, and creatinine (Cr) preoperatively as well as 6, 12, 24, 36, 48, and 60 months after cadaveric RT in 49 patients. We in addition recorded demographic, clinical, and therapeutic data.
Results:
Pretransplantation iPTH stabilized from 194.2 ± 273.5 to 71.5 ± 50.7 ng/L at 6 months. Serum Ca (9.5 ± 1.1 mg/dL) and APh (81.9 ± 42.1 U/L) did not change. Baseline serum P (5.7 ± 1.8 mg/dL) and serum Mg (2.4 ± 0.4 mg/dL) decreased to normal ranges from month 6 onward. Low baseline calcitriol (22.4 ± 21.8 pmol/L) normalized slowly by 12 months (95.4 ± 46.7 pmol/L). Stable graft function (53.2 ± 15.8 mL/min) was achieved from 6 months onward. By 60 months, 26.5% of patients had a serum Ca above 9.8 mg/dL and serum P below 2.7 mg/dL; 22.4%, an Mg below 1.7 mg/dL and 8.2%, a serum iPTH more than 2.5-fold the upper limit of normal. Upon multiple regression analyses the iPTH at 60 months was influenced by a dialysis duration ≥ 2 years (β = 0.259, P = .003), body mass index > 25 kg/m(2) (β = 0.257, P = .006), baseline iPTH (β = 0.182, P = .036), serum Cr (β = 0.268, P = .002) and Mg (β = -0.242, P = .006).
Conclusions:
Hypercalcemia, hypophosphatemia, hypomagnesemia, and elevated iPTH persist in a subset of post-RT patients. Pretransplantation iPTH and obesity, dialysis duration, and posttransplant serum creatininemia and hypomagnesemia independently contribute to persistent HPT.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:16
Kidney Transplant III: Nursing Management
 01:29
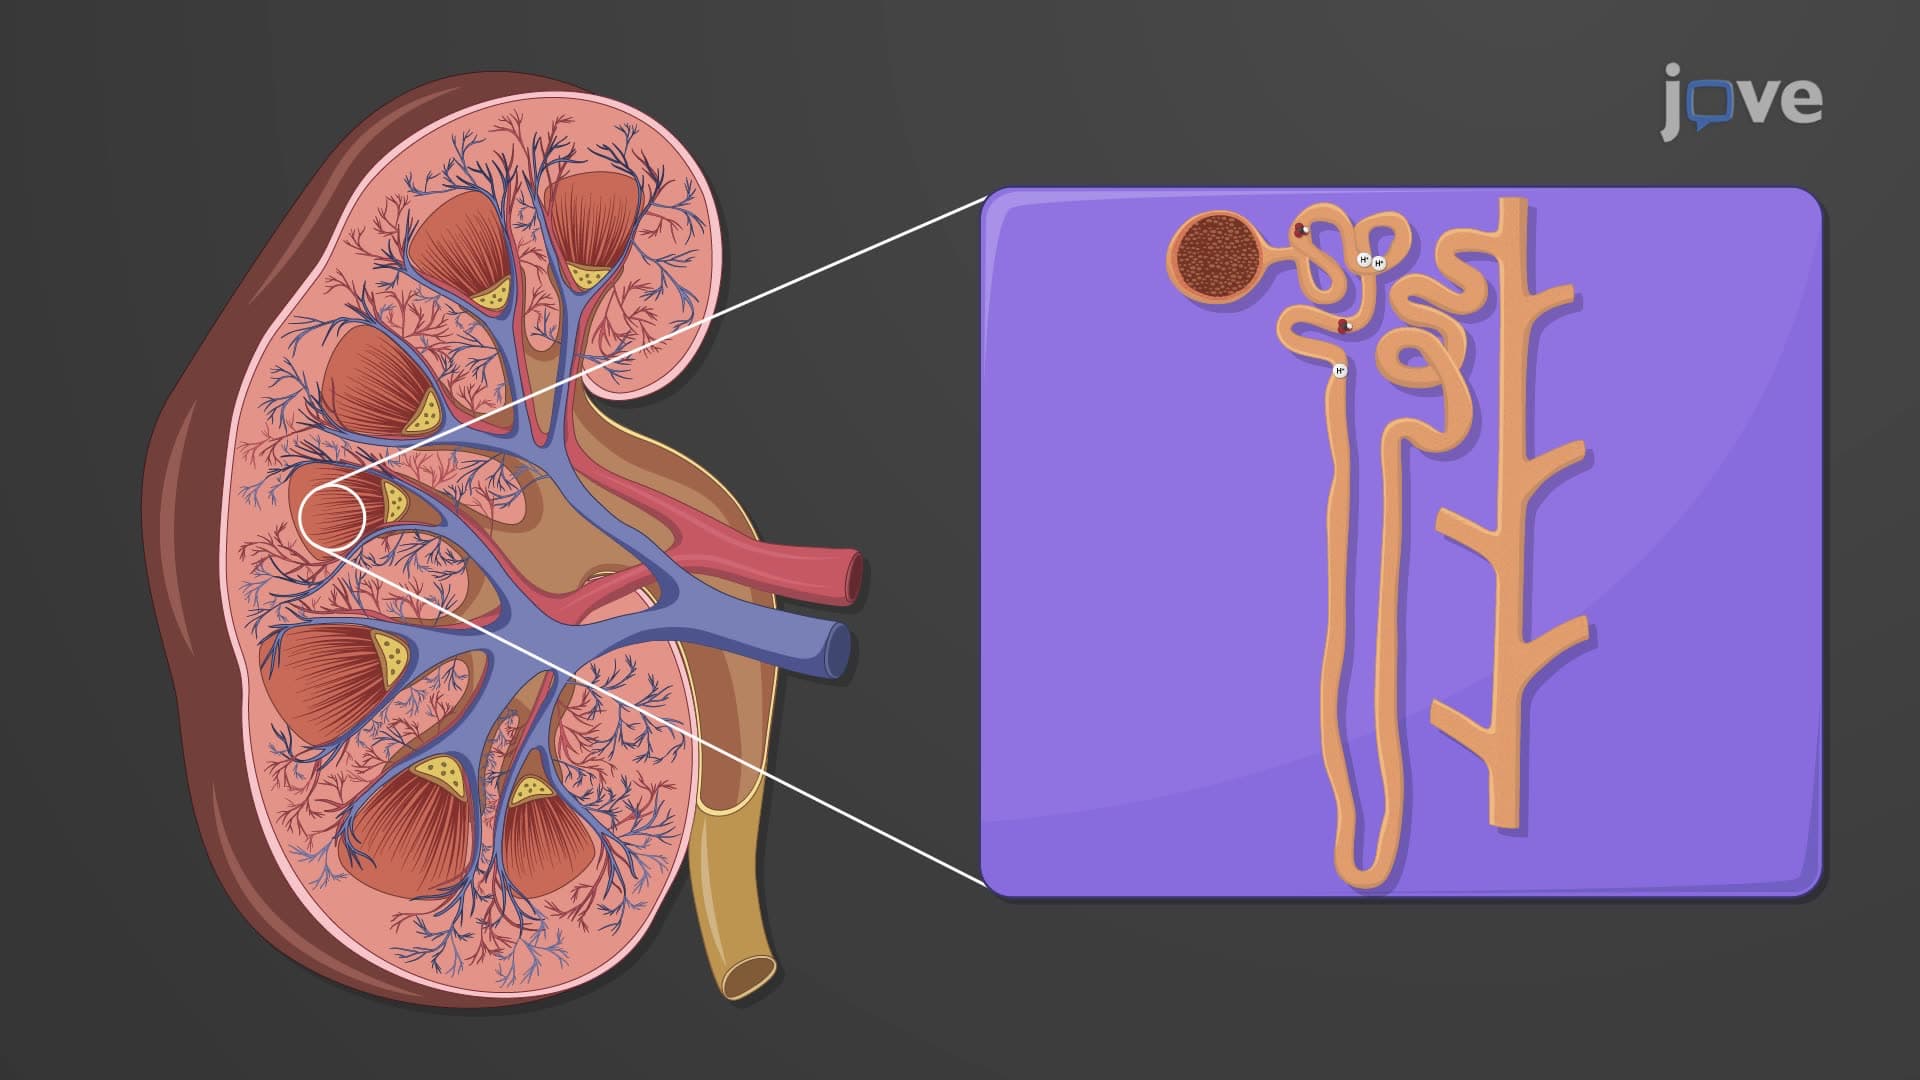
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:26
Kidney Transplant II: Surgical Procedure
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention