Related Experiment Video
Updated: May 27, 2026
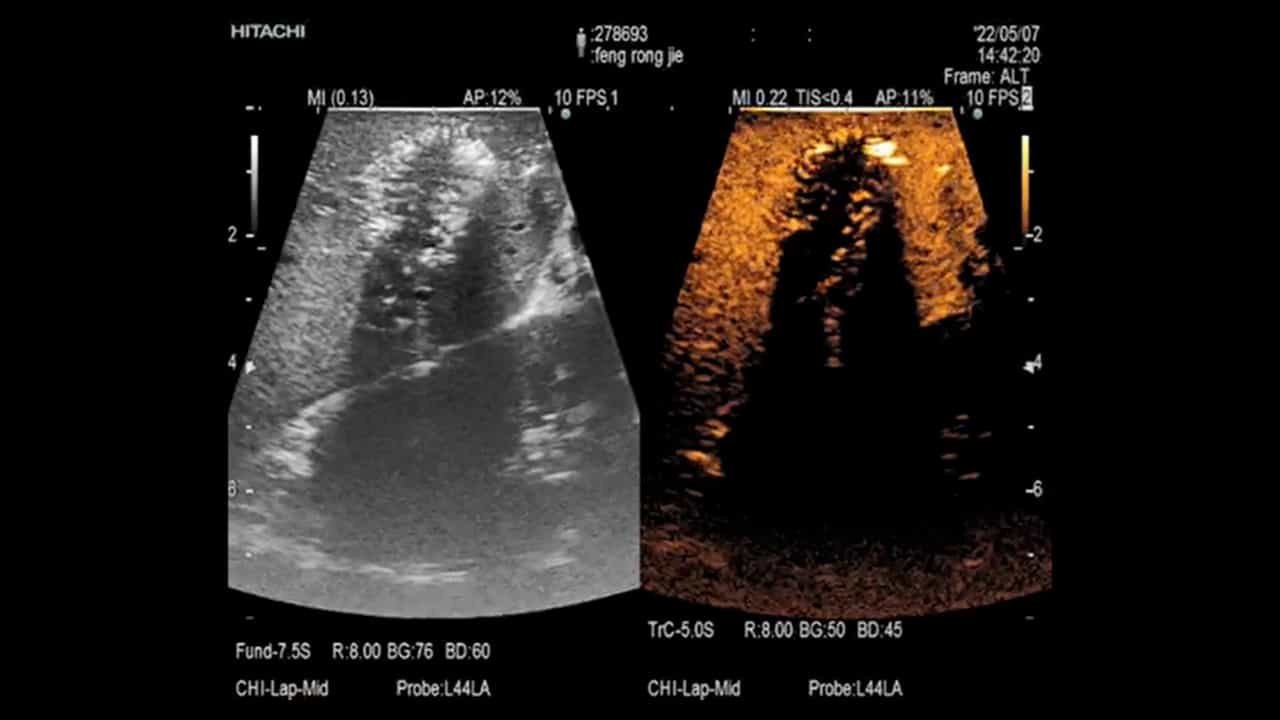
Application of Laparoscopic Hepatectomy Combined with Intraoperative Microwave Ablation in Colorectal Cancer Liver Metastasis
Published on: March 3, 2023
Intraoperative microwave ablation of pulmonary malignancies with tumor permittivity feedback control: ablation and
Farrah J Wolf1, Bassam Aswad, Thomas Ng
1Department of Diagnostic Imaging, Office of Research Administration, Alpert Medical School of Brown University, Rhode Island Hospital, 593 Eddy St, Providence, RI 02903, USA.

Purpose:
To determine histologic changes induced by microwave ablation (MWA) in patients with pulmonary malignancy by using an ablation system with tumor permittivity feedback control, enabling real-time modulation of energy power and frequency.
Materials And Methods:
Institutional review board approval and patient informed consent were obtained for this prospective HIPAA-complaint ablation and resection study. Between March 2009 and January 2010, 10 patients (four women, six men; mean age, 71 years; age range, 52-82 years) underwent intraoperative MWA of pulmonary malignancies. Power (10-32 W) and frequency (908-928 MHz) were continuously adjusted by the generator to maintain a temperature of 110°-120°C at the 14-gauge antenna tip for one 10-minute application. After testing for an air leak, tumors were resected surgically. Gross inspection, slicing, and hematoxylin-eosin (10 specimens) and nicotinamide adenine dinucleotide (six specimens) staining were performed.
Results:
Tumors included adenocarcinomas (n = 5), squamous cell carcinomas (n = 3), and metastases from endometrial (n = 1) and colorectal (n = 1) primary carcinomas. Mean maximum tumor diameter was 2.4 cm (range, 0.9-5.0 cm), and mean maximum volume was 8.6 cm(3) (range, 0.5-52.7 cm(3)). One air leak was detected. Five of 10 specimens were grossly measurable, revealing a mean maximum ablation zone diameter of 4.8 cm (range, 3.0-6.5 cm) and a mean maximum ablation zone volume of 15.1 cm(3) (range, 7.3-25.1 cm(3)). At hematoxylin-eosin staining, coagulation necrosis was observed in all ablation zones, extended into the normal lung in nine of 10 specimens, and up to blood vessel walls without evidence of vessel (>4 mm) thrombosis. Nicotinamide adenine dinucleotide staining enabled confirmation of no viability within ablation zones extending into normal lung in five of six specimens.
Conclusion:
MWA with tumor permittivity feedback control results in cytotoxic intratumoral temperatures and extension of ablation zones into aerated peritumoral pulmonary parenchyma, possibly forming the equivalent of an oncologic resection margin.