Related Experiment Video
Updated: May 27, 2026
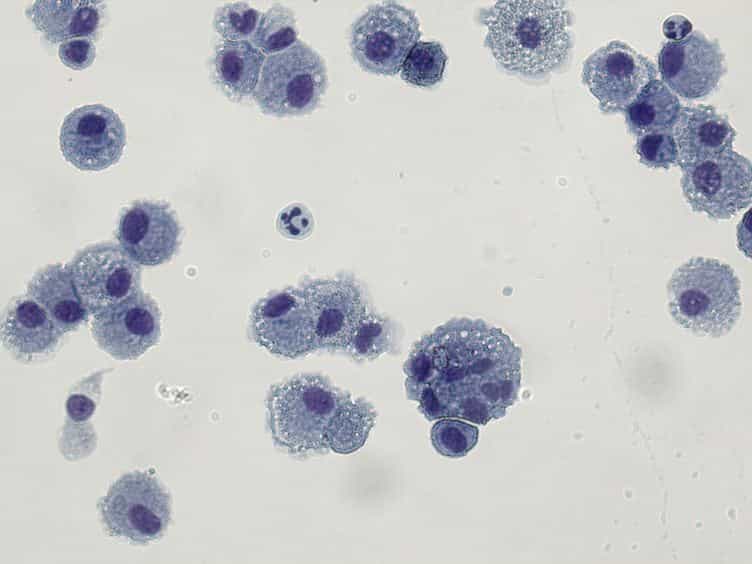
Bronchoalveolar Lavage (BAL) for Research; Obtaining Adequate Sample Yield
Published on: March 24, 2014
Risk factors that affect the surgical outcome in the management of focal bronchiectasis in a developed country
Miyako Hiramatsu1, Yuji Shiraishi, Yutsuki Nakajima
1Section of Chest Surgery, Fukujuji Hospital, and Department of Mathematics, Tokyo University of Science, Tokyo, Japan. mykhrmt@a07.itscom.net

Background:
The purpose of this study was to demonstrate our surgical experience for focal bronchiectasis in the setting of modern diagnostic modalities and state-of-the-art medical treatment in a developed country.
Methods:
Thirty-one patients undergoing 33 lung resections for the treatment of focal bronchiectasis from 1991 to 2009 were reviewed. The mean age was 54 years. Twenty-nine patients (94%) were female; 21 patients (68%) had nontuberculous mycobacterial infection; and 22 patients (71%) received preoperative multiple-drug regimens containing clarithromycin. Five patients (16%) were in an immunocompromised status. All were diagnosed by chest computed tomography scan, and either the right middle lobe or left lingula were involved in 29 (94%). The curve for relapse-free interval was estimated by Kaplan-Meier methods. The factors that affected this curve were examined using Cox's regression analysis.
Results:
Operative morbidity and mortality were 18% and 0%, respectively. All patients became asymptomatic postoperatively. During the median follow-up of 48 months (11 to 216), 8 patients (26%) experienced recurrence, and the mean relapse-free interval was 34 months (3 to 216). By univariate analysis, an immunocompromised status (p=0.017), Pseudomonas aeruginosa infection (p=0.040), the preoperative extent of bronchiectatic lesion (p=0.013), and the extent of residual bronchiectasis after surgery (p=0.003) were significantly associated with the shorter relapse-free interval. By multivariate analysis, an immunocompromised status (p=0.039), Pseudomonas aeruginosa infection (p=0.033), and the extent of residual bronchiectasis (p=0.009) were independent and significant factors.
Conclusions:
Complete resection of bronchiectasis while the disease is localized and is free from Pseudomonas aeruginosa infection is the key for a success. Also, immunocompromised status was suggested to be a risk factor.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation