Related Experiment Video
Updated: May 27, 2026
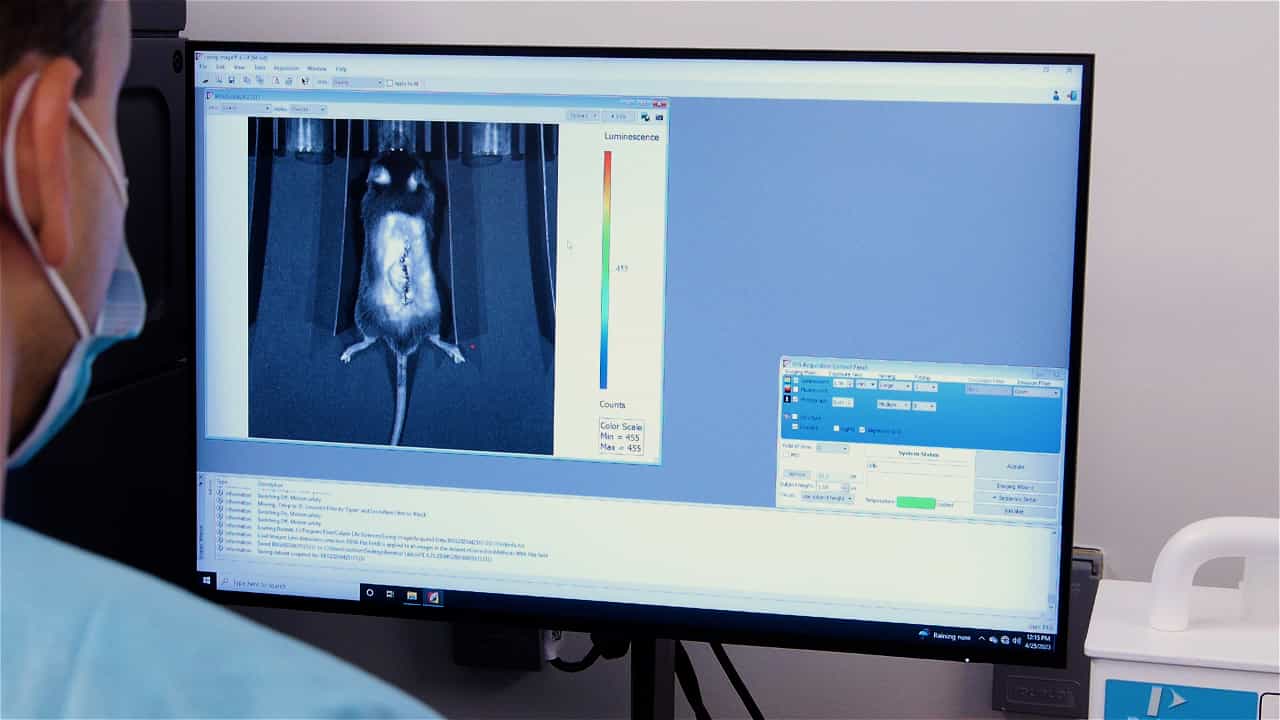

In Vivo Mouse Model of Spinal Implant Infection
Published on: June 23, 2020
Bacterial wound contamination during simple and complex spinal procedures. A prospective clinical study
Ioannis D Gelalis1, Christina M Arnaoutoglou, Angelos N Politis
1Department of Orthopaedics, University of Ioannina, School of Medicine, 11 Pantazidi St, Ioannina 45221, Greece. idgelalis@gmail.com

Background Context:
Spinal procedures have a potential of intraoperative contamination. C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) have been used to diagnose postoperative infections after spinal surgery. However, it has not been demonstrated if there is an association between surgical site contamination and clinical manifestation of postoperative infection based on inflammatory markers and patients' clinical course.
Purpose:
The purpose of this prospective study was to evaluate the association between surgical site contamination and the development of a postoperative infection in simple and complex surgical procedures. C-reactive protein and ESR levels were observed. The correlation between their values, surgical time, type of surgical procedures, and contaminated surgical sites was investigated.
Study Design:
Prospective clinical study.
Patient Sample:
The study consisted of 40 patients divided into two groups. Group A included 20 patients (mean age, 46.2 years; 12 women and 8 men) who underwent an open discectomy for a lumbar herniated disc. Group B consisted of 20 patients (mean age, 67.9 years; 11 women and 9 men) who underwent a decompression and instrumented fusion for lumbar spinal stenosis. They were followed up for an average of 26.7 months (range, 11-40 months).
Outcome Measures:
Samples were obtained for cultures in standard time intervals during surgery. The types of bacteria cultured were evaluated, and CRP and ESR levels were measured.
Methods:
Simple lumbar discectomy (Group A, 20 patients) and instrumented lumbar decompression for degenerative lumbar stenosis (Group B, 20 patients) were performed in a prospective consecutive series of patients. All patients were operated by the same surgeon in the same operating room. Surgical site preparation in each patient was done by a standard manner. Samples were obtained for cultures in standard time intervals during surgery. C-reactive protein and ESR levels were measured preoperatively on the 3rd, 7th, and 21st postoperative days, and the clinical course of each patient was recorded.
Results:
From 40 patients, three patients in Group A and five patients in Group B, a total of eight patients (20%) had positive cultures for bacteria. There was no statistical significance between contamination and duration of surgery in both groups. None of the patients with positive intraoperative cultures developed any clinical signs of superficial or deep postoperative spinal infection, and no additional antibiotic treatment was administered. Three patients with negative cultures developed a postoperative infection. There were no differences in CRP and ESR values between patients with contamination and noncontamination in both groups. C-reactive protein and ESR levels were significantly elevated in complex procedures (Group B) than in simple procedures (Group A). Statistical analysis of CRP and ESR values in both groups and types of bacteria cultured intraoperatively are presented.
Conclusions:
The results of this study demonstrate that intraoperative contamination can occur during simple and complex spinal procedures. In the absence of postoperative signs of infection in patients with intraoperative contamination, there is no need of continuing antibiotic treatment. Postoperative kinetics of CRP and ESR showed to be the same in patients with and without intraoperative contamination. Higher levels of inflammatory markers were noted in complex spinal procedures where instrumentation was applied.
Insights
Intraoperative contamination during spinal surgery does not necessitate antibiotics if no infection signs appear. Inflammatory markers like C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) remain similar in contaminated vs. uncontaminated cases.
Area of Science:
- Spinal Surgery
- Infectious Disease
- Inflammatory Markers
Background:
- Spinal procedures carry a risk of intraoperative contamination.
- C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) are used to detect postoperative infections.
- The association between surgical site contamination and clinical infection signs, based on inflammatory markers, requires further investigation.
Purpose of the Study:
- To assess the link between surgical site contamination and postoperative infection development in spinal surgery.
- To monitor CRP and ESR levels and correlate them with surgical factors.
- To investigate the relationship between inflammatory marker values, surgical duration, procedure type, and contamination.
Main Methods:
- Prospective clinical study involving 40 patients undergoing spinal procedures.
- Patients were divided into two groups: simple discectomy (Group A) and complex decompression/fusion (Group B).
- Intraoperative cultures, CRP, and ESR measurements were performed, with follow-up for an average of 26.7 months.
Main Results:
- 20% of patients had positive intraoperative cultures; no significant correlation with surgery duration.
- No patients with positive cultures developed clinical infection signs; no additional antibiotics were needed.
- CRP and ESR levels were significantly higher in complex procedures (Group B) than in simple ones (Group A).
Conclusions:
- Intraoperative contamination is possible in both simple and complex spinal surgeries.
- Antibiotic treatment is not required for intraoperative contamination if no postoperative infection signs are present.
- Postoperative CRP and ESR kinetics are similar in contaminated and uncontaminated cases; higher levels indicate complex procedures.
