Related Experiment Video
Updated: May 27, 2026


Determining Glucose Metabolism Kinetics Using 18F-FDG Micro-PET/CT
Published on: May 2, 2017
Clopidogrel pharmacodynamics and pharmacokinetics in the fed and fasted state: a randomized crossover study of
Fabrice Hurbin1, Xavier Boulenc, Nikki Daskalakis
1DSAR–Drug Disposition, sanofi-aventis Recherche Développement, Montpellier, France. Fabrice.Hurbin@sanofi-aventis.com

Abstract:
Clopidogrel requires CYP450-mediated hepatic metabolism to form its active metabolite (clopi-H4). This randomized, placebo-controlled, crossover study was designed to characterize the effect of a high-fat or standard breakfast on adenosine diphosphate (ADP)-induced platelet aggregation and exposure to unchanged clopidogrel and clopi-H4 following clopidogrel (300-mg loading dose, 75 mg/d for 4 days) in 72 healthy men. At day 5 and as assessed by liquid chromatography-tandem mass spectrometry, unchanged clopidogrel area under the concentration- time curve from 0 to 24 hours (AUC(0-24)) increased 3.32-fold (90% confidence interval [CI], 2.88-3.84), and clopi-H4 AUC(0-24) decreased nonsignificantly by 12% (90% CI, 0.82-0.94) upon administration of clopidogrel with a standard breakfast. The estimated treatment difference in maximum platelet aggregation (MPA) induced by ADP 5 µM and assessed by light transmission aggregometry was 4.7%, with the 90% CI (0.9%-8.5%) contained within the prespecified equipotency range of ±15%. The mean ± standard deviation of day 5 inhibition of platelet aggregation was 49.7% ± 17.2% and 54.0% ± 13.3% in the fed and fasted states, respectively. Despite increased unchanged clopidogrel and slightly decreased clopi-H4 exposure following clopidogrel administration, the numerical increase in MPA in the fed versus fasted state was small and within the prespecified limit of equipotency. These findings confirm that clopidogrel can be taken with or without food.

Related Concept Videos
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:30
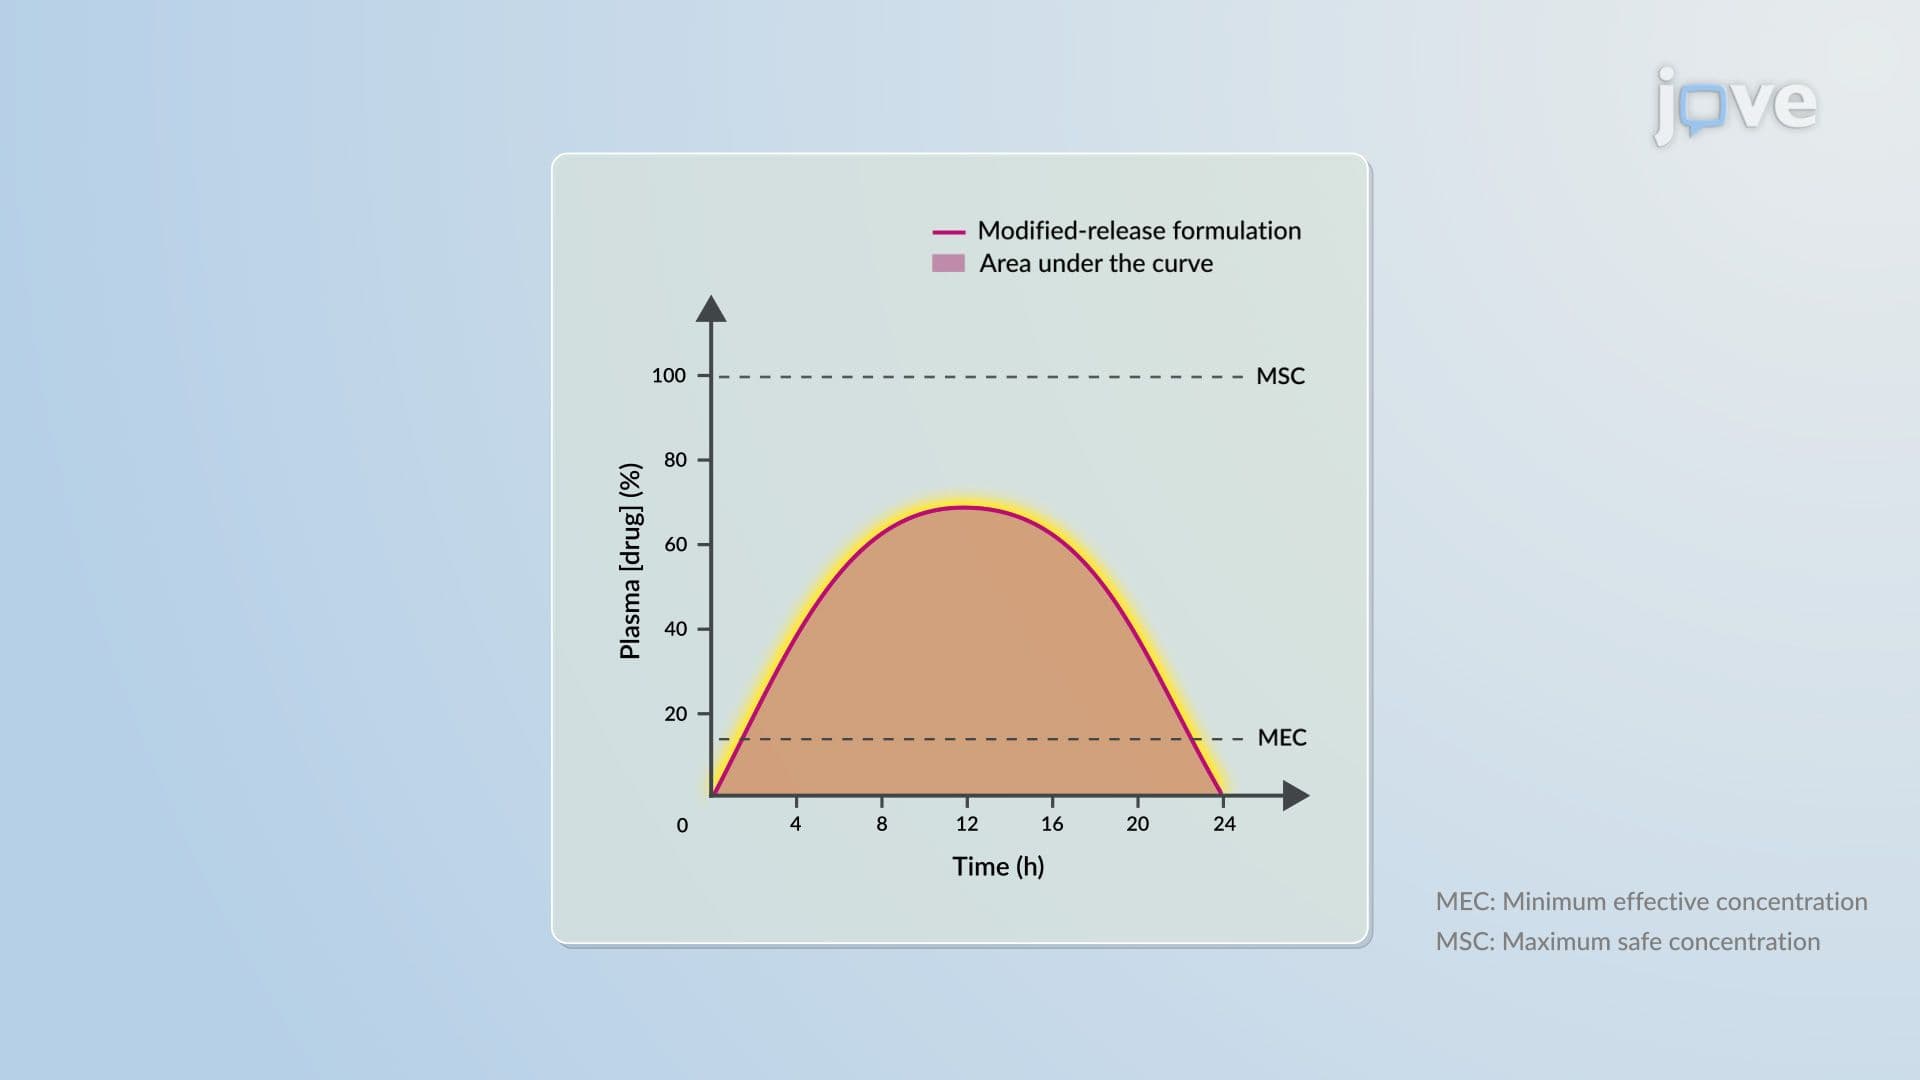
Modified-Release Drug Delivery Systems: Bioavailability
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment