Related Experiment Video
Updated: May 27, 2026

Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Dose-effect relationships for individual pelvic floor muscles and anorectal complaints after prostate radiotherapy
Robert Jan Smeenk1, Aswin L Hoffmann, Wim P M Hopman
1Department of Radiation Oncology, Radboud University Nijmegen Medical Centre, Nijmegen, The Netherlands. r.smeenk@rther.umcn.nl

Purpose:
To delineate the individual pelvic floor muscles considered to be involved in anorectal toxicity and to investigate dose-effect relationships for fecal incontinence-related complaints after prostate radiotherapy (RT).
Methods And Materials:
In 48 patients treated for localized prostate cancer, the internal anal sphincter (IAS) muscle, the external anal sphincter (EAS) muscle, the puborectalis muscle (PRM), and the levator ani muscles (LAM) in addition to the anal wall (Awall) and rectal wall (Rwall) were retrospectively delineated on planning computed tomography scans. Dose parameters were obtained and compared between patients with and without fecal urgency, incontinence, and frequency. Dose-effect curves were constructed. Finally, the effect of an endorectal balloon, which was applied in 28 patients, was investigated.
Results:
The total volume of the pelvic floor muscles together was about three times that of the Awall. The PRM was exposed to the highest RT dose, whereas the EAS received the lowest dose. Several anal and rectal dose parameters, as well as doses to all separate pelvic floor muscles, were associated with urgency, while incontinence was associated mainly with doses to the EAS and PRM. Based on the dose-effect curves, the following constraints regarding mean doses could be deduced to reduce the risk of urgency: ≤ 30 Gy to the IAS; ≤ 10 Gy to the EAS; ≤ 50 Gy to the PRM; and ≤ 40 Gy to the LAM. No dose-effect relationships for frequency were observed. Patients treated with an endorectal balloon reported significantly less urgency and incontinence, while their treatment plans showed significantly lower doses to the Awall, Rwall, and all pelvic floor muscles.
Conclusions:
Incontinence-related complaints show specific dose-effect relationships to individual pelvic floor muscles. Dose constraints for each muscle can be identified for RT planning. When only the Awall is delineated, substantial components of the continence apparatus are excluded.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
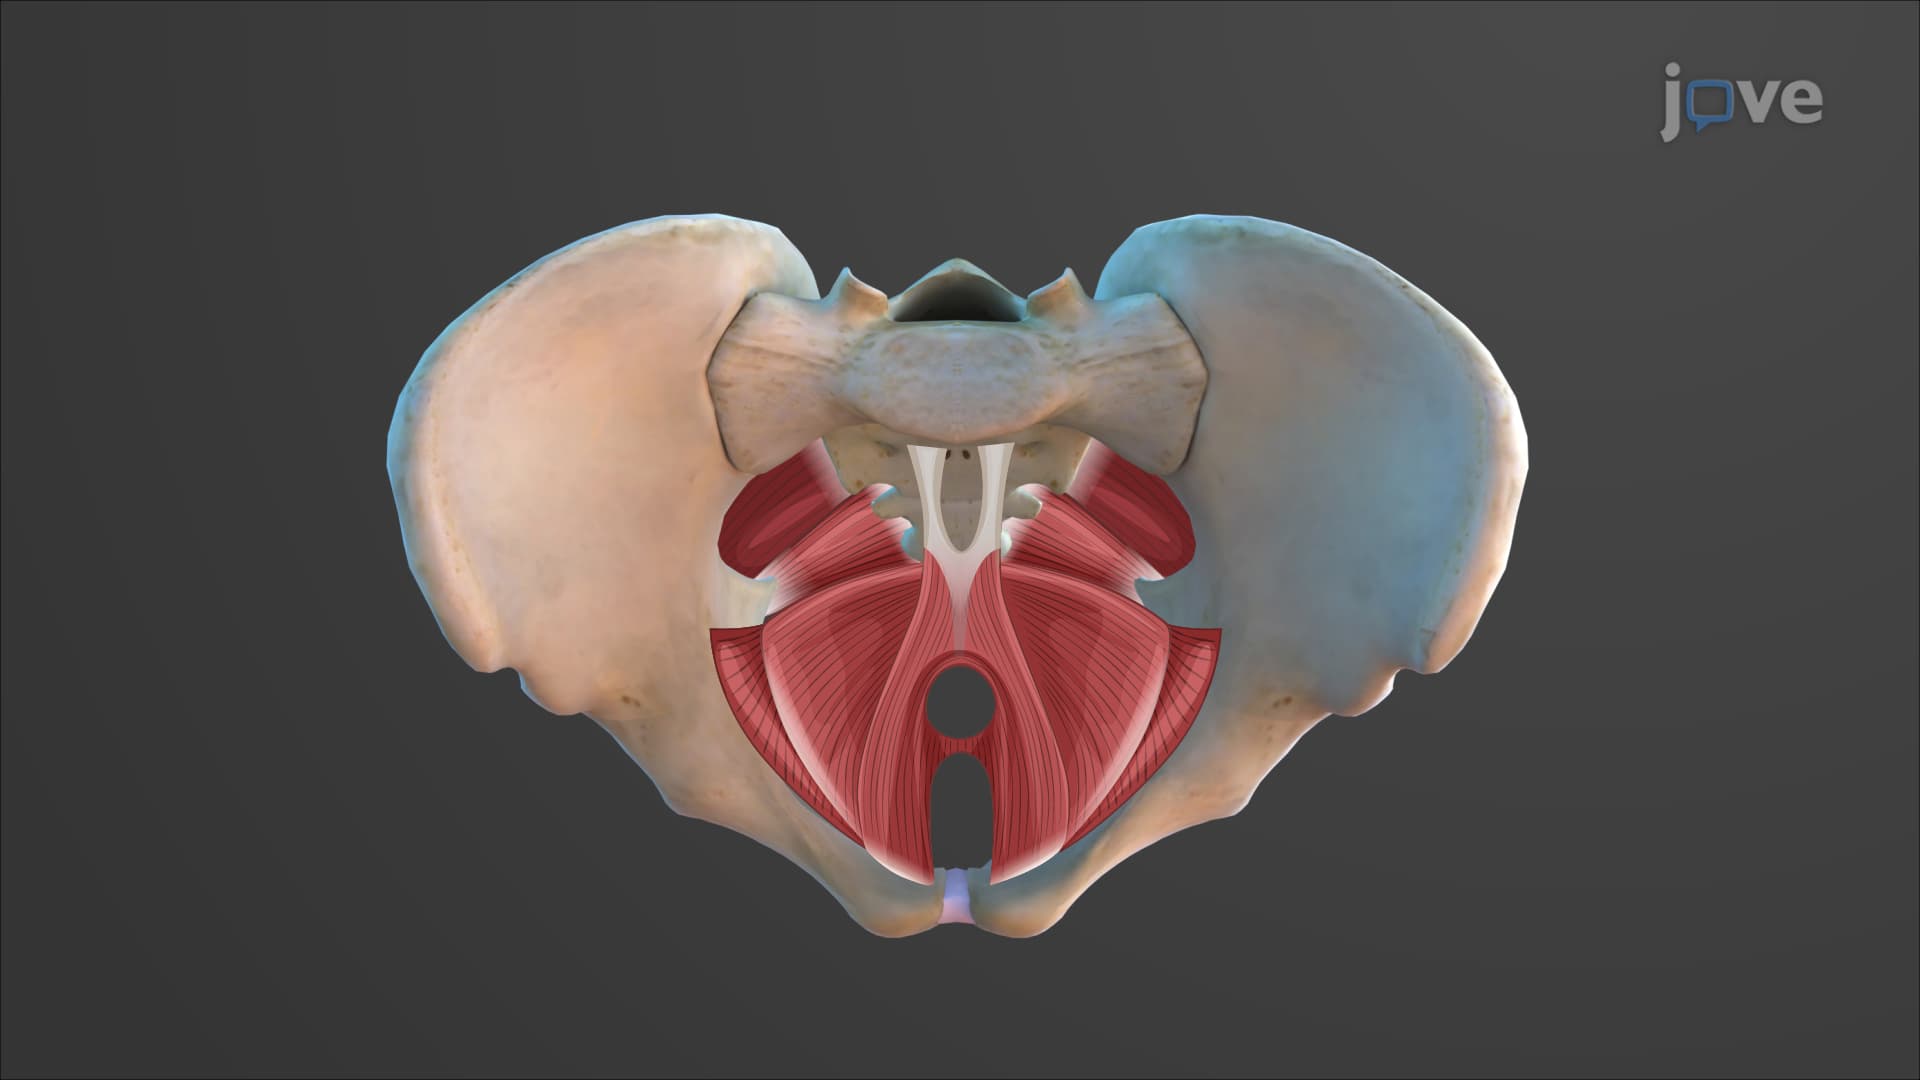 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists