Related Experiment Video
Updated: May 26, 2026
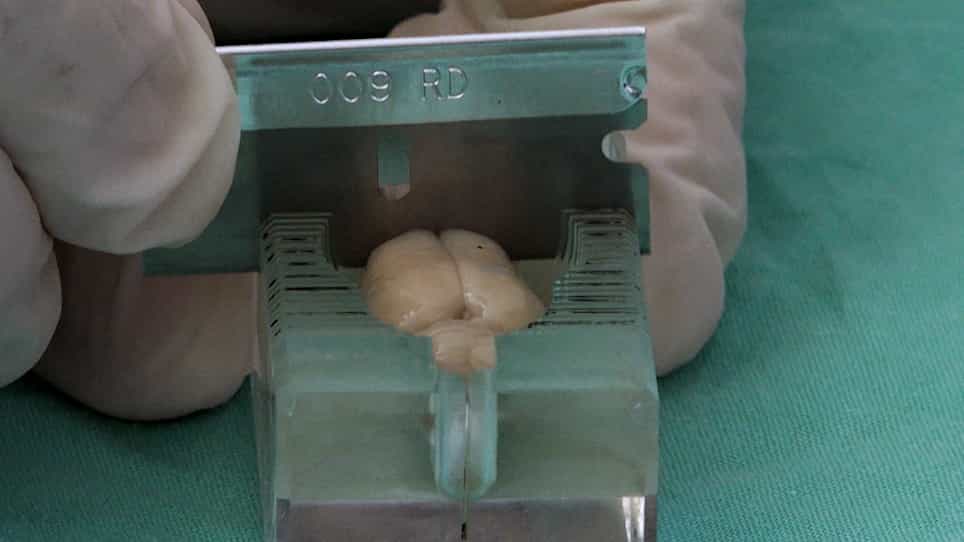
Measuring Post-Stroke Cerebral Edema, Infarct Zone and Blood-Brain Barrier Breakdown in a Single Set of Rodent Brain Samples
Published on: October 23, 2020
The severity of ischemia determines and predicts malignant brain edema in patients with large middle cerebral artery
Christian Dohmen1, Norbert Galldiks, Bert Bosche
1Max Planck Institute for Neurological Research, University of Cologne, Cologne, Germany. christian.dohmen@uk-koeln.de

Background:
In order to determine the impact of the severity of ischemia on malignant edema formation, we investigated various degrees of perfusional deficit by (11)C-flumazenil PET in patients with large middle cerebral artery (MCA) infarction.
Methods:
17 patients with large MCA stroke were included. Cerebral blood flow (CBF) was measured 15.9 ± 6.4 h after the ictus. Patients were divided into a malignant (n = 9) and a benign group (n = 8) as a function of their clinical courses and edema. Edema was measured as maximal midline shift on follow-up CTs. Total hypoperfusion volume was divided into different subvolumes according to the degree of CBF reduction.
Results:
Subvolumes of severe ischemia relative to total ischemic area were significantly larger in the malignant group than in the benign group and were significantly correlated with edema formation. The highest correlation and best predictive values for edema formation with a sensitivity, specificity, and a positive and negative predictive value of 100% were found for subvolumes with severe ischemia. Correlation coefficients and prediction decreased for subvolumes with less severe perfusional deficit, pointing to the risk of misclassifying patients when relying on the volume of total perfusional deficit alone.
Conclusions:
Malignant MCA infarction seems to be determined more by the volume of severe perfusional deficit than that of total perfusional deficit. Assessment of severely ischemic areas allows prediction of malignant edema formation and might help to select candidates for hemicraniectomy.
Insights
Severe ischemia, not total hypoperfusion, predicts malignant edema in middle cerebral artery (MCA) infarction. Assessing severely ischemic areas accurately predicts edema and may guide treatment selection for stroke patients.
Area of Science:
- Neurology
- Neuroimaging
- Stroke Medicine
Background:
- Investigated the impact of ischemia severity on malignant edema formation in large middle cerebral artery (MCA) infarction.
- Utilized (11)C-flumazenil Positron Emission Tomography (PET) to assess varying degrees of perfusional deficit.
Purpose of the Study:
- To determine the relationship between the severity of ischemia and malignant edema formation.
- To evaluate the predictive value of different hypoperfusion volumes for edema development in MCA stroke.
Main Methods:
- Included 17 patients with large MCA stroke, measuring cerebral blood flow (CBF) hours after ictus.
- Categorized patients into malignant (n=9) and benign (n=8) groups based on clinical course and edema.
- Quantified edema via maximal midline shift on CT scans and analyzed hypoperfusion subvolumes based on CBF reduction.
Main Results:
- Subvolumes of severe ischemia were significantly larger in the malignant group and correlated strongly with edema.
- Severely ischemic subvolumes demonstrated 100% sensitivity and specificity in predicting edema formation.
- Predictive accuracy decreased for less severe hypoperfusion, highlighting risks of using total deficit volume alone.
Conclusions:
- Malignant MCA infarction is primarily determined by the volume of severe, not total, perfusional deficit.
- Assessing severely ischemic areas enables prediction of malignant edema.
- This assessment may aid in selecting stroke patients who could benefit from hemicraniectomy.
Related Concept Videos
 01:22
Cerebral Edema ll: Pathophysiology
 01:15
Ischemic Stroke ll: Pathophysiology
 01:21
Cytotoxic Edema: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology