Related Experiment Video
Updated: May 23, 2026


Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
What we should know about the cellular and tissue response causing catheter obstruction in the treatment of
Carolyn A Harris1, James P McAllister
1Department of Neurosurgery, Division of Pediatric Neurosurgery, University of Utah, Salt Lake City, Utah 84132, USA. carolyn.anne.harris@gmail.com

Insights
Ventricular catheter obstruction is a common problem in hydrocephalus treatment. This review explores modifications to shunts, including surgical strategies and catheter design, to prolong their lifespan and improve patient outcomes.
Area of Science:
- Biomedical Engineering
- Neurosurgery
- Materials Science
Background:
- Hydrocephalus treatment often involves cerebrospinal fluid (CSF) shunting.
- Ventricular catheter obstruction is a significant complication, leading to shunt failure.
- Obstruction can be caused by normal brain cells or pathological cells in CSF.
Purpose of the Study:
- To review the causes of ventricular catheter obstruction in hydrocephalus.
- To identify modifications to ventricular catheters that may reduce obstruction.
- To explore strategies for prolonging shunt longevity and improving patient outcomes.
Main Methods:
- Review of existing literature on ventricular catheter obstruction.
- Analysis of modifications to surgical strategies.
- Examination of changes to catheter surface chemistry and architecture.
Main Results:
- Obstruction is multifactorial, involving cellular adhesion and material interactions.
- Modifications to catheter surface properties can influence cell interaction.
- Altering catheter architecture and surgical techniques may impact obstruction rates.
Conclusions:
- A combination of approaches, including surgical, chemical, and architectural modifications, is likely necessary.
- Optimizing ventricular catheter design and implantation can improve hydrocephalus treatment.
- Prolonging shunt function is key to better patient outcomes in hydrocephalus management.
Abstract:
The treatment of hydrocephalus by cerebrospinal fluid shunting is plagued by ventricular catheter obstruction. Shunts can become obstructed by cells originating from tissue normal to the brain or by pathological cells in the cerebrospinal fluid for a variety of reasons. In this review, the authors examine ventricular catheter obstruction and identify some of the modifications to the ventricular catheter that may alter the mechanical and chemical cues involved in obstruction, including alterations to the surgical strategy, modifications to the chemical surface of the catheter, and changes to the catheter architecture. It is likely a combination of catheter modifications that will improve the treatment of hydrocephalus by prolonging the life of ventricular catheters to improve patient outcome.


Related Concept Videos
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:26
Cardiac Catheterization IV: Nursing Management
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
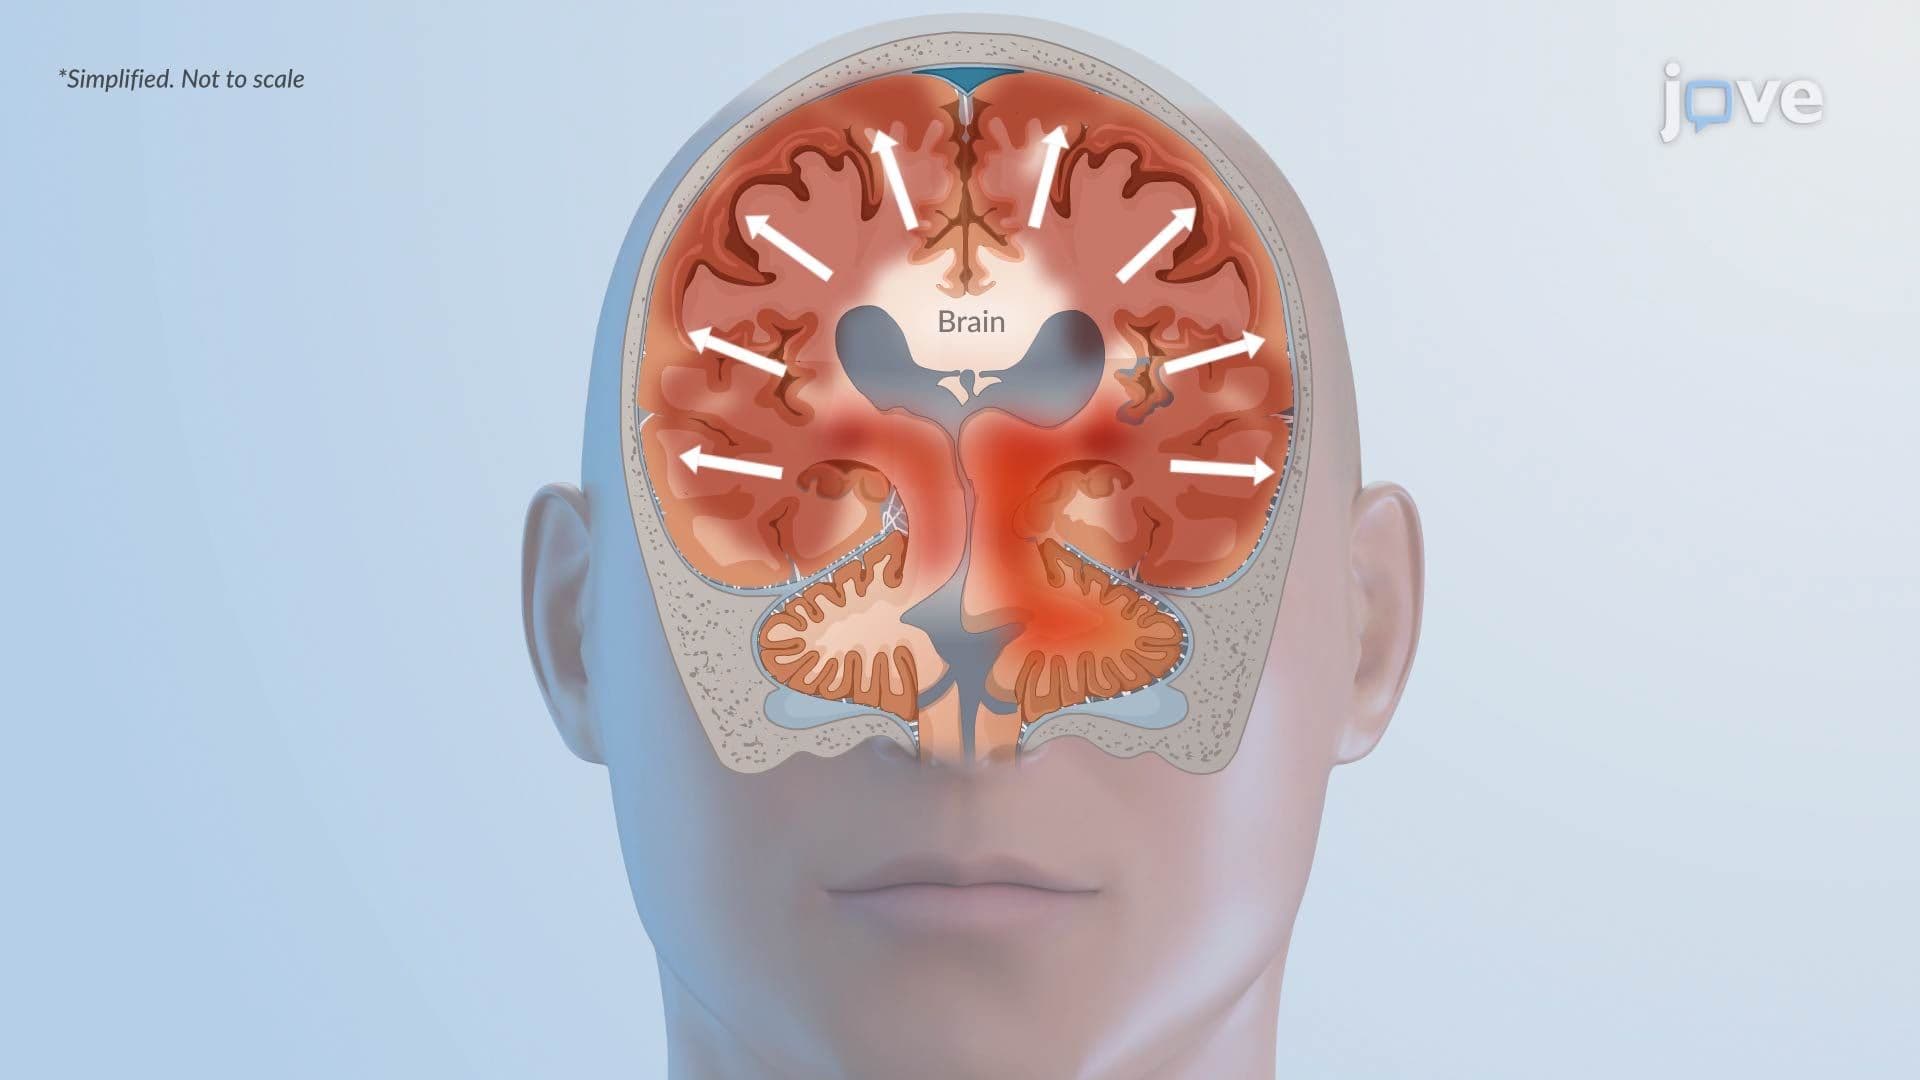
Cytotoxic Edema: Pathophysiology