Related Experiment Video
Updated: May 26, 2026
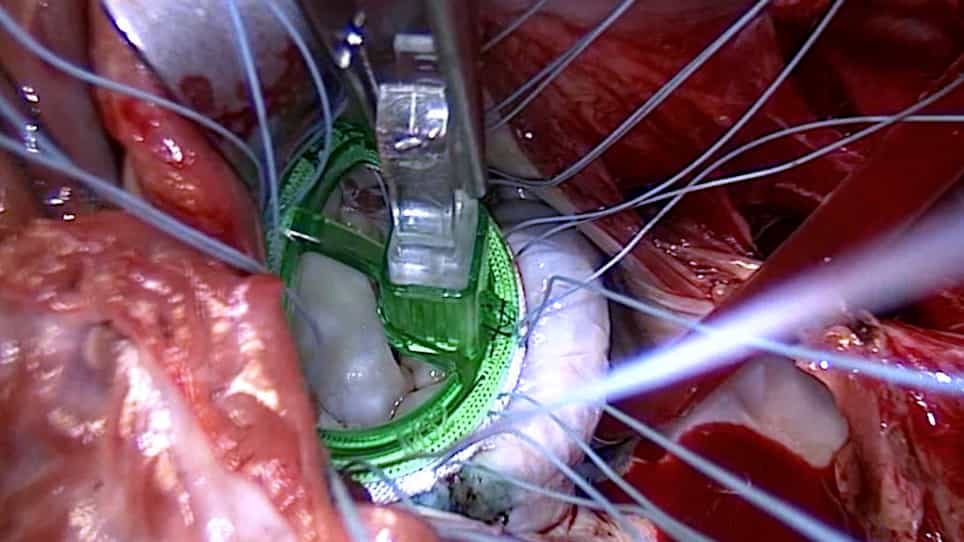
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
Analysis of risk factors for valve replacements in 5,128 cases from a single heart center in China
Li-Xin Guo1, Xu Meng, Zhao-Guang Zhang
1Department of Cardiac Surgery, Beijing Anzhen Hospital, Capital Medical University, Beijing 100029, China.

Insights
This study developed risk models to predict hospital mortality after heart valve replacement surgery. The models identified key risk factors, improving patient outcome assessment for aortic, mitral, and combined valve surgeries.
Area of Science:
- Cardiovascular Surgery
- Medical Informatics
- Clinical Risk Assessment
Background:
- Existing risk scores primarily focus on coronary artery bypass grafting (CABG), with limited models for heart valve replacement (HVR).
- HVR risk stratification is crucial due to varying disease distributions and patient complexities.
- This study aimed to develop and validate risk models for hospital mortality in cardiac valve replacement patients.
Purpose of the Study:
- To quantitatively assess risk factors for hospital mortality in cardiac valve replacement patients.
- To establish and validate predictive risk models for hospital mortality following aortic valve replacement (AVR), mitral valve replacement (MVR), and combined AVR/MVR.
Main Methods:
- Retrospective analysis of 5128 HVR cases (2005-2009) from Beijing Anzhen Hospital.
- Data randomly divided into model (n=3657) and validation (n=1471) groups.
- Multi-factor analysis identified risk factors from 32 pre- and intra-operative indicators.
Main Results:
- Identified specific risk factors for AVR (e.g., age, bypass time), MVR (e.g., etiology, heart failure history), and combined surgery (e.g., BMI, bypass time).
- Developed risk models demonstrating strong predictive ability (Hosmer-Lemeshow P-values > 0.15).
- Validation group ROC curve areas ranged from 0.845 to 0.958, confirming model accuracy.
Conclusions:
- The established risk models effectively quantify hospital mortality risk for patients undergoing cardiac valve replacement.
- These models provide valuable tools for clinical decision-making and patient management in cardiac surgery.
- Further research can refine these models for broader application and improved patient outcomes.
Background:
Numerous studies have developed a "severity score" or "risk index" for short-term mortality associated with coronary artery bypass grafting (CABG). Due to the different distribution of disease types, the number of valve surgeries in the US and Europe is relatively small. Thus, a risk-scoring system for valve surgeries was developed later and used less than that for the CABG surgery. We retrospectively reviewed 5128 cases of heart valve replacement, to quantitatively assess the risk factors for hospital mortality, and establish risk models for the hospital mortality of cardiac valve replacement patients.
Methods:
A total of 1549 cases of aortic valve replacement, 2460 cases of mitral valve replacement, and 1119 cases of combined aortic valve and mitral valve replacement that were recorded from January 2005 to December 2009 in the cardiac surgery database at Beijing Anzhen Hospital were selected for this study. The cases were randomly assigned to a model group (n = 3657) and a validation group (n = 1471) with a ratio of 7:3. Thirty-two pre- and intra-operative clinical indicators were selected as possible influencing factors for hospital mortality. Single-factor analysis was performed to screen these factors, and then multi-factor analysis was used to determine the risk factors for hospital mortality in the three surgeries and to establish risk models.
Results:
In the multi-factor analysis, age, body surface area, etiology, cardiopulmonary bypass time, preoperative cardiothoracic ratio, cardiac functional classification, and preoperative creatinine were risk factors for aortic valve replacement. Etiology, preoperative history of heart failure, cardiopulmonary bypass time, preoperative cardiothoracic ratio, and preoperative left ventricular end systolic diameter were risk factors for mitral valve replacement. Age, body mass index, cardiopulmonary bypass time, and cardiac function classification were risk factors for combined aortic valve and mitral valve replacement. The risk models showed good predictive ability (Hosmer-Lemeshow test: P = 0.981 in the model for aortic valve replacement, P = 0.503 in the model for mitral valve replacement, and P = 0.154 in the model for combined aortic valve and mitral valve replacement). The area under the ROC curve of the validation group was 0.958 (95%CI: 0.936 - 0.975) for the aortic valve replacement model, 0.876 (95%CI: 0.805 - 0.948) for the mitral valve replacement model, and 0.845 (95%CI: 0.753 - 0.939) for the combined aortic valve and mitral valve replacement, indicating that the risk models were good in predicting hospital mortality for surgeries.
Conclusion:
The three risk models can quantitatively assess the hospital mortality risk in the patients treated with cardiac valve replacement.

Related Concept Videos
 01:15
Aortic Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:27
Mitral Stenosis IV: Nursing Management
 01:25
Aortic Regurgitation III: Medical Management
 01:22
Mitral Valve Prolapse II: Assessment and Management