Treatment pathways for patients with atrial fibrillation
Related Experiment Video
Updated: May 26, 2026
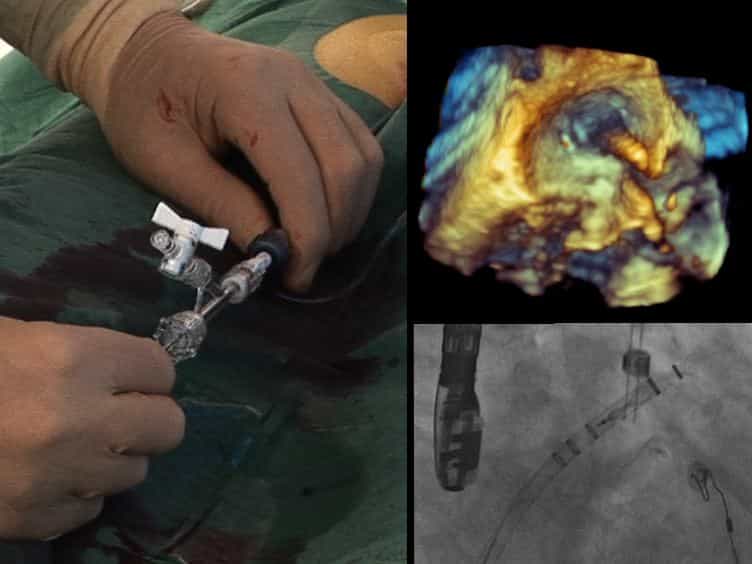
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
J A Hodgkinson1, C J Taylor, F D R Hobbs
1Department of Primary Care Clinical Sciences, School of Health and Population Sciences, University of Birmingham, Edgbaston, Birmingham, UK. j.a.hodgkinson@bham.ac.uk

Insights
Despite guidelines for atrial fibrillation (AF) treatment, high-risk patients often do not receive recommended anticoagulant therapy. Treatment patterns reveal significant deviations from best practices, with many patients discontinuing or not receiving anticoagulants as prescribed.
Area of Science:
- Cardiology
- Pharmacology
- Health Services Research
Background:
- Recent guidelines show growing concordance on best practices for atrial fibrillation (AF) treatment, particularly concerning anticoagulant use.
- However, adherence to these guidelines in clinical practice remains unclear.
- This study investigates whether patients receive treatments aligned with established best practices.
Purpose of the Study:
- To explore treatment pathways over time for patients diagnosed with atrial fibrillation (AF).
- To test if higher stroke-risk patients (by CHADS(2) score) are more likely to maintain or initiate anticoagulant therapy compared to lower-risk patients.
- To assess adherence to guideline recommendations in AF management.
Main Methods:
- Analysis of treatment pathways for 67,857 patients diagnosed with AF using the General Practice Research Database.
- Estimation of treatment change probabilities and average treatment durations over 5 years, stratified by CHADS(2) score.
- Comparison of treatment patterns based on initial therapy (anticoagulants vs. antiplatelets).
Main Results:
- No association was found between CHADS(2) score and the maintenance or discontinuation of antithrombotic treatments.
- Patients on antiplatelet therapy were more likely to change treatment than those on anticoagulants (approx. 60% vs. 50% in the first year).
- Approximately one-third of the treatment time for patients initiated on anticoagulants involved no anticoagulant use over 5 years, irrespective of CHADS(2) score.
Conclusions:
- While treatment is more often maintained than changed, particularly within the first year post-diagnosis, the overall rate of therapeutic change is notable.
- Prescription patterns indicate that too few high-risk AF patients receive guideline-recommended best practice treatment.
- A concerning trend shows some high-risk patients being moved away from best practice treatments over time.
Background:
Although there has been growing concordance over what constitutes best practice in recent guidelines for treatment of atrial fibrillation (AF), notably regarding anticoagulant use, it remains unclear whether patients are being treated accordingly.
Aims:
The aims of this study were to explore the pattern of treatment pathways - i.e. how patients are treated over time - for patients with AF, and to test the hypothesis that comparative to patients in lower stroke-risk categories (as measured by CHADS(2) score), patients with higher CHADS(2) scores are less likely to discontinue anticoagulant therapy or, if not started on anticoagulant treatment, more likely to be transferred to anticoagulant therapy, in keeping with guideline recommendations.
Setting:
A total of 67,857 patients with a diagnosis of AF in practices registered with the General Practice Research Database.
Methods:
A series of possible treatment pathways were identified, and for each initial treatment, we estimated the probability of treatment change and the average time that a patient newly diagnosed with AF spent on a particular treatment, projected across 5 years and stratified by CHADS(2) score.
Results:
There was no relationship between CHADS(2) score and maintenance or discontinuation of particular approaches to antithrombotic treatment. While those beginning on antiplatelet therapy were more likely to change treatment than those on anticoagulants (approximately 60% vs. 50% within the first year), as much as one-third of treatment time of all those starting on a therapeutic approach involving anticoagulants featured no use of anticoagulants (either as monotherapy or in combination) over the 5-year period, and whether treatment was discontinued or maintained did not vary by CHADS(2) score. No difference was found in treatment pathways controlling for post-2002 diagnoses as against the whole sample.
Conclusions:
Although there is more evidence of treatment maintenance than treatment change, especially in the first year after diagnosis, the amount of therapeutic change remains noteworthy and appears higher than in some previous studies. Prescription patterns for AF therapy suggest that too few high-risk patients are receiving best practice treatment, and particularly of concern is that some of these patients are being transferred away from best practice treatment over time.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:22
Heart Failure VI: Adjunct Therapies