Related Experiment Video
Updated: May 26, 2026
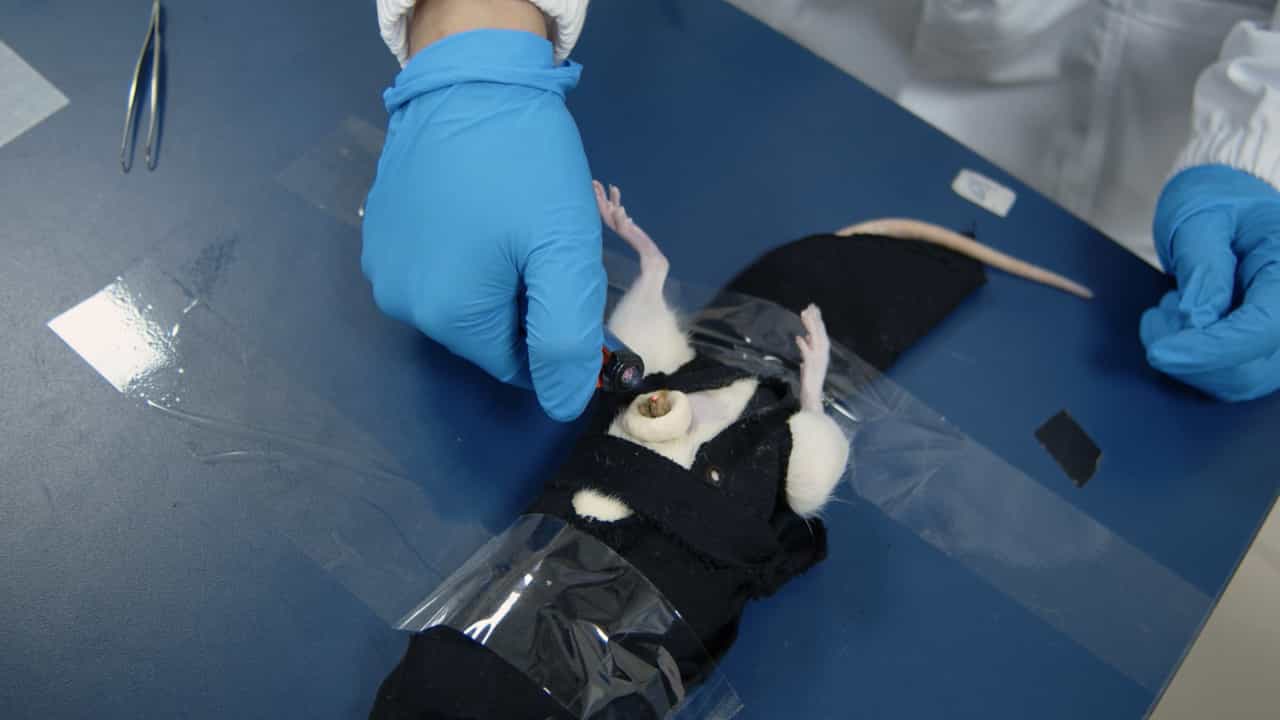

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Current and future medical treatments for menometrorrhagia during the premenopause
1Department of Endocrinology, Obstetrics & Gynecology, Hôpital Saint-Antoine, Assistance Publique-Hôpitaux de Paris, Paris, France. philippe.bouchard@sat.aphp.fr

Abstract:
Excessive menstrual bleeding reflects aberrant angiogenesis, generally due to submucosal myomas and endometrial polyps, although it is also frequently observed with long-term progestin-only contraception, impaired haemostasis and hormonal disorders. Surgery (hysterectomy, endometrial ablation) is used too frequently. Uterine artery embolisation is also an option for myomas. Medical treatments include combined oral contraception, progestins and levonorgestrel-releasing Intrauterine System. Gonadotropin-releasing hormone agonists provide significant improvements in bleeding for myomas, but also decrease estrogen secretion (e.g. hot flushes, decreased bone mass). Progestins, although used widely, remain poorly effective as they promote myoma cell growth. Recently, Selective Progesterone Receptor Modulators (SPRMs) have been shown to induce amenorrhea whilst maintaining endogenous estrogen secretion. Phase II studies have also demonstrated decreased fibroid size in SPRM-treated women. Although the mechanism of amenorrhea observed after SPRM treatment is still poorly understood, they may control uterine bleeding via a direct effect on endometrial blood vessels. Suppression of bleeding in women with uterine fibroids receiving SPRMs is associated with moderate reductions in uterine artery blood flow, without major changes in angiogenic factors and extracellular matrix composition; a clear difference to modifications observed with progestins. These data suggest major progress in the treatment of excessive menstrual bleeding.
Related Concept Videos
 01:28
Menopause
 01:25
Mitral Regurgitation III: Medical Management
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Mitral Stenosis III: Medical Management
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Open Angle Glaucoma: Treatment
Drugs such as carbonic anhydrase inhibitors, α2- and...