Stevens-Johnson syndrome complicating adalimumab therapy in rheumatoid arthritis disease

Aziza Mounach1, Asmae Rezqi, Abderrazak Nouijai

  • 1Rheumatology and Physical Rehabilitation Department, Military Hospital Mohammed V, PO Box: 1018, Rabat, Morocco. azizamounach@yahoo.fr

Rheumatology International
|December 22, 2011
PubMed

Related Concept Videos

Drug Toxicity: Allergic Reactions01:30

Drug Toxicity: Allergic Reactions

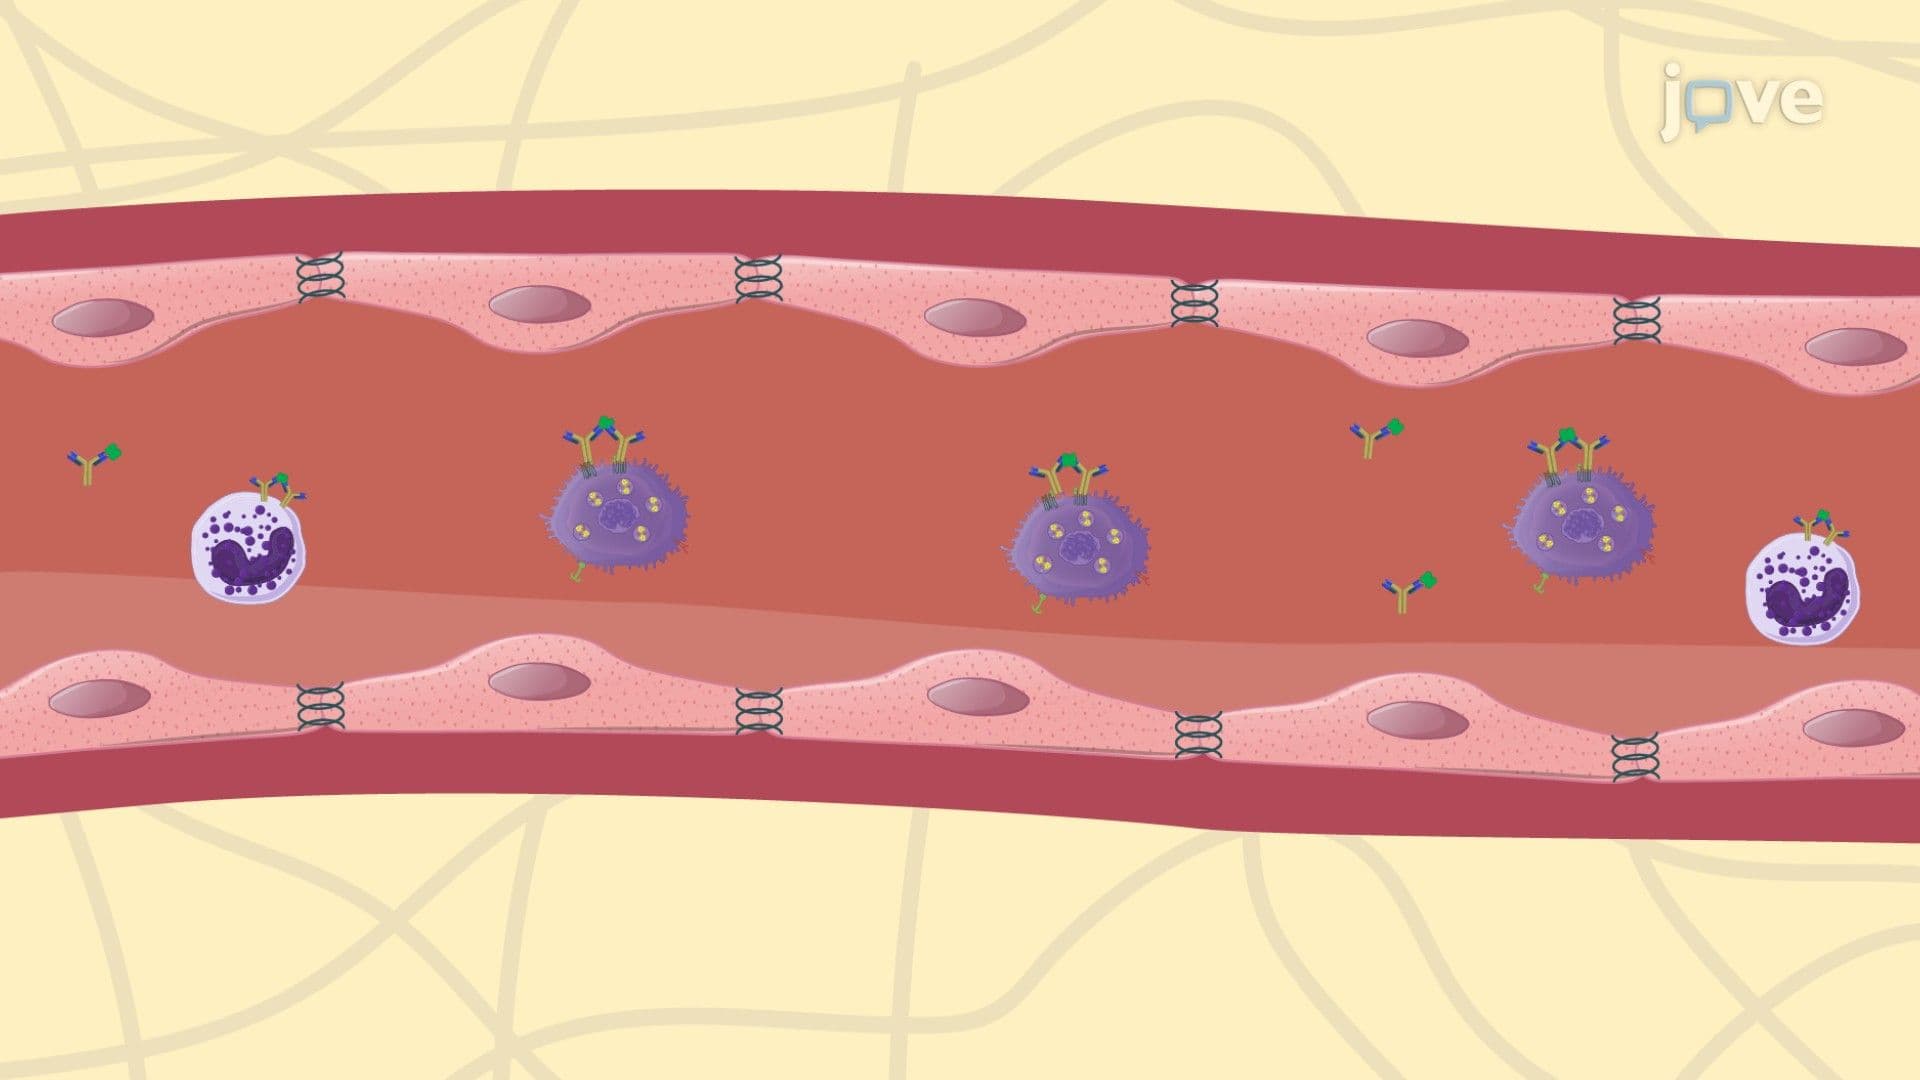
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
Drugs for Treatment of Crohn's Disease in IBD Using Biologic Agents: Anti-TNF01:24

Drugs for Treatment of Crohn's Disease in IBD Using Biologic Agents: Anti-TNF
Tumor Necrosis Factor (TNF), a proinflammatory cytokine, contributes significantly to the inflammation seen in Crohn's disease. It exists as soluble TNF and membrane-bound TNF, with actions mediated through TNF receptors (TNFR). TNFR activation leads to the release of proinflammatory cytokines, T-cell activation, collagen production, and leukocyte migration, all contributing to inflammation in Crohn's disease. Anti-TNF monoclonal antibodies, namely infliximab (Remicade), adalimumab (Humira),...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

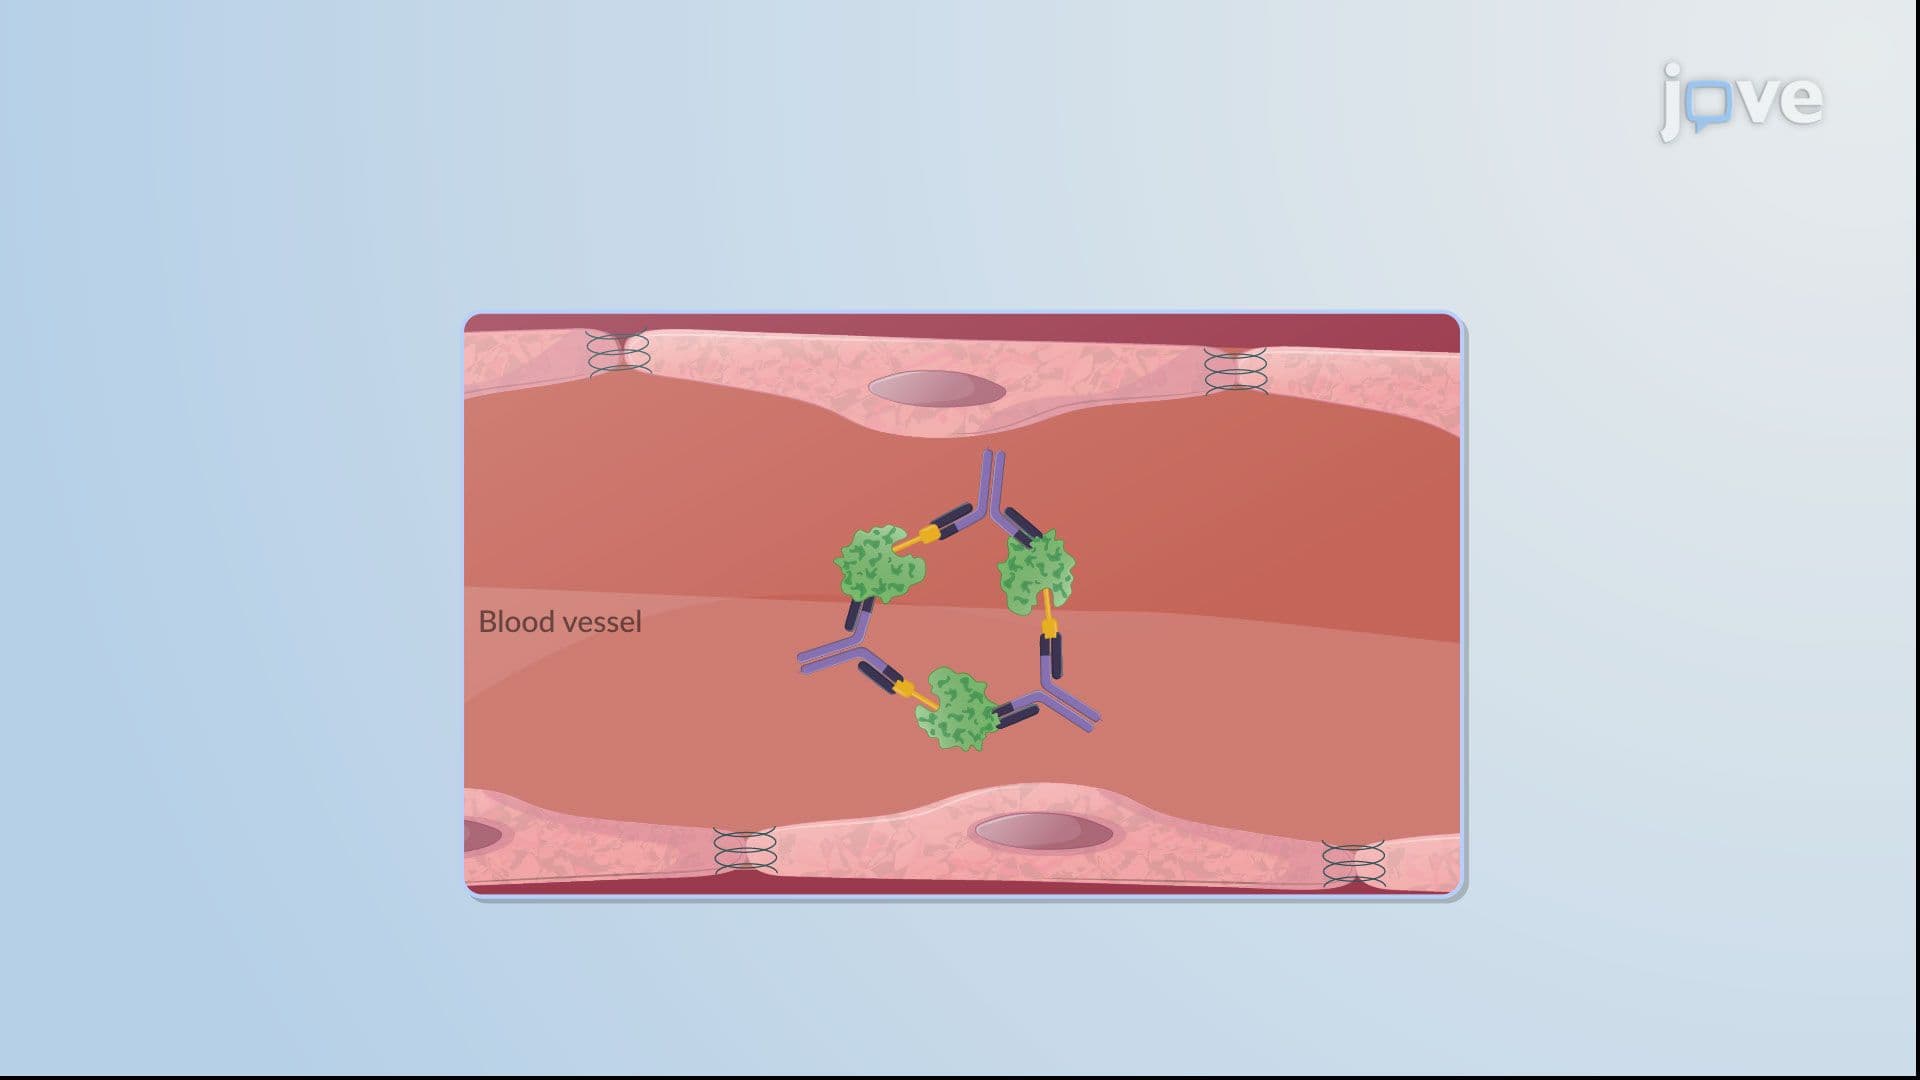
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...
Inflammatory Bowel Disease IV: Clinical Manifestations01:20

Inflammatory Bowel Disease IV: Clinical Manifestations

Inflammatory bowel disease (IBD) encompasses two major chronic disorders—ulcerative colitis and Crohn’s disease—each characterized by relapsing episodes of gastrointestinal inflammation. Although they share certain clinical features, their patterns of involvement and manifestations differ in ways that aid diagnosis and guide management.Ulcerative ColitisUlcerative colitis is limited to the colon and rectum and involves continuous inflammation of the mucosal layer. The disease course is marked...
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents01:29

Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents

Crohn's disease is an inflammatory bowel disorder marked by chronic inflammation of the GI tract. Various treatment strategies for Crohn's disease are employed, such as immunomodulatory agents, glucocorticoids, and biologics or anti-TNF therapy. Azathioprine (Imuran), a commonly used immunomodulatory drug for Crohn's disease, is converted in the body to mercaptopurine, which inhibits purine biosynthesis and cell proliferation. Both are utilized in severe cases of Inflammatory Bowel Disease...
Inflammatory Bowel Disease III: Crohn's Disease01:25

Inflammatory Bowel Disease III: Crohn's Disease

Crohn’s disease is a chronic, relapsing form of inflammatory bowel disease characterized by segmental, transmural inflammation that can affect any part of the gastrointestinal tract. Its pathogenesis arises from a combination of genetic susceptibility, environmental exposures, epithelial barrier dysfunction, and immune dysregulation. Together, these factors lead to an exaggerated immune response against components of the gut microbiome.Genetic and Environmental InfluencesMultiple genetic...