Related Experiment Video
Updated: May 26, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Obstetric levator ani muscle injuries: current status
N Schwertner-Tiepelmann1, R Thakar, A H Sultan
1Croydon University Hospital, Croydon, UK.

Levator ani muscle (LAM) injuries occur in 13-36% of women who have a vaginal delivery. Although these injuries were first described using magnetic resonance imaging, three-dimensional transperineal and endovaginal ultrasound has emerged as a more readily available and economic alternative to identify LAM morphology. Injury to the LAM is attributed to vaginal delivery resulting in reduced pelvic floor muscle strength, enlargement of the vaginal hiatus and pelvic organ prolapse. There is inconclusive evidence to support an association between LAM injuries and stress urinary incontinence and there seems to be a trend towards the development of fecal incontinence. Longitudinal studies with long-term follow-up assessing the LAM before and after childbirth are lacking. Furthermore, the consequence of LAM injuries on quality of life due to prolapse and/or urinary and fecal incontinence have not been evaluated using validated questionnaires. Direct comparative studies using the above-mentioned imaging modalities are needed to determine the true gold standard for the diagnosis of LAM injuries. This would enable consistency in definition and classification of LAM injuries. Only then could high-risk groups be identified and preventive strategies implemented in obstetric practice.
Levator ani muscle (LAM) injuries occur in 13-36% of women who have a vaginal delivery. Although these injuries were first described using magnetic resonance imaging, three-dimensional transperineal and endovaginal ultrasound has emerged as a more readily available and economic alternative to identify LAM morphology. Injury to the LAM is attributed to vaginal delivery resulting in reduced pelvic floor muscle strength, enlargement of the vaginal hiatus and pelvic organ prolapse. There is inconclusive evidence to support an association between LAM injuries and stress urinary incontinence and there seems to be a trend towards the development of fecal incontinence. Longitudinal studies with long-term follow-up assessing the LAM before and after childbirth are lacking. Furthermore, the consequence of LAM injuries on quality of life due to prolapse and/or urinary and fecal incontinence have not been evaluated using validated questionnaires. Direct comparative studies using the above-mentioned imaging modalities are needed to determine the true gold standard for the diagnosis of LAM injuries. This would enable consistency in definition and classification of LAM injuries. Only then could high-risk groups be identified and preventive strategies implemented in obstetric practice.

Related Concept Videos
 01:26
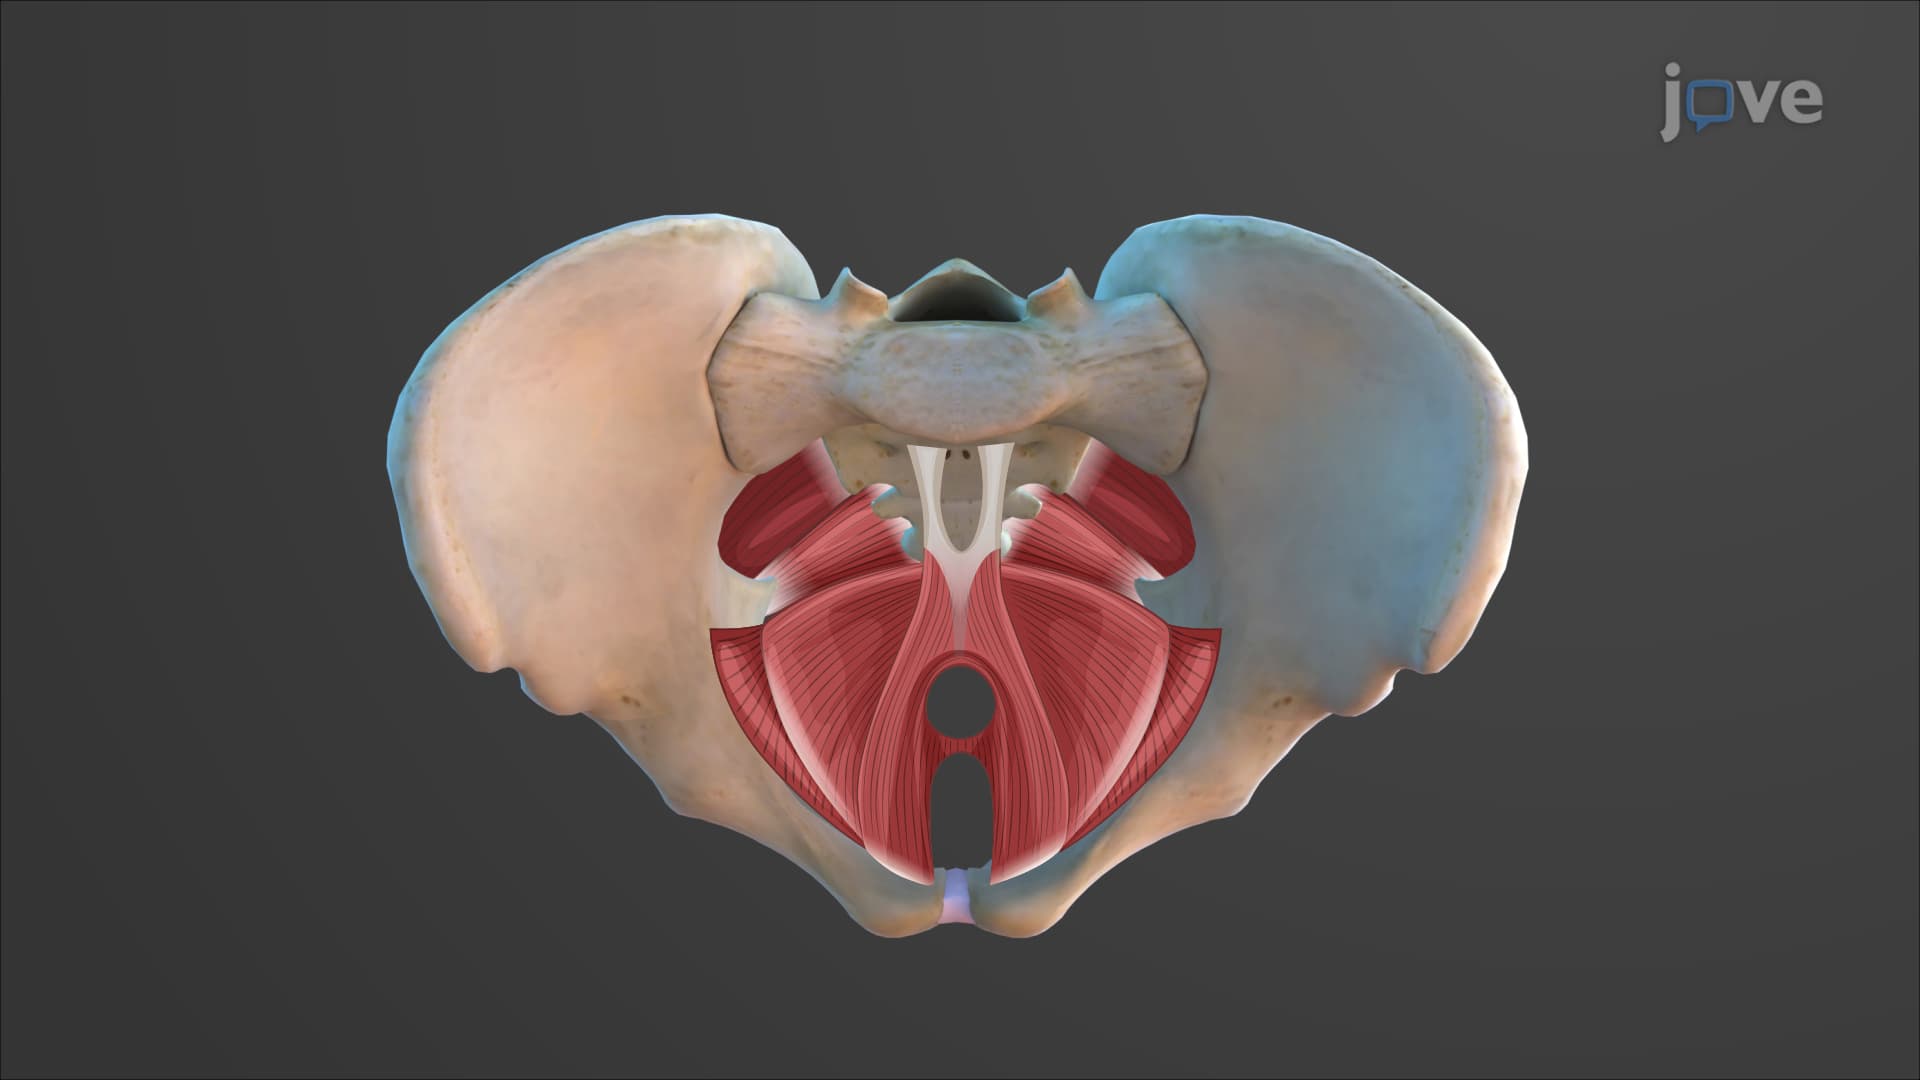
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Muscles of the Abdomen
Anterolateral Region
The anterolateral region comprises five paired muscles classified into the lateral and anterior...
 01:29
Intestinal Obstruction I: Introduction
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: