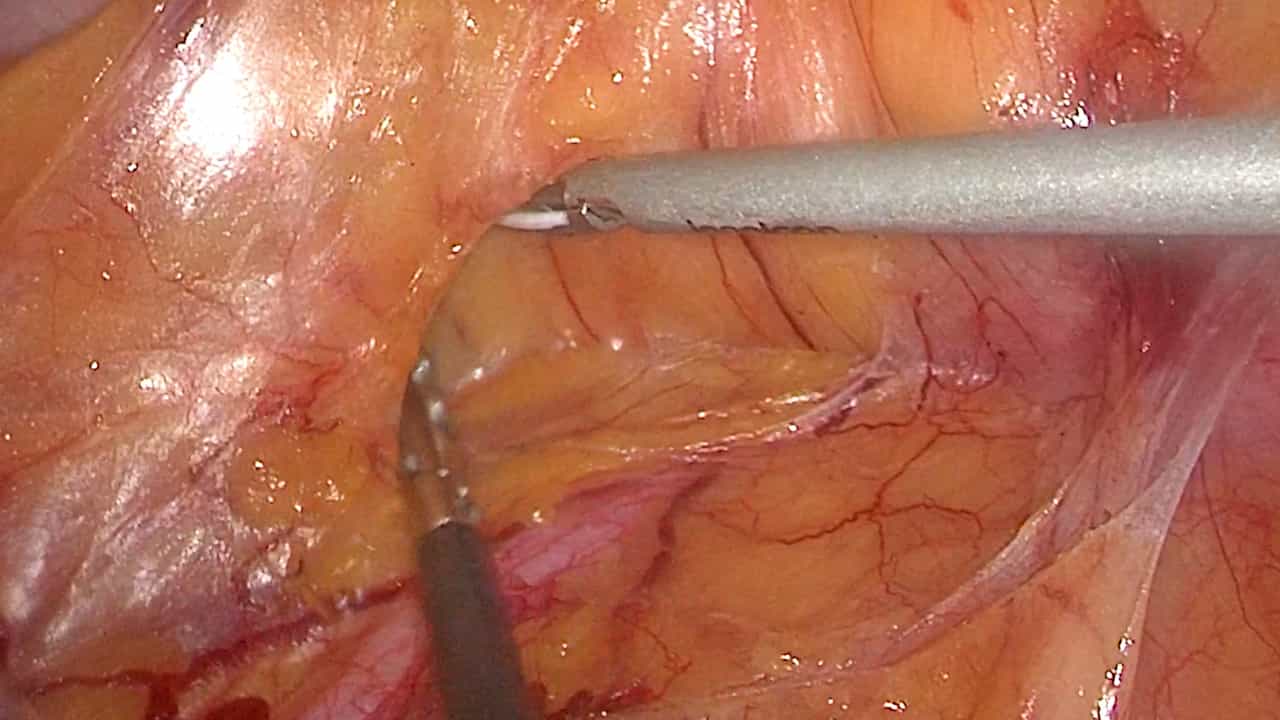
Related Experiment Video
Updated: May 26, 2026

An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Esophageal reconstruction using the terminal ileum and right colon in esophageal cancer surgery
Yoichi Hamai1, Jun Hihara, Manabu Emi
1Department of Surgical Oncology, Research Institute for Radiation Biology and Medicine, Hiroshima University, 1-2-3 Kasumi, Minami-Ku, Hiroshima, 734-8551, Japan. yyhamai@hotmail.com

Purpose:
To evaluate the outcomes of colon interposition based on our surgical experience.
Methods:
We reviewed data from 40 patients who underwent esophagectomy with colon interposition using the terminal ileum and right colon, to treat esophageal cancer, between January 1990 and December 2009.
Results:
Transthoracic esophagectomy, transhiatal esophagectomy, and pharyngolaryngoesophagectomy were performed in 31 (77.5%), 8 (20.0%), and 1 (2.5%) patients, respectively. The routes of the colon interposition were posterior mediastinal in 30 (75.0%) patients, retrosternal in 5 (12.5%), and subcutaneous in 5 (12.5%). The median operative time was 450 min (range 320-760 min) and the median blood loss was 755 ml (range 180-3,000 ml). Overall postoperative morbidity involved 18 (45.0%) patients and included esophagoileostomy leakage in 7 (17.5%; minor, n = 4; major, n = 3) and necrosis of the colon conduit in 2 (5%) patients. The 30- and 90-day mortality rates were 0 and 2.5%, respectively. The 1-, 3-, and 5-year survival rates were 80, 66, and 66%, respectively.
Conclusions:
Our surgical outcomes were acceptable in relation to other published results and the prognosis was favorable. Thus, esophageal reconstruction using the ileum and right colon is useful for patients with esophageal cancer for whom the stomach is not available. We currently perform colon interposition with microvascular anastomoses for grafts via the subcutaneous route to increase the safety of this operation.