Related Experiment Video
Updated: May 26, 2026
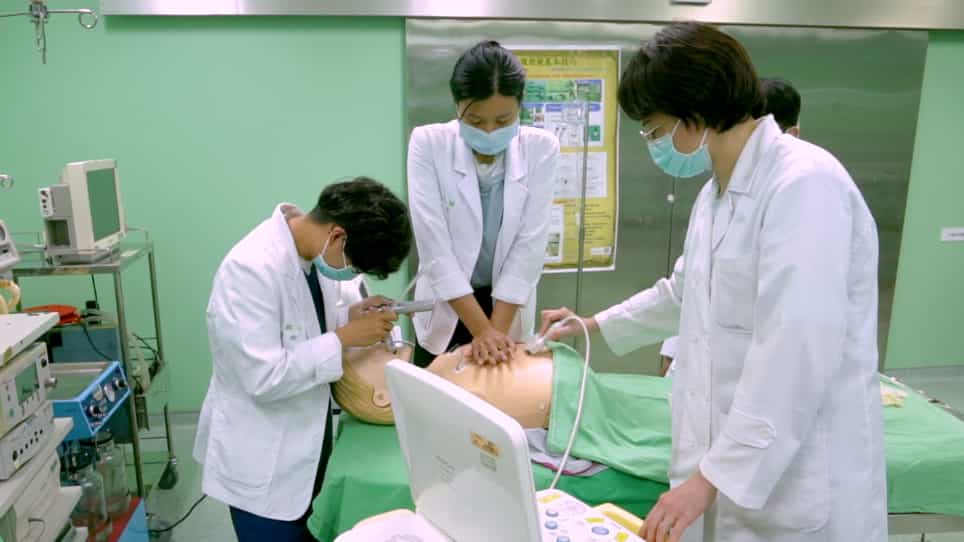
Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
What is the role of chest compression depth during out-of-hospital cardiac arrest resuscitation?
Ian G Stiell1, Siobhan P Brown, James Christenson
1Department of Emergency Medicine and Ottawa Hospital Research Institute, University of Ottawa, Ottawa, Ontario, Canada. istiell@ohri.ca

Background:
The 2010 international guidelines for cardiopulmonary resuscitation recently recommended an increase in the minimum compression depth from 38 to 50 mm, although there are limited human data to support this. We sought to study patterns of cardiopulmonary resuscitation compression depth and their associations with patient outcomes in out-of-hospital cardiac arrest cases treated by the 2005 guideline standards.
Design:
Prospective cohort.
Setting:
Seven U.S. and Canadian urban regions.
Patients:
We studied emergency medical services treated out-of-hospital cardiac arrest patients from the Resuscitation Outcomes Consortium Epistry-Cardiac Arrest for whom electronic cardiopulmonary resuscitation compression depth data were available, from May 2006 to June 2009.
Measurements:
We calculated anterior chest wall depression in millimeters and the period of active cardiopulmonary resuscitation (chest compression fraction) for each minute of cardiopulmonary resuscitation. We controlled for covariates including compression rate and calculated adjusted odds ratios for any return of spontaneous circulation, 1-day survival, and hospital discharge.
Main Results:
We included 1029 adult patients from seven U.S. and Canadian cities with the following characteristics: Mean age 68 yrs; male 62%; bystander witnessed 40%; bystander cardiopulmonary resuscitation 37%; initial rhythms: Ventricular fibrillation/ventricular tachycardia 24%, pulseless electrical activity 16%, asystole 48%, other nonshockable 12%; outcomes: Return of spontaneous circulation 26%, 1-day survival 18%, discharge 5%. For all patients, median compression rate was 106 per minute, median compression fraction 0.65, and median compression depth 37.3 mm with 52.8% of cases having depth <38 mm and 91.6% having depth <50 mm. We found an inverse association between depth and compression rate ( p < .001). Adjusted odds ratios for all depth measures (mean values, categories, and range) showed strong trends toward better outcomes with increased depth for all three survival measures.
Conclusions:
We found suboptimal compression depth in half of patients by 2005 guideline standards and almost all by 2010 standards as well as an inverse association between compression depth and rate. We found a strong association between survival outcomes and increased compression depth but no clear evidence to support or refute the 2010 recommendations of >50 mm. Although compression depth is an important component of cardiopulmonary resuscitation and should be measured routinely, the most effective depth is currently unknown.

Related Concept Videos
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: