Related Experiment Video
Updated: May 26, 2026


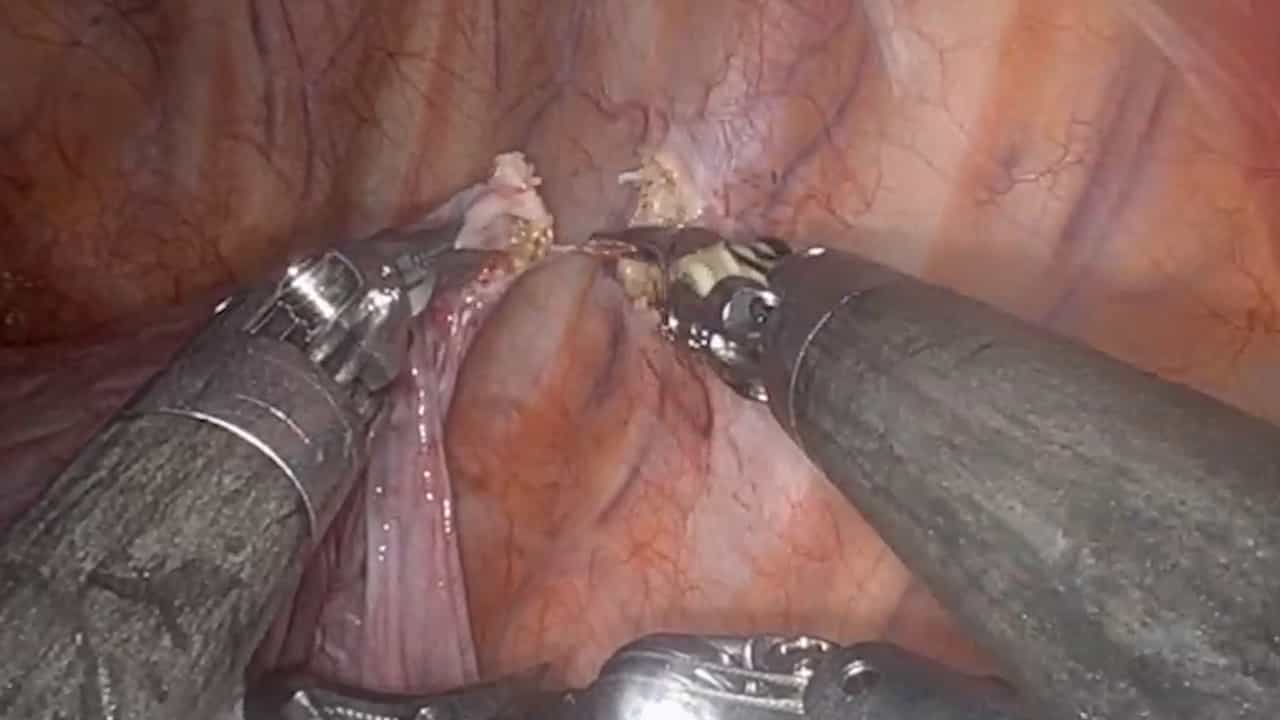
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Pneumonectomy: calculable or non-tolerable risk factor in trimodal therapy for Stage III non-small-cell lung cancer?
Volker Steger1, Werner Spengler, Jürgen Hetzel
1Department of Thoracic, Cardiac and Vascular Surgery, Tuebingen University, Tuebingen, Germany. vrsteger@gmx.de

Objectives:
Lung cancer is the leading cause of death in cancer statistics throughout developed countries. While single surgical approach provides best results in early stages, multimodality approaches have been employed in advanced disease and demonstrated superior results in selected patients. With either full-dose chemotherapy and/or radiotherapy, patients usually have a poor general condition when entering surgical therapy and therefore neoadjuvant therapy can lead to a higher morbidity and mortality. Especially in the case of pneumonectomy as the completing procedure, mortality rate can exceed over 40%. Therefore, chest physicians often shy away from recommending pneumonectomy as final step in trimodal protocols. We analysed our experience with pneumonectomy after neoadjuvant chemoradiotherapy in advanced non-small-cell lung cancer (NSCLC) with a focus on feasibility, outcome and survival.
Methods:
Retrospective, single-centre study of 146 patients with trimodal neoadjuvant therapy for NSCLC Stage III over 17 years time span. Follow-up was taken from our own outpatient files and with survival check of central registry office in Baden-Württemberg, Germany.
Results:
A total of 118 men and 28 women received 62 lobectomies, 6 bi-lobectomies and 78 pneumonectomies after two different neoadjuvant protocols for Stage III NSCLC. Overall morbidity rate was 53 and 56% after pneumonectomy. Overall hospital mortality rate was 4.8 and 6.4% after pneumonectomy. Overall median survival rate was 31 months with a 5-year survival rate of 38% (Kaplan-Meier). Pneumonectomy, right-sited pneumonectomy and initial T- and N-stages were no risk factors for survival (log-rank test). Significant factors for survival were ypT-stage, ypN-stage, yUICC-stage in univariate testing (log-rank test) and ypUICC-stage in multivariate testing (Cox's regression).
Conclusions:
Pneumonectomy in neoadjuvant trimodal approach for Stage III NSCLC can be done safe with acceptable mortality rate. Patients should not withhold from operation because of necessitating pneumonectomy. Not the procedure but the selection, response rate and R0-resection are crucial for survival after trimodal therapy in experienced centres.
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...