Related Experiment Video
Updated: May 25, 2026

Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Effects of phosphonoformic acid and renagel on renal type IIa sodium-dependent phosphate cotransporter mRNA
Ming Zeng1, Xiaoyun Wang, Xiaobing Wang
1Department of Nephrology, The First Affiliated Hospital of Nanjing Medical University, Nanjing, PR China.

Objective:
To investigate the effects of phosphonoformic acid (PFA) and sevelamer hydrochloride (Renagel) on renal type IIa sodium-dependent phosphate cotransporter (NaPi-2) mRNA expression in hyperphosphatemia rats.
Methods:
Thirty rats were randomly divided into five groups based on the diet for 2 weeks after 5/6 nephrectomy (Nx): Nx + high-phosphate (HP; 1.2% P) diet; Nx + low-phosphate (LP; 0.2% P) diet; HP + PFA (injected with 0.15 g/kg PFA daily); HP + Saline (injected with the same amount of saline daily); and HP + Renagel (2%) group. Another 12 rats were sham operated and divided into Sham + HP and Sham + LP groups. Serum ionized calcium, phosphorus (P), and intact parathyroid hormone (iPTH) were measured on days 2, 7, and 14. Serum 1,25(OH)2D3 was measured on day 14 and NaPi-2 mRNA levels were assayed by RT-PCR.
Results:
PFA decreased iPTH level but had no effect on NaPi-2 mRNA expression. Renagel decreased serum P and iPTH levels, but upregulated renal NaPi-2 mRNA expression.
Conclusions:
Both PFA and Renagel are effective drugs to decrease iPTH level and they might be potential candidates for treatment of clinical secondary hyperparathyroidism. Renagel can also decrease serum P and upregulate renal NaPi-2 mRNA expression.
More Related Videos


Related Concept Videos
 01:28
Renal Drug Excretion: Tubular Secretion
 01:29
Acute Kidney Injury II: Pathophysiology
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:29
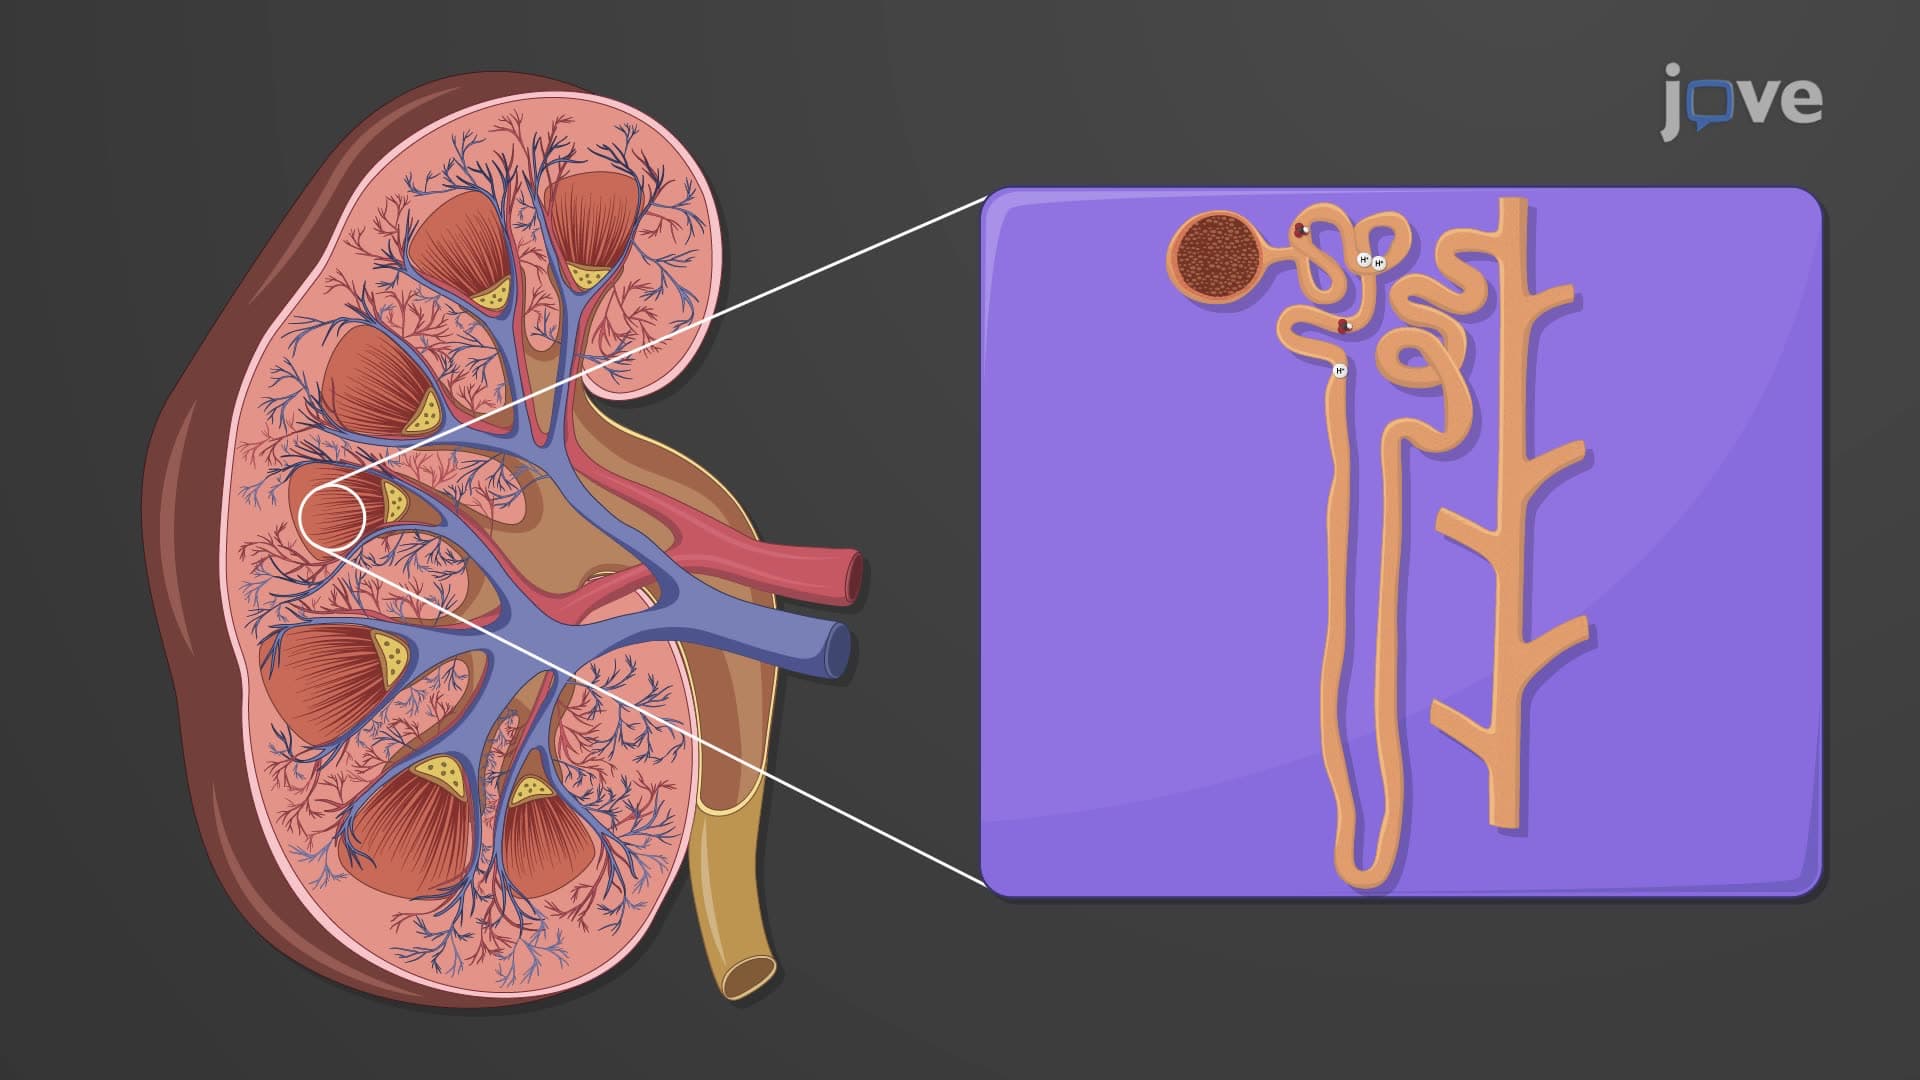
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Renal Drug Excretion: Tubular Reabsorption