Related Experiment Video
Updated: May 25, 2026
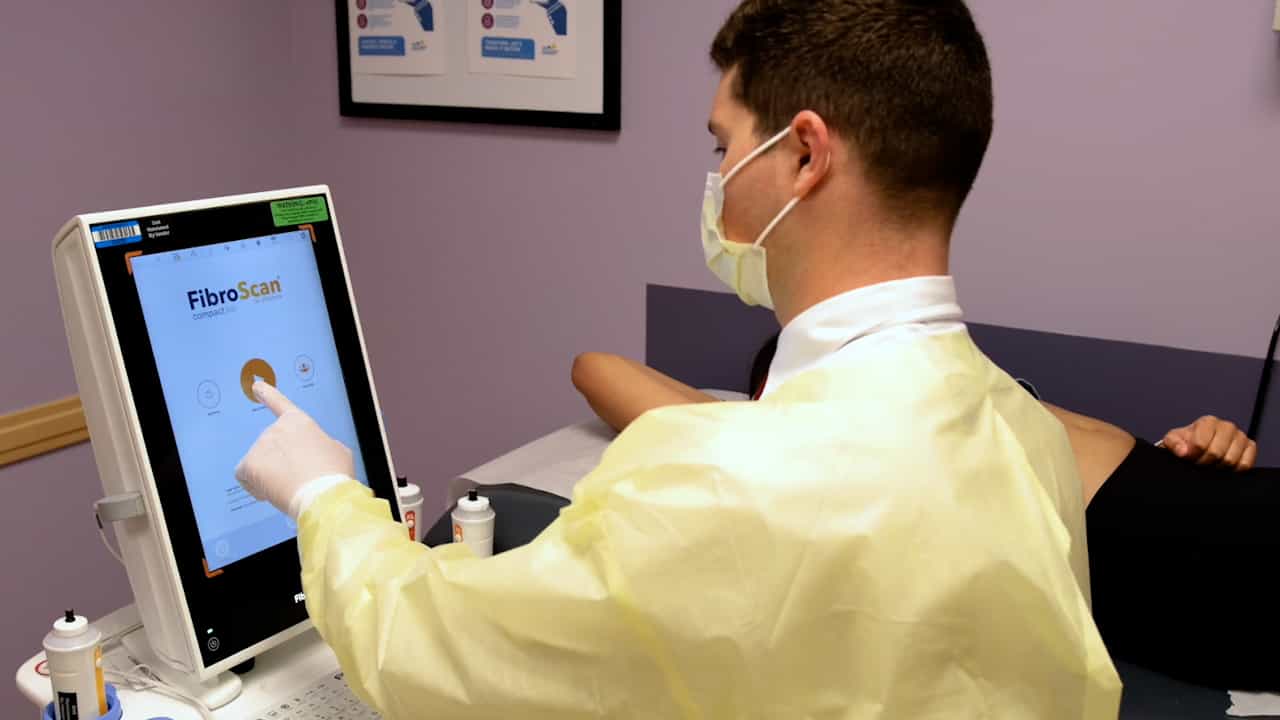
Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
Transient elastography identifies liver recipients with nonviral graft disease after transplantation: a guide for
Cristina Rigamonti1, Mirella Fraquelli, Anan Judina Bastiampillai
1First Division of Gastroenterology (A. M. and A. Migliavacca Center for Liver Disease), University of Milan, Milan, Italy. crigamo@tin.it

Abstract:
Transient elastography (TE) reliably predicts the severity of recurrent hepatitis C virus after orthotopic liver transplantation (OLT); however, its accuracy in evaluating nonviral liver graft damage is unknown. Between 2006 and 2009, 69 OLT recipients [37 for hepatitis B virus/hepatitis D virus (recurrence-free), 20 for autoimmune/cholestatic liver disease, 6 for alcoholic liver disease, and 6 for mixed etiologies] underwent protocol/on-demand liver biopsy (LB) and concomitant TE. A histological diagnosis of graft disease was made according to criteria defined by the Banff working group. Sixty-five patients (94%) had reliable TE examinations during a median post-OLT follow-up of 18 months (range = 7-251 months). LB samples (median length = 35 mm) showed graft damage in 28 patients (43%): idiopathic chronic hepatitis (11), steatohepatitis (3), rejection (3), cholangitis (2), and autoimmune/cholestatic recurrence (9). Patients with graft damage had significantly higher serum liver enzyme levels and TE results (median = 7.8 kPa, range = 5.4-27.4 kPa) than the 37 patients without graft damage (median = 5.3 kPa, range = 3.1-7.4 kPa, P < 0.001). By a receiver operating characteristic curve analysis, 2 TE cutoffs for the diagnosis of graft damage were identified: 5.3 kPa with 100% sensitivity and 7.4 kPa with 100% specificity. The pretest probability of graft damage was 43%; in patients with TE values ≤5.3 kPa, the posttest probability of graft damage fell to 0%, but in patients with TE results >7.4 kPa, the posttest probability increased to 100%. In conclusion, the dual TE cutoff allows accurate discrimination between the absence and presence of nonviral liver graft damage and improves the clinical management of OLT recipients in terms of the selection of patients most in need of LB.
Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:28
Kidney Transplant I: Introduction