Related Experiment Video
Updated: May 25, 2026
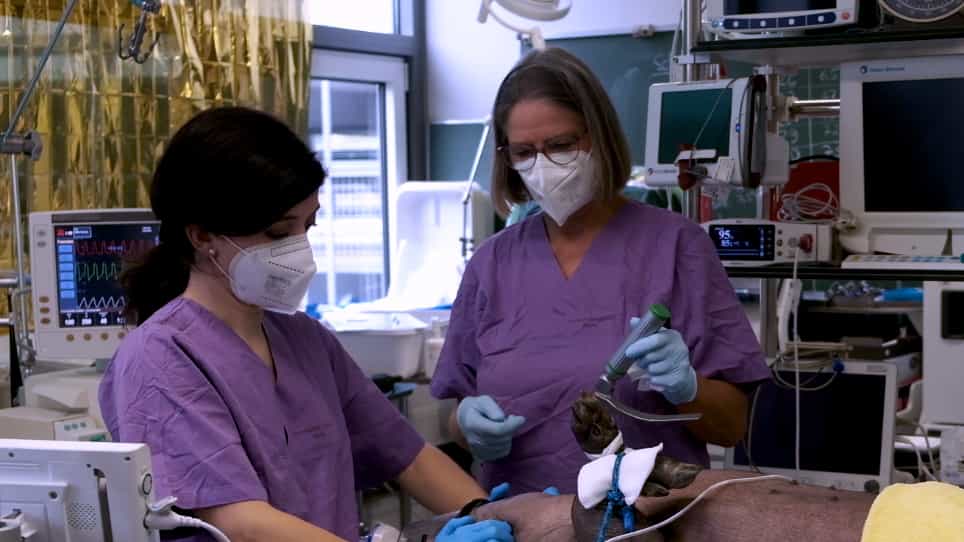

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Incidence of unanticipated difficult airway in obstetric patients in a teaching institution
Weike Tao1, Jason T Edwards, Faping Tu
1Department of Anesthesiology and Pain Management, The University of Texas Southwestern Medical Center at Dallas, 5323 Harry Hines Blvd, Dallas, TX, 75390-9068, USA, weike.tao@utsouthwestern.edu.

PURPOSE: Our aim was to determine the incidence of difficult intubation during pregnancy-related surgery at a high-risk, high-volume teaching institution. METHODS: Airway experience was analyzed among patients who had pregnancy-related surgery under general anesthesia from January 2001 through February 2006. A difficult airway was defined as needing three or more direct laryngoscopy (DL) attempts, use of the additional airway equipment after the DL attempts, or conversion to regional anesthesia due to inability to intubate. Airway characteristics were compared between patients with and without a difficult airway. In addition, pre- and postoperative airway evaluations were compared to identify factors closely related to changes from pregnancy. RESULTS: In a total of 30,766 operations, 2,158 (7%) were performed with general anesthesia. Among these, 1,026 (47.5%) were for emergency cesarean delivery (CD), 610 (28.3%) for nonemergency CD, and 522 (24.2%) for non-CD procedures. A total of 12 patients (0.56%) were identified as having a difficult airway. Four patients were intubated with further DL attempts; others required mask ventilation and other airway equipment. Two patients were ventilated through a laryngeal mask airway without further intubation attempts. Ten of the 12 difficult airway cases were encountered by residents during their first year of clinical anesthesia training. There were no maternal or fetal complications except one possible aspiration. CONCLUSION: Unanticipated difficult airways accounted for 0.56% of all pregnancy-related surgical patients. More than 99.9% of all obstetric patients could be intubated. A difficult airway is more likely to be encountered by anesthesia providers with <1 year of experience. Proper use of airway equipment may help secure the obstetric airway or provide adequate ventilation. Emergency CD did not add an additional level of difficulty over nonemergency CD.
PURPOSE: Our aim was to determine the incidence of difficult intubation during pregnancy-related surgery at a high-risk, high-volume teaching institution. METHODS: Airway experience was analyzed among patients who had pregnancy-related surgery under general anesthesia from January 2001 through February 2006. A difficult airway was defined as needing three or more direct laryngoscopy (DL) attempts, use of the additional airway equipment after the DL attempts, or conversion to regional anesthesia due to inability to intubate. Airway characteristics were compared between patients with and without a difficult airway. In addition, pre- and postoperative airway evaluations were compared to identify factors closely related to changes from pregnancy. RESULTS: In a total of 30,766 operations, 2,158 (7%) were performed with general anesthesia. Among these, 1,026 (47.5%) were for emergency cesarean delivery (CD), 610 (28.3%) for nonemergency CD, and 522 (24.2%) for non-CD procedures. A total of 12 patients (0.56%) were identified as having a difficult airway. Four patients were intubated with further DL attempts; others required mask ventilation and other airway equipment. Two patients were ventilated through a laryngeal mask airway without further intubation attempts. Ten of the 12 difficult airway cases were encountered by residents during their first year of clinical anesthesia training. There were no maternal or fetal complications except one possible aspiration. CONCLUSION: Unanticipated difficult airways accounted for 0.56% of all pregnancy-related surgical patients. More than 99.9% of all obstetric patients could be intubated. A difficult airway is more likely to be encountered by anesthesia providers with <1 year of experience. Proper use of airway equipment may help secure the obstetric airway or provide adequate ventilation. Emergency CD did not add an additional level of difficulty over nonemergency CD.


Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.